Related Experiment Video
Updated: Oct 14, 2026
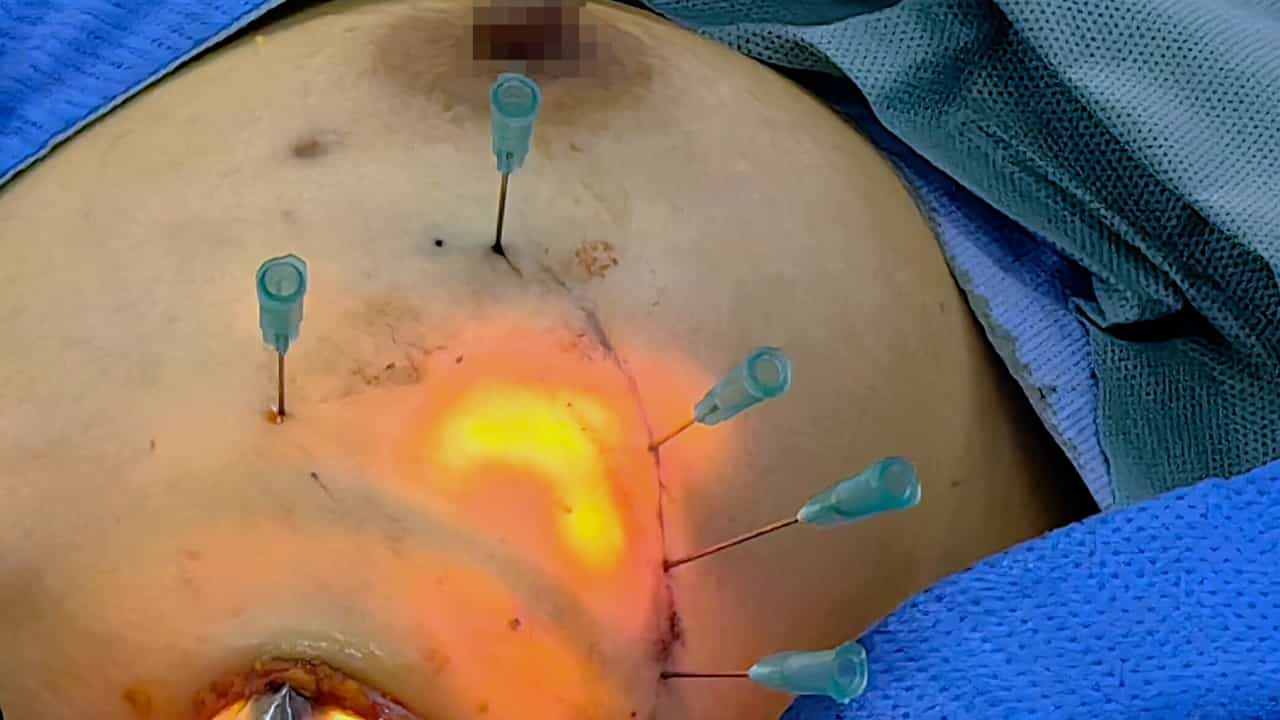
Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025
Robotic-assisted versus conventional coronary artery bypass grafting: a systematic review, meta-analysis, and trial
Ahmed Abdelsamad1,2, Ibrahim Khalil3, Mohammed Hrebat4
1Department of Surgery II, University of Witten/Herdecke, Witten, Germany. ahmed6361410@gmail.com.

Background:
Robotic-assisted coronary artery bypass grafting (RA-CABG) is an evolving minimally invasive alternative to conventional CABG (C-CABG), but comparative evidence remains fragmented. We conducted a comprehensive systematic review, meta-analysis, and trial sequential analysis to compare outcomes between RA-CABG and C-CABG.
Methods:
Following PRISMA 2020 guidelines, we searched PubMed, Embase, Cochrane CENTRAL, and Web of Science through January 2026. Studies comparing RA-CABG to C-CABG reporting at least one outcome of interest were eligible. Random-effects meta-analyses using DerSimonian-Laird estimators were performed. Risk of bias was assessed using ROBINS-I. Trial sequential analysis evaluated the conclusiveness of cumulative evidence.
Results:
Nine studies comprising 39,918 patients (13,638 RA-CABG; 26,280 C-CABG) were included. All included studies were observational in design, and long-term outcome data were sparse. RA-CABG was associated with significantly lower mortality (OR 0.55, 95% CI 0.43-0.69; P < 0.001; I²=0%), atrial fibrillation (OR 0.53; P < 0.001), respiratory failure (OR 0.31; P < 0.001), blood transfusion (OR 0.28; P < 0.001), hospital length of stay (MD - 1.95 days; P < 0.001), and ICU stay (MD - 22.7 h; P < 0.001). Stroke showed a non-significant trend favoring RA-CABG (OR 0.76; P = 0.071). Trial sequential analysis confirmed conclusive evidence for mortality, atrial fibrillation, respiratory failure, and blood transfusion. Results were robust across sensitivity analyses.
Conclusions:
In this meta-analysis of observational studies, RA-CABG was associated with significantly improved short-term outcomes compared to C-CABG across multiple endpoints, with conclusive statistical evidence for four of seven binary outcomes. However, all included studies were observational, and these associations should be interpreted with caution given potential residual confounding and case-selection bias. Multicenter randomized trials with long-term follow-up are needed to confirm these findings.