Related Experiment Video
Updated: Oct 15, 2026
Robotic Enucleation of an Intra-Pancreatic Insulinoma in the Pancreatic Head
Published on: January 3, 2020
Robotic Parenchyma-Preserving Pancreatic Resection for Focal Congenital Hyperinsulinism in an Infant
Manjunath Haridas1, Arvind Sabharwal2, Ajay N3
1Department of Surgical Gastroenterology, Manipal Hospital Whitefield, Bengaluru, Karnataka, India. (Dr. Haridas).

Background:
Robot-assisted surgery has been increasingly adopted over traditional laparoscopic and open procedures. However, its application in neonates and infants remains limited. Restricted space, delicate tissues, and the need for special instruments complicate its use. This case report describes the application of robot-assisted surgery in an infant with focal congenital hyperinsulinism.
Materials And Methods:
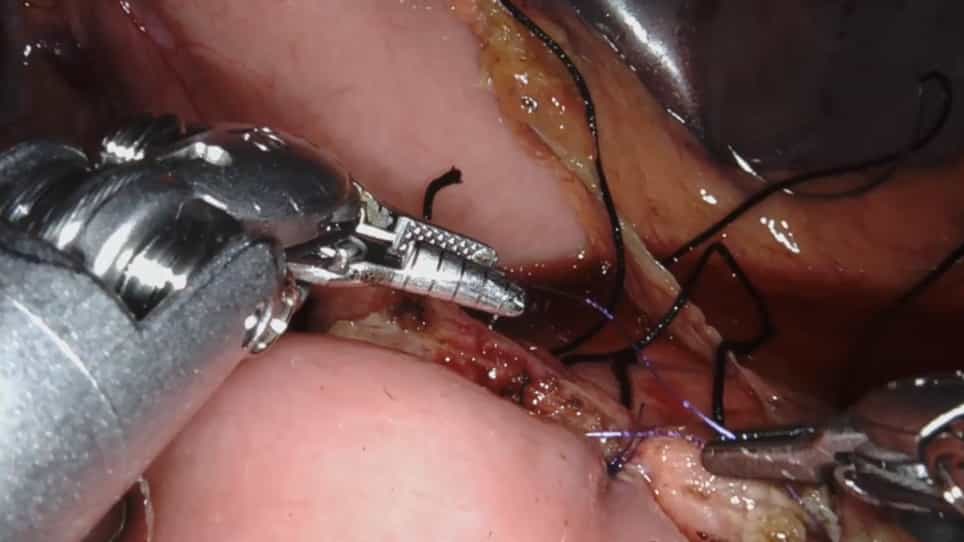
We describe the management of focal congenital hyperinsulinism in an infant using robotic surgery with indocyanine green injection, intraoperative ultrasound, and a suture-based retraction technique.
Case Description:
Herein, we present a case of an infant weighing less than 5 kg who underwent robotic surgery. The procedure was performed using the 3 arms of the da Vinci Xi robotic system and a suture-based intraoperative retraction technique. Intraoperative frozen sections confirmed the complete excision of the focal disease. Final histopathology revealed focal adenomatous hyperplasia. Intraoperatively, plasma glucose levels transiently increased after resection peaking at 23.1 mmol/L. Intravenous dextrose was discontinued. The postoperative course was uneventful, and the infant was discharged on postoperative day nine after tolerating full oral feeds. At follow-up in 8 months, the child remained euglycemic without any medical therapy or hypoglycemic episodes.
Discussion:
This case demonstrates the feasibility of robotic-assisted parenchyma-preserving pancreatic resection in a 4.6-kg infant. Careful attention to operative planning and the use of adjuncts, such as indocyanine green fluorescence and intraoperative ultrasonography, is critical. Minimizing the number of additional ports and using suture-based retraction techniques can help achieve successful robotic surgery in this high-risk population.