Related Experiment Video
Updated: Oct 15, 2026
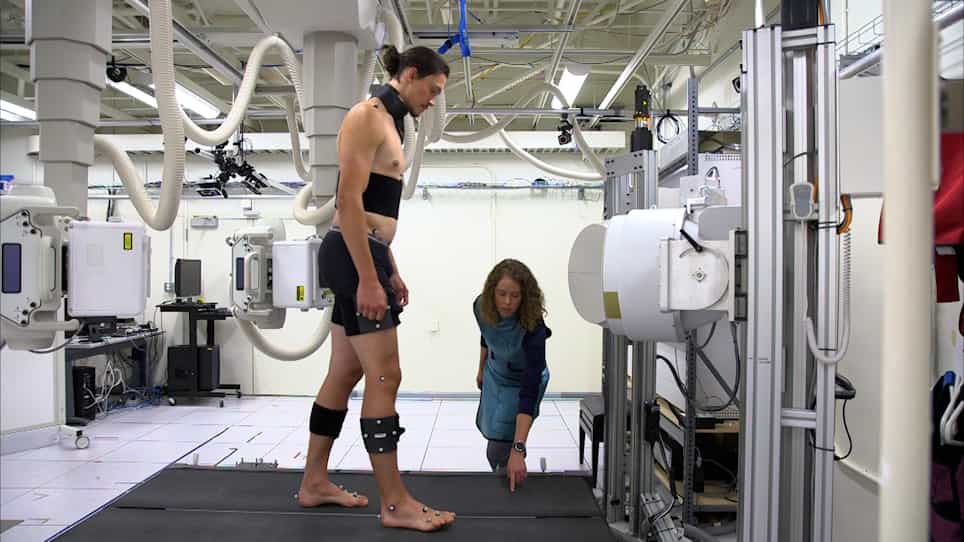
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Single-leg versus double-leg weight-bearing radiographs for coronal alignment assessment in patients with lower
Naya Pabla1, Kairo Noronha1, Sathyagopal Siddapureddy1
1Wayne State University School of Medicine and Detroit Medical Center, Detroit, MI, USA.

Introduction:
Accurate assessment of coronal lower extremity alignment is critical for surgical planning and postoperative evaluation following orthopedic trauma. Although double-leg (DL) standing radiographs remain the standard for alignment assessment, single-leg (SL) stance more closely approximates physiologic loading during gait. Prior studies have demonstrated differences between DL and SL alignment measurements in patients with osteoarthritis and elective deformity correction, but comparable data in orthopedic trauma patients are lacking.
Methods:
We performed a retrospective study of patients presenting to a Level I trauma center after lower extremity orthopedic surgery who underwent DL and SL standing radiographs during the same clinic visit. Lateral distal femoral angle, medial proximal tibial angle, and joint line convergence angle were measured by two blinded evaluators and averaged. The primary outcome was the proportion of limbs with at least one SL-DL difference exceeding the prespecified threshold (>3° for LDFA or MPTA; >2° for JLCA). Bland-Altman analyses assessed agreement, with patient-cluster bootstrap confidence intervals accounting for patients who contributed multiple limb encounters.
Results:
Forty-nine encounters from 32 patients contributed 91 limb-encounters (64 operated and 27 non-operated). Overall, 69.2% were within all prespecified thresholds, whereas 30.8% exceeded at least one threshold. The proportion exceeding at least one threshold was 40.6% in operated limbs and 7.4% in non-operated limbs. Bland-Altman biases were 0.00° for LDFA, -0.06° for MPTA, and 0.13° for JLCA; corresponding 95% limits of agreement were -5.46° to 5.46°, -4.26° to 4.15°, and -2.74° to 3.00°, respectively.
Discussion:
Average DL-SL differences were small, but nearly one-third of limbs exceeded at least one prespecified descriptive threshold. Because this study did not establish the accuracy of either imaging condition against an external reference standard, SL radiographs should be viewed as potentially complementary to, rather than superior to, DL radiographs in selected postoperative patients.