Related Experiment Video
Updated: Oct 15, 2026

3D-Neuronavigation In Vivo Through a Patient's Brain During a Spontaneous Migraine Headache
Published on: June 2, 2014
Plasma amylin levels in migraine and after erenumab treatment: A REFORM study
Rogelio Domínguez-Moreno1,2, Tyla I Alexander3, William K Karlsson1,2
1Department of Neurology, Center for Discoveries in Migraine and Danish Headache Center, Copenhagen University Hospital-Rigshospitalet, Copenhagen, Denmark.

Objective:
To investigate whether plasma amylin concentrations differ between adults with migraine and healthy controls (HCs) and whether baseline or longitudinal amylin levels are associated with treatment response to erenumab.
Background:
Amylin is a calcitonin family peptide closely related to calcitonin gene-related peptide, with overlapping receptor pharmacology, and has been implicated in migraine. Human provocation studies have shown that pramlintide, an amylin analogue, triggers migraine attacks, but it remains unclear whether plasma amylin distinguishes people with migraine from HCs, varies across migraine subtypes, predicts response to erenumab, or changes during treatment.
Methods:
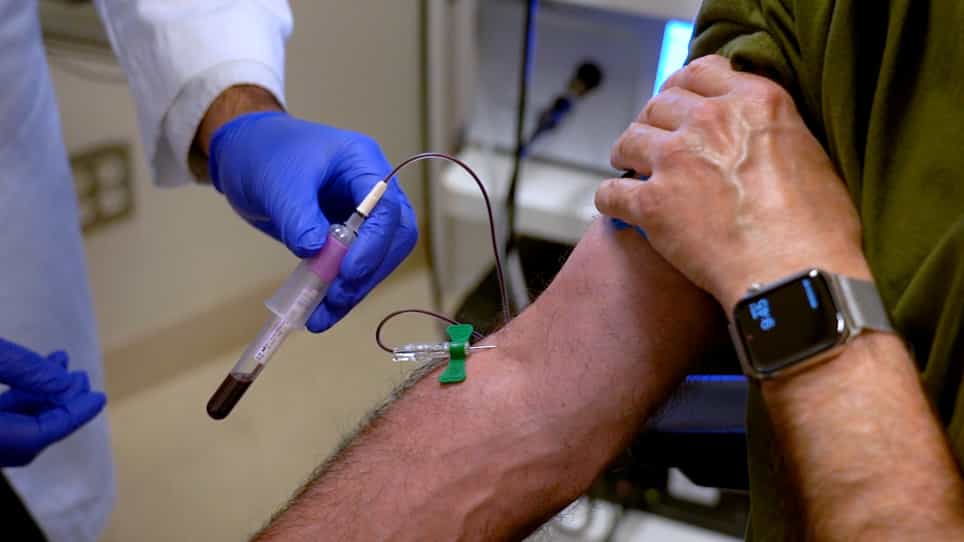
This prospective longitudinal analysis was conducted within the Registry for Migraine study at the Danish Headache Center (Copenhagen, Denmark). Adults with migraine (≥4 monthly migraine days) and age- and sex-similar HCs were enrolled between September 2020 and June 2022. Plasma samples were collected under standardized conditions at baseline and after 24 weeks of erenumab treatment (140 mg every 4 weeks). Treatment response was defined as a ≥50% reduction in monthly migraine days during weeks 13 to 24 compared with baseline. Plasma amylin was quantified from November 2023 to March 2024 using a competitive immunoassay that was selected after head-to-head kit validation, which included assessment of parallelism and spike recovery with human plasma.
Results:
A total of 121 adults with migraine and 63 HCs were enrolled; 100 participants with migraine completed 24 weeks of erenumab treatment and provided evaluable efficacy data. At baseline, plasma amylin concentrations were not significantly different between erenumab responders (n = 55) and nonresponders (n = 45) (9.0 ± 2.3 vs. 8.6 ± 1.7 ng/mL; p > 0.999), and concentrations of both groups were not statistically significantly different from HCs (9.2 ± 1.7 ng/mL; p > 0.999 and p = 0.220, respectively). At 24 weeks, plasma amylin concentrations did not differ significantly between responders and nonresponders (8.8 ± 2.2 vs. 8.3 ± 2.1 ng/mL; p = 0.676). In paired analyses (n = 100), plasma amylin levels did not change from baseline to week 24 (p = 0.208). Baseline plasma amylin concentrations did not differ across migraine subgroups (episodic vs. chronic, with aura vs. without aura, ictal vs. interictal) and were not associated with key clinical variables.
Conclusion:
Plasma amylin levels did not differ between adults with migraine and HCs, across clinically relevant migraine subgroups, or by response to erenumab. These findings do not support plasma amylin as a clinically useful disease or treatment-response biomarker and are consistent with the broader concept that migraine-relevant peptidergic signaling may be compartmentalized and not captured by peripheral venous blood sampling.