Related Experiment Video
Updated: Oct 15, 2026
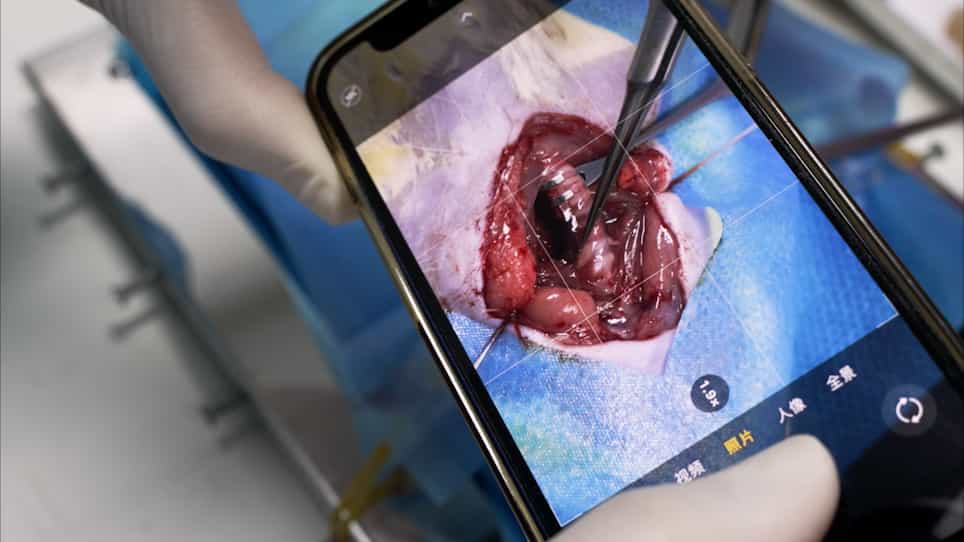
Establishment of a Simple and Effective Rat Model for Intraoperative Parathyroid Gland Imaging
Published on: August 17, 2022
Pathological characteristics rather than thyroid size predict incidental parathyroidectomy during thyroid surgery
Hasan Turgut Aydın1, Osman Gökhan Gökdere2, Ahmet Aydın3
1Private Practice, Çankaya/Ankara, Türkiye.

Background:
Incidental parathyroidectomy (IP) is a recognized event during thyroid surgery and may contribute to postoperative hypocalcemia and impaired parathyroid function. Although several clinical and operative factors associated with IP have been described, the contribution of thyroid size-related characteristics remains uncertain. This study aimed to evaluate the association between thyroid size-related parameters, clinicopathological characteristics, and the occurrence of IP.
Methods:
This retrospective cohort study included consecutive patients who underwent thyroidectomy between January 2021 and December 2025 at a tertiary referral center. Patients with primary parathyroid disease were excluded. Demographic, operative, pathological, and thyroid size-related variables, including dominant nodule diameter, thyroid specimen weight, and thyroid lobe dimensions, were analyzed. Associations with incidental parathyroidectomy were evaluated using univariable and multivariable logistic regression analyses. The multivariable model included age, sex, malignant thyroid pathology, Hashimoto thyroiditis, multinodular goiter/nodular hyperplasia, extent of thyroidectomy, and central neck dissection.
Results:
The study included 1,049 patients, of whom 125 (11.9%) had incidental parathyroidectomy. Dominant nodule diameter and thyroid specimen weight were not significantly associated with IP in available-case analyses. Increasing largest thyroid lobe diameter was associated with lower odds of IP in univariable analysis, although this association was not robust after adjustment. In the multivariable analysis, malignant thyroid pathology (adjusted odds ratio [aOR], 2.47; 95% confidence interval [CI], 1.49-4.09; p < 0.001), multinodular goiter/nodular hyperplasia (aOR, 2.31; 95% CI, 1.11-4.80; p = 0.025), and female sex (aOR, 1.88; 95% CI, 1.01-3.50; p = 0.045) were independently associated with higher odds of IP. Hashimoto thyroiditis (aOR, 1.53; 95% CI, 0.96-2.44; p = 0.072), central neck dissection (aOR, 1.55; 95% CI, 0.98-2.45; p = 0.058), and total/bilateral thyroidectomy (aOR, 0.60; 95% CI, 0.34-1.06; p = 0.079) were not independently associated with IP. The model demonstrated modest discrimination (AUC, 0.687) and adequate calibration (Hosmer-Lemeshow p = 0.445).
Conclusions:
Malignant thyroid pathology and multinodular goiter/nodular hyperplasia were independently associated with higher odds of incidental parathyroidectomy after adjustment for demographic and operative factors, including central neck dissection. Female sex was also associated with higher odds of IP, whereas Hashimoto thyroiditis did not retain statistical significance after multivariable adjustment. Thyroid size-related parameters showed no consistent independent association with IP. These findings should be interpreted cautiously given the retrospective design, incomplete data for some thyroid size-related parameters, and the possibility of residual confounding.

Related Concept Videos
 01:27
Hyperthyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:27
Goiter