Related Experiment Video
Updated: Oct 15, 2026
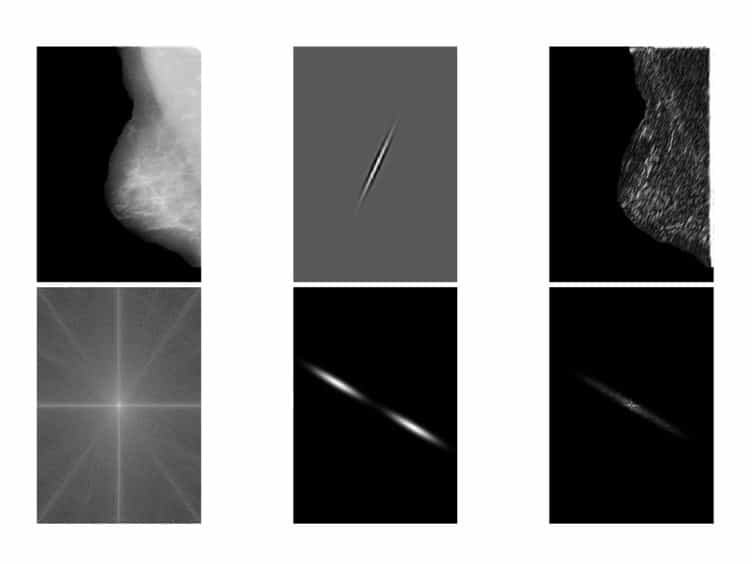
Detection of Architectural Distortion in Prior Mammograms via Analysis of Oriented Patterns
Published on: August 30, 2013
Comparison of two automated PGMI-based software tools for breast positioning quality assessment in DBT screening
Gisella Gennaro1, Stefano Trazzi2, Valentina Bordon3
1Veneto Institute of Oncology (IOV), IRCCS, Via Gattamelata 64, 35128, Padua, Italy. gisella.gennaro@iov.veneto.it.

Objective:
Automated "Perfect/Good/Moderate/Inadequate" (PGMI)-based tools have been developed to standardize breast positioning quality assessment, but their agreement remains uncertain. This study compared two automated software systems applied to the same digital breast tomosynthesis (DBT) screening cohort.
Materials And Methods:
This retrospective study included 778 women (3,112 views). Two software tools (SW1 and SW2) independently generated PGMI classifications and quality control (QC) feature outputs. Agreement was assessed using exact agreement and quadratic weighted κ. PGMI distributions were compared overall and by view, breast density, and breast volume. Associations between imaging parameters and PGMI scores were evaluated using Spearman correlation and ordinal regression.
Results:
SW2 assigned more Inadequate ratings than SW1 (10.9% vs. 0.7%, p < 0.001), whereas SW1 assigned more Perfect (21.9% vs. 12.9%, p < 0.001). Overall agreement was limited (48.2%; κ = 0.044, 95% CI 0.006-0.085). Agreement was higher in mediolateral oblique than in craniocaudal views. Across SW1-derived density strata, SW2 assigned more Inadequate and fewer Perfect ratings in higher density strata, with smaller differences observed at higher breast volume. Higher volumetric breast density and breast thickness were associated with lower PGMI scores, whereas breast volume showed positive associations, with the effect more pronounced for SW2. QC patterns differed markedly: SW1 most frequently flagged inframammary fold and posterior positioning criteria, whereas SW2 identified pectoral muscle and parenchymal coverage issues.
Conclusion:
Two automated PGMI systems showed limited agreement and systematic differences in classification behavior. These findings indicate a lack of interchangeability and support the need for harmonized definitions and validation frameworks for automated image quality assessment.
Key Points:
Question Standardized automated assessment of breast positioning quality in digital breast tomosynthesis remains lacking, limiting comparability between different PGMI-based software tools in screening. Findings Two automated PGMI systems showed limited agreement and systematic differences across views, breast density, breast volume, and acquisition-related parameters in DBT screening. Relevance statement Automated PGMI systems are not interchangeable and reflect different operational definitions of image quality. Harmonized standards and rigorous validation are required before implementation in clinical quality assurance workflows.
