Related Experiment Video
Updated: Oct 15, 2026
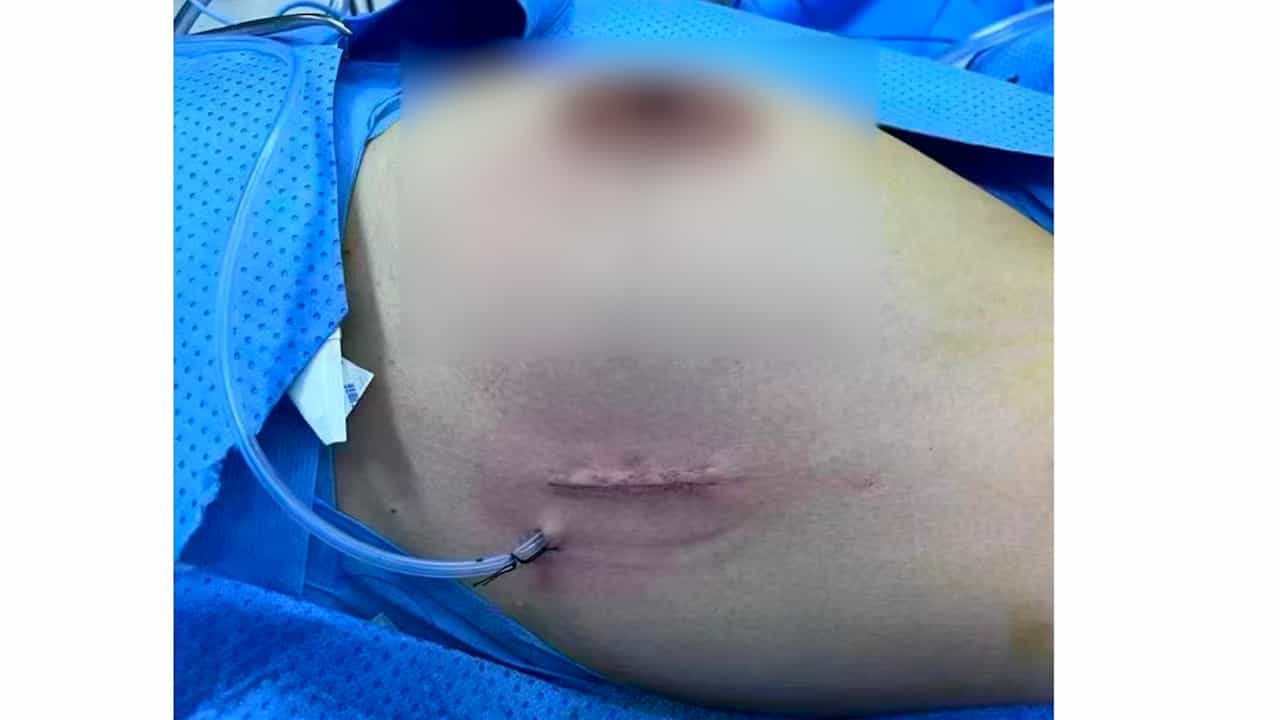
Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Preoperative MRI for pleomorphic lobular carcinoma in situ: Implications for surgical management
Sara Grossi1, Lauren Longo1, Sadie Munter1
1University of California San Diego School of Medicine Department of Surgery, La Jolla, CA, USA.

Background:
Pleomorphic lobular carcinoma in situ (PLCIS), a more aggressive variant of classic LCIS (CLCIS), demonstrates higher rates of upgrade to invasive carcinoma at surgical excision. Mammography may underestimate disease extent, whereas MRI may delineate lesions due to sensitivity.
Methods:
Our institutional pathology database was queried for patients diagnosed with PLCIS on core needle biopsy (CNB) from 2002 to 2025 who underwent surgical excision. Preoperative MRI and MRI-guided biopsies were reviewed. Radiologic, pathologic, surgical, and outcome data were collected. Proportions were summarized with 95% confidence intervals. Fisher's exact test assessed associations between categorical variables, and Bayesian logistic regression evaluated the relationship between calcification size and malignant upgrade.
Results:
Preoperative MRI was performed in 94.7% (18/19) of patients. Among these, 61.1% (11/18) underwent additional biopsy, identifying additional LCIS in 72.7% (8/11), benign findings in 18.2% (2/11), and malignancy in 9.1% (1/11). Mammographic PLCIS presentation included calcifications (26.3%), mass (5.3%), both (31.6%), or neither (36.8%). Among cases with calcifications, 45.5% (5/11) upgraded to malignancy. Increasing calcification size was associated with higher upgrade probability (OR 1.32 per cm, 95% CrI: 0.68-2.97), increasing from 35% at 0.5 cm to 52% at 3.0 cm. The overall upgrade rate was 47.4% (9/19).
Conclusion:
Preoperative MRI in PLCIS frequently prompts additional biopsies, often detecting further LCIS rather than malignancy. Calcification extent predicts upgrade, and the high upgrade rate supports surgical excision after CNB diagnosis.
