Related Experiment Video
Updated: Oct 15, 2026
A Reference Broth Microdilution Method for Dalbavancin In Vitro Susceptibility Testing of Bacteria that Grow Aerobically
Published on: September 9, 2015
Daptomycin for enterococcal bloodstream infections and endocarditis: reconciling clinical evidence, susceptibility
Alejandro Díez-Vidal1, Pilar Vizcarra2, Carlos M Oñoro-López3
1Infectious Diseases Unit, Department of Internal Medicine, La Paz University Hospital, Madrid, Spain; Hospital La Paz Institute for Health Research (IdiPAZ), La Paz University Hospital, Madrid, Spain; CIBER de Enfermedades Infecciosas (CIBERINFEC), Carlos III Health Institute, Madrid, Spain.

Abstract:
Despite the absence of US Food and Drug Administration or European Medicines Agency approval, randomised trials, and harmonised susceptibility guidance, daptomycin has become indispensable for the treatment of serious enterococcal bloodstream infections and endocarditis. The Clinical and Laboratory Standards Institute assigns Enterococcus faecium a susceptible dose-dependent category (≤4 mg/L, 8-12 mg/kg per day) and Enterococcus faecalis a susceptible breakpoint (≤2 mg/L, 6 mg/kg per day), whereas the European Committee on Antimicrobial Susceptibility Testing sets no clinical breakpoint, citing insufficient evidence. We argue that this misalignment between evidence and regulation is itself a potential source of patient harm, through persistent underdosing and inconsistent interpretive guidance. Observational data link 10-12 mg/kg per day with lower mortality in patients infected with vancomycin-resistant E faecium. Even so, appropriate dosing frequently does not attain the pharmacodynamic target, because target attainment depends less on the administered dose than on the isolate's minimum inhibitory concentration (MIC), which current methods cannot reliably determine. Any-grade creatine phosphokinase elevation rises modestly with dose in the largest registry but is inconsistent elsewhere, with a clearer signal of marked elevation at the highest doses. We propose a pragmatic framework (≥8 mg/kg per day for E faecium, 10-12 mg/kg per day in vancomycin-resistant disease, MIC-informed dose selection, β-lactam combination in endocarditis, and weekly creatine phosphokinase monitoring) and call for therapeutic drug monitoring, harmonised breakpoints, prospective studies, and molecular resistance detection.
Related Concept Videos
 01:25
Clinical Significance of Antibiotic Resistance
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:15
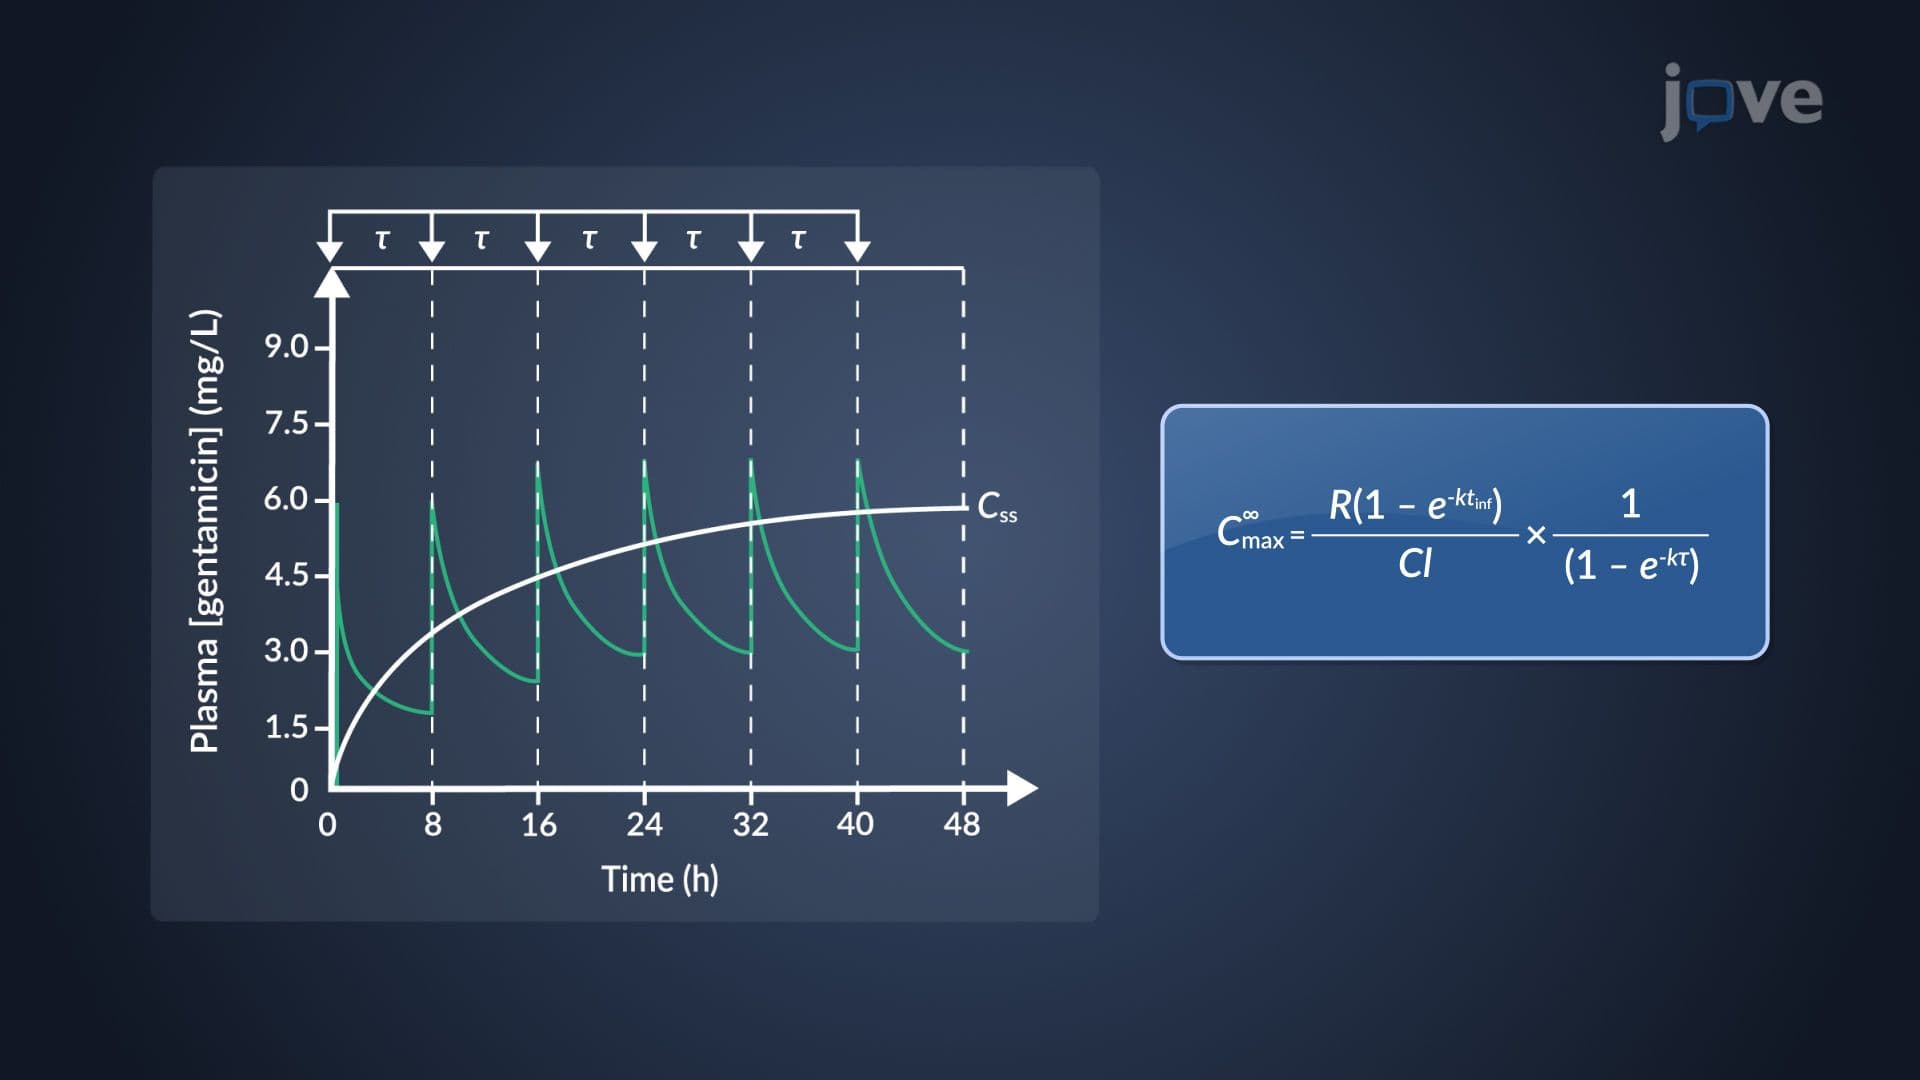
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:24
Automated Microbial Diagnostics
 01:20
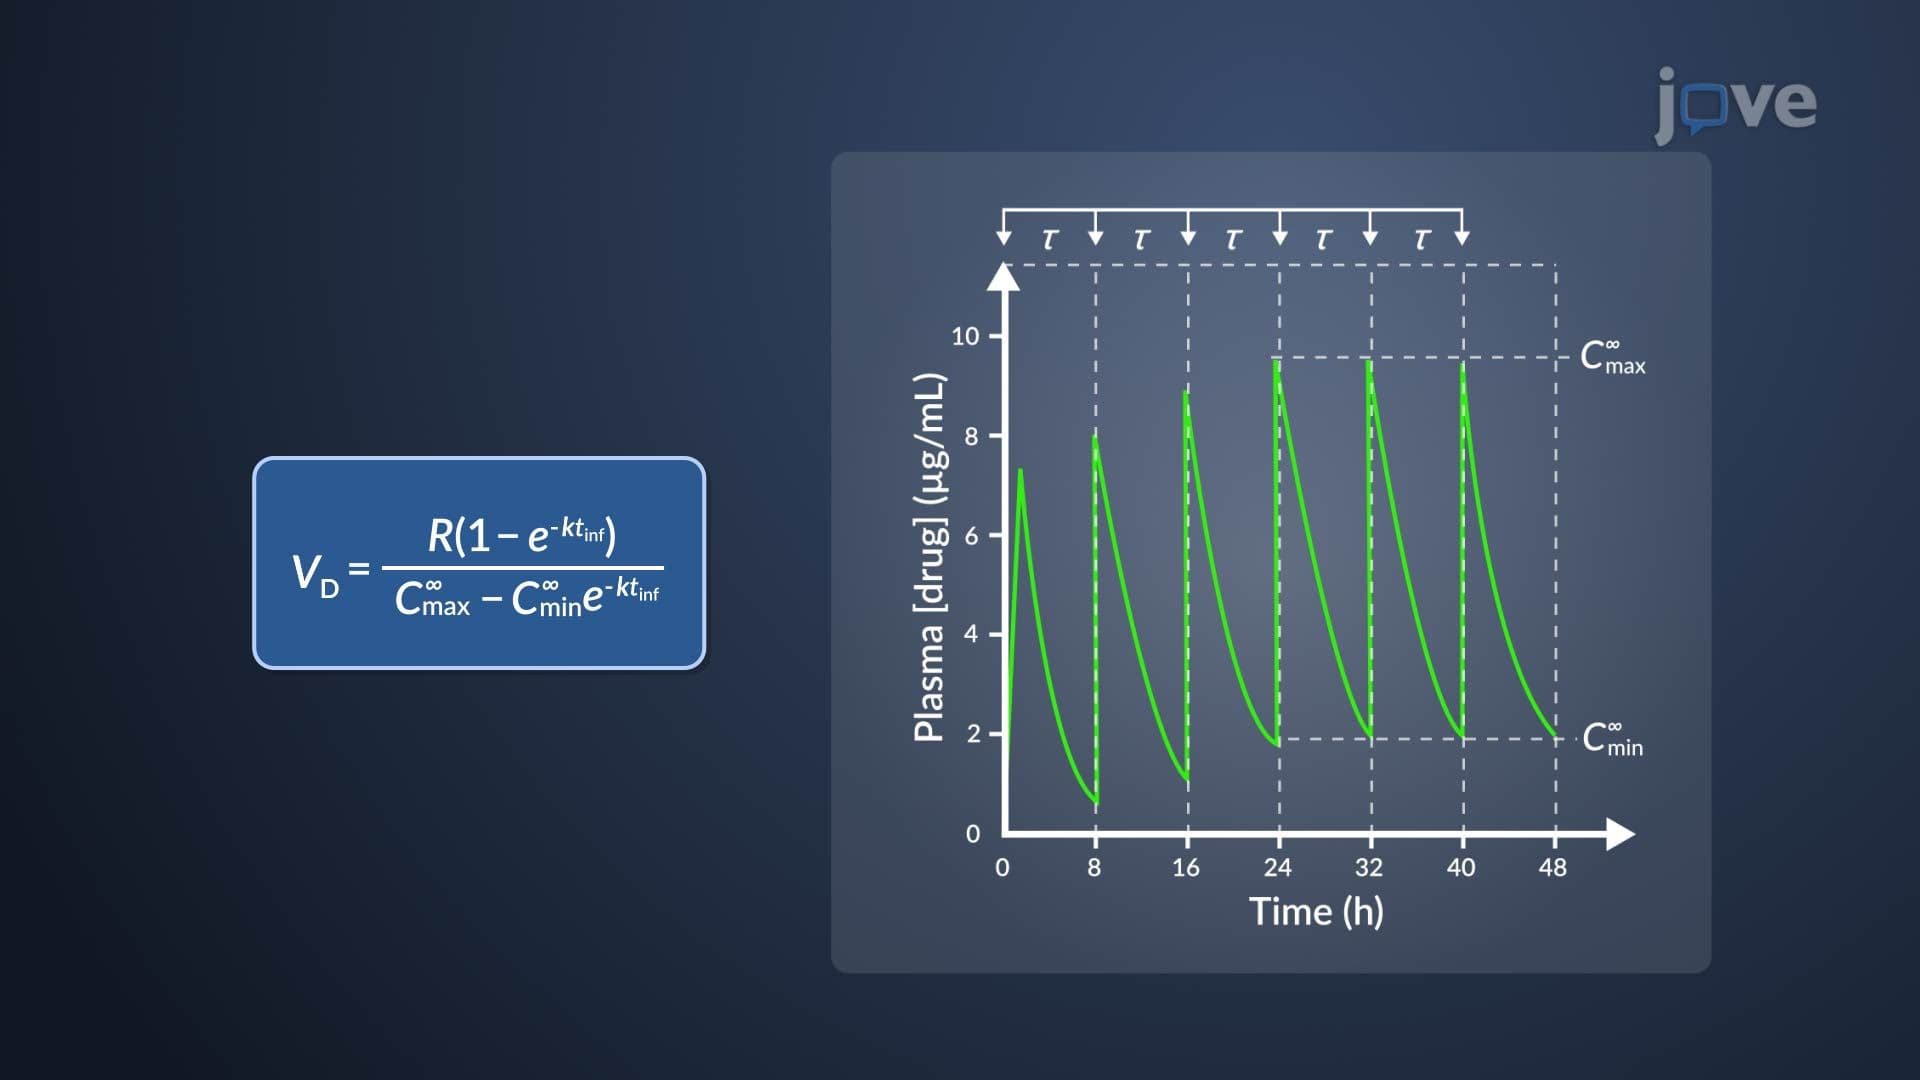
Estimation of k and VD of Aminoglycosides
 01:25
Mechanism of Antibiotic Resistance in MRSA