Related Experiment Video
Updated: Oct 15, 2026
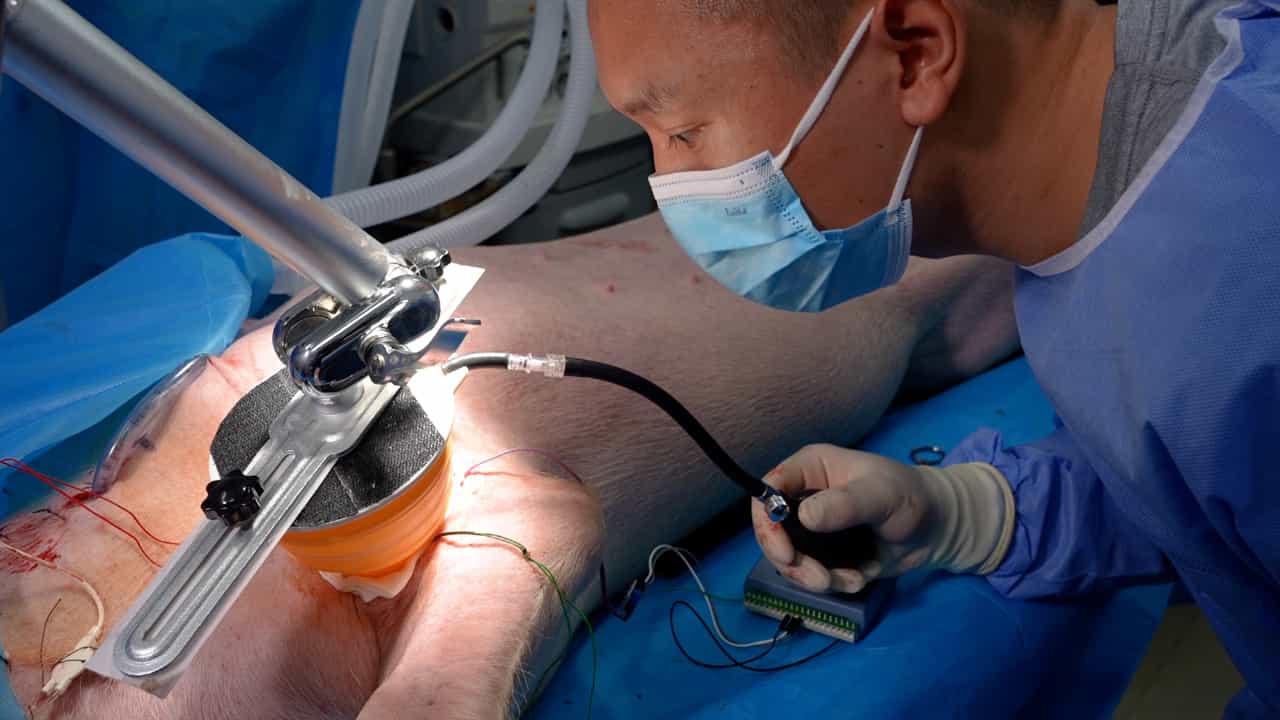
A New Hybrid Quantitative Evaluation Model for Axillary Junctional Hemorrhage in Swine
Published on: December 6, 2024
Expert Perspectives on Disruptive Bleeding and Hemostasis Optimization in Primary and Revision Total Hip
Michael A Mont1, Antonia F Chen2, Chase W Smitterberg1
1The Rubin Institute for Advanced Orthopedics, Sinai Hospital of Baltimore, Baltimore, Maryland.

Background:
Despite advances in perioperative blood management, disruptive bleeding after total hip arthroplasty (THA) remains clinically important, given associations with hematoma, wound complications, infection, reoperation, and resource utilization. The term "disruptive bleeding" has emerged from recent outcomes and health-economic work to describe bleeding-related events that alter care, but has not been standardized as a clinical entity in THA. This survey explored whether this construct aligns with arthroplasty surgeons' perspectives and identified domains for future validation.
Methods:
A structured expert-opinion survey was distributed to 14 arthroplasty surgeons experienced in primary and revision THA. Domains included definitions of disruptive bleeding, risk factors, intraoperative diffuse oozing, postoperative drainage, escalation triggers, and topical hemostatic agent use. Responses included categorical selections, Likert-style ratings, and free-text comments. Descriptive statistics and exact denominators were reported. An agreement of at least 70% was used descriptively to identify high-agreement items.
Results:
All respondents supported characterizing disruptive bleeding as a composite of care-altering events, including symptomatic or management-changing hemoglobin decline greater than three g/dL, transfusion, prolonged drainage, return to the operating room, embolization, and readmission. The most frequently identified bleeding risk factors were thrombocytopenia and anticoagulant use (n = 14 of 14), followed by coagulopathy and liver disease (n = 12 of 14). Escalation triggers included suspected arterial bleeding (n = 14 of 14), enlarging hematoma (n = 13 of 14), hemodynamic instability (n = 13 of 14), neurovascular compromise (n = 13 of 14), and persistent drainage (n = 12 of 14). Only four of 14 supported routine topical hemostatic agent use in primary THA, whereas seven of 14 supported selective consideration in revision THA. Disagreement remained regarding timing definitions and drainage thresholds.
Conclusions:
Disruptive bleeding in THA was viewed as a composite construct defined by care-altering events rather than numeric blood-loss measures. These findings are exploratory, hypothesis-generating, and identify candidate domains for future multidisciplinary and prospective validation.
