Related Experiment Video
Updated: Oct 15, 2026
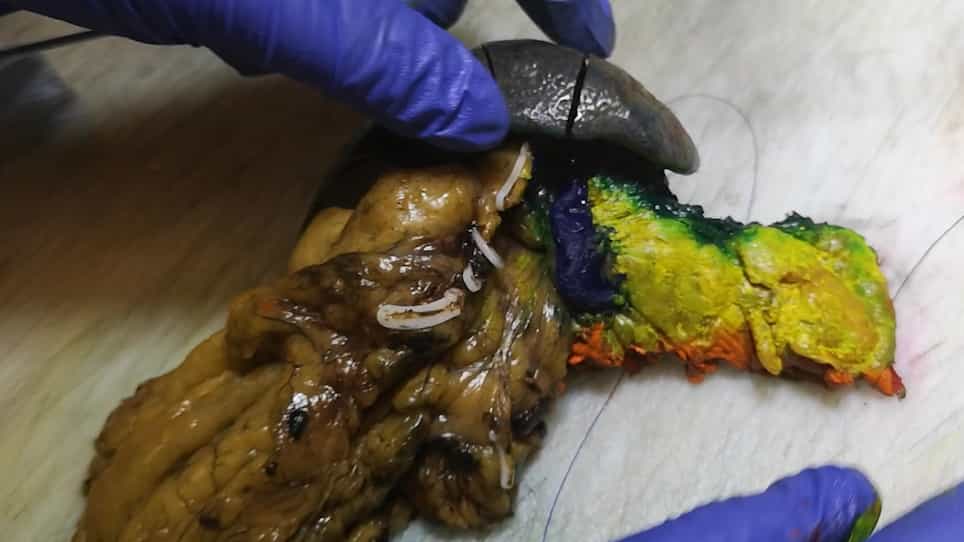
DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Transitioning from template-based groin dissection to dynamic sentinel node biopsy in penile cancer: Prospective
Gagan Prakash1, Sarah Shaikh2, Amandeep Arora1
1Department of Surgical Oncology, Tata Memorial Hospital, Homi Bhabha National Institute, Mumbai, India.

Purpose:
Dynamic sentinel lymph node biopsy (DSNB) offers accurate inguinal staging in clinically node-negative (cN0) penile cancer (PeCa), but implementation requires multidisciplinary expertise and standardization. We evaluated the feasibility and diagnostic accuracy of a standardized dual-tracer DSNB protocol during transition from modified/superficial inguinal lymph node dissection (MILD/SILD).
Methods:
In this prospective, non-randomized phase II study, 20 patients with intermediate- or high-risk cN0 PeCa underwent DSNB followed by MILD and SILD in both groins. DSNB used 99mTc-nanocolloid and indocyanine green (ICG). Sentinel nodes were identified using lymphoscintigraphy/SPECT-CT, gamma-probe and near-infrared fluorescence, and assessed by frozen section. Final SILD pathology served as the reference standard for calculating the false-negative rate (FNR).
Results:
Forty groins were evaluated. DSNB successfully identified sentinel nodes in 37/40 (92.5%) groins; ICG identified nodes in 36 (90%) compared with 28 (70%) for 99mTc. Five groins contained metastatic sentinel nodes, all detected by DSNB, yielding 100% sensitivity and 0% FNR. In 4/37 (10.8%) successful procedures, sentinel nodes lay outside the MILD template. Median sentinel node yield was 4 versus 12 nodes with SILD. Median drain duration and hospital stay were 21 and 3 days, respectively. Eleven patients (55%) had no complications; grade 2 and 3a complications occurred in 20% and 25%, respectively. After median follow-up of 34 months, no inguinal nodal recurrences occurred.
Conclusion:
A standardized dual-tracer DSNB protocol was feasible and demonstrated high diagnostic accuracy during phased implementation at a tertiary cancer centre. Initial validation alongside template dissection may facilitate safe adoption, particularly in settings without centralized PeCa services.