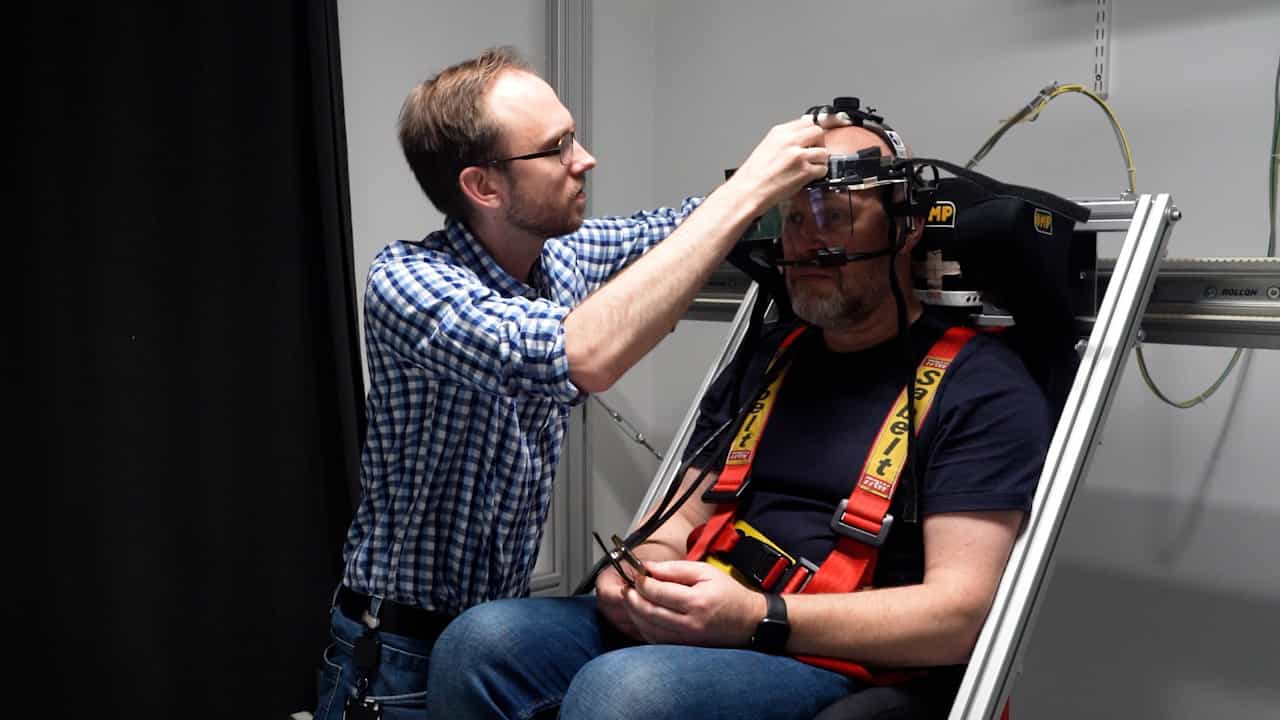
Related Experiment Video
Updated: Oct 15, 2026

Testing of all Six Semicircular Canals with Video Head Impulse Test Systems
Published on: April 18, 2019
Hemi-see-saw nystagmus with superimposed pendular oculopalatal tremor: case report and systematic review
Jesus Gutierrez-Arratia1, Fiorella Rivas-Sarmiento2, Christoper A Alarcon-Ruiz2,3
1Department of Neuro-Ophthalmology, Instituto Nacional de Ciencias Neurológicas, Jirón Ancash 1271, Lima, Peru. neuroremjesus@gmail.com.

Background:
Hemi-see-saw nystagmus (HSSN) is an uncommon subtype, characterized by elevation and intorsion of one eye with contralateral depression and extorsion, typically in a jerk pattern. It is associated with unilateral lesions of the interstitial nucleus of Cajal and the medial longitudinal fasciculus, both of which are involved in the ocular tilt reaction (OTR). Although its association with oculopalatal tremor (OPT) has been described, it is rare.
Methods:
We performed a systematic review of seven databases on HSSN, extracting data on demographics, etiology, lesion location, oculomotor findings, nystagmus pattern, outcomes, and in addition we presented a representative case.
Results:
A systematic review of seven databases identified 18 reports comprising 57 cases of HSSN or closely related dissociated vertical-torsional nystagmus, including the present index case. The mean age was 56.2 ± 16.3 years, and 63.2% of patients were male. Ischemic stroke was the most frequent etiology (75.4%), followed by hemorrhagic stroke (14.0%). Less frequent causes included Chiari I malformation, demyelinating/inflammatory disease, cavernous malformation, ataxia with oculomotor apraxia type 2, Joubert syndrome, and brainstem encephalitis (1.8% each). Jerk nystagmus predominated (82.5%), whereas pendular nystagmus was identified in 17.5%, exclusively in the setting of OPT or inferior olivary hypertrophy. Among jerk HSSN cases, the pontine tegmentum was the most frequent lesion site (63.8%), with INO present in all pontine cases and OTR in 90.0%. Complete resolution was reported predominantly in cases associated with INO, whereas lack of improvement was confined to OPT-related cases, with one exception of spontaneous resolution after 20 years. We describe a 30-year-old man with a pontomedullary arteriovenous malformation presenting with pendular HSSN, right one-and-a-half syndrome, gaze-evoked nystagmus, OTR, incomplete Horner syndrome, and OPT.
Conclusions:
HSSN is an uncommon nystagmus, most often vascular in origin and frequently involving the pontine tegmentum. While it usually presents with a jerk waveform, association with OPT may produce a pendular phenotype, suggesting a distinct brainstem-cerebellar mechanism. Larger anatomically and oculographically characterized series are needed to clarify structure-function correlations and prognosis.