Related Experiment Video
Updated: Oct 15, 2026
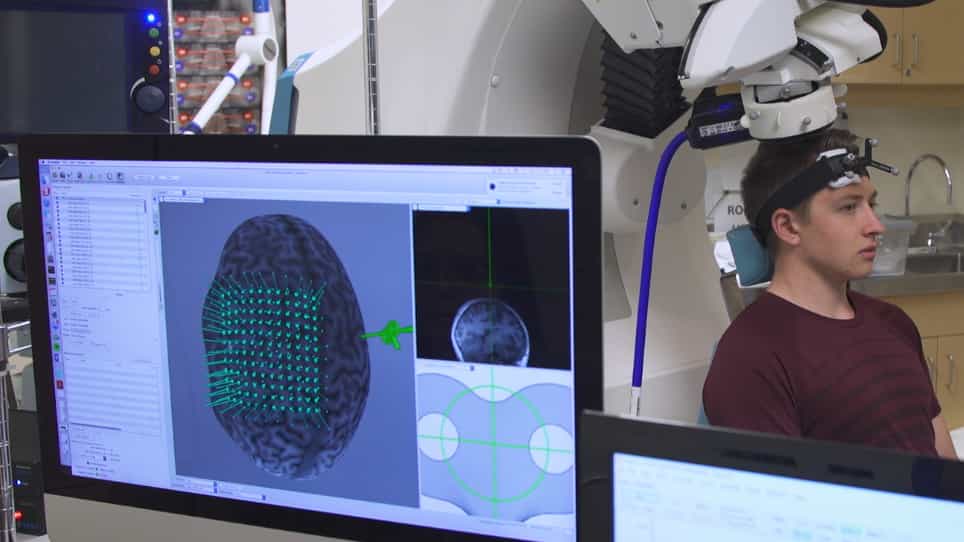
Non-Invasive Modulation and Robotic Mapping of Motor Cortex in the Developing Brain
Published on: July 1, 2019
Brain-computer interfaces in pediatric populations: research advances, application challenges, and future directions
Shan Wang1, Qian Wu2, Qiaorong Lei3
1School of Nursing, Shaoyang University, Shaoyang, Hunan, China.

Abstract:
Brain-computer interfaces (BCIs) establish direct communication pathways between the brain and external devices. Leveraging the unique neuroplasticity of the developing brain, BCIs have emerged as a novel rehabilitative technology for children with neurodevelopmental disorders, including cerebral palsy, autism spectrum disorder (ASD), attention deficit hyperactivity disorder (ADHD), and perinatal brain injury. This review comprehensively examines five major BCI paradigms-P300, motor imagery (MI), steady-state visual evoked potentials (SSVEP), functional near-infrared spectroscopy (fNIRS), and multimodal hybrid systems-with respect to their pediatric adaptability, technical limitations, and optimization strategies. We summarize the existing evidence across four key clinical applications: augmentative and alternative communication (AAC), motor function rehabilitation, ADHD attention training, and ASD social-emotional intervention. Key intrinsic (cognitive and physiological) and extrinsic (device and environmental) variables affecting BCI performance in children are analyzed, along with general optimization approaches including personalized parameter tuning, pre-training neurofeedback, and lightweight hardware modifications. Furthermore, we examine multilayer barriers to pediatric BCI adoption, including user experience, clinical workforce readiness, translational pathways, and child-specific ethical considerations. Preliminary evidence suggests that non-invasive BCIs can be feasibly used in children above 5 years of age, although this finding is based on short-term studies with small sample sizes and requires further validation through larger longitudinal trials. However, the immature pediatric brain, short attention spans, and low device tolerance preclude direct translation of adult BCI systems. While evidence is more established for AAC and motor rehabilitation in cerebral palsy, large-scale long-term data are still lacking for ADHD and ASD interventions. Future efforts should prioritize child-specific lightweight wearable devices, multicenter longitudinal trials, immersive integration with virtual reality (VR) and social robots, standardized clinical service frameworks, and ethical guidelines for invasive pediatric BCIs, thereby facilitating the transition of BCI technology from laboratory to clinical and home settings and maximizing its value in promoting neurodevelopmental plasticity in children with special needs.

