Related Experiment Video
Updated: Oct 16, 2026
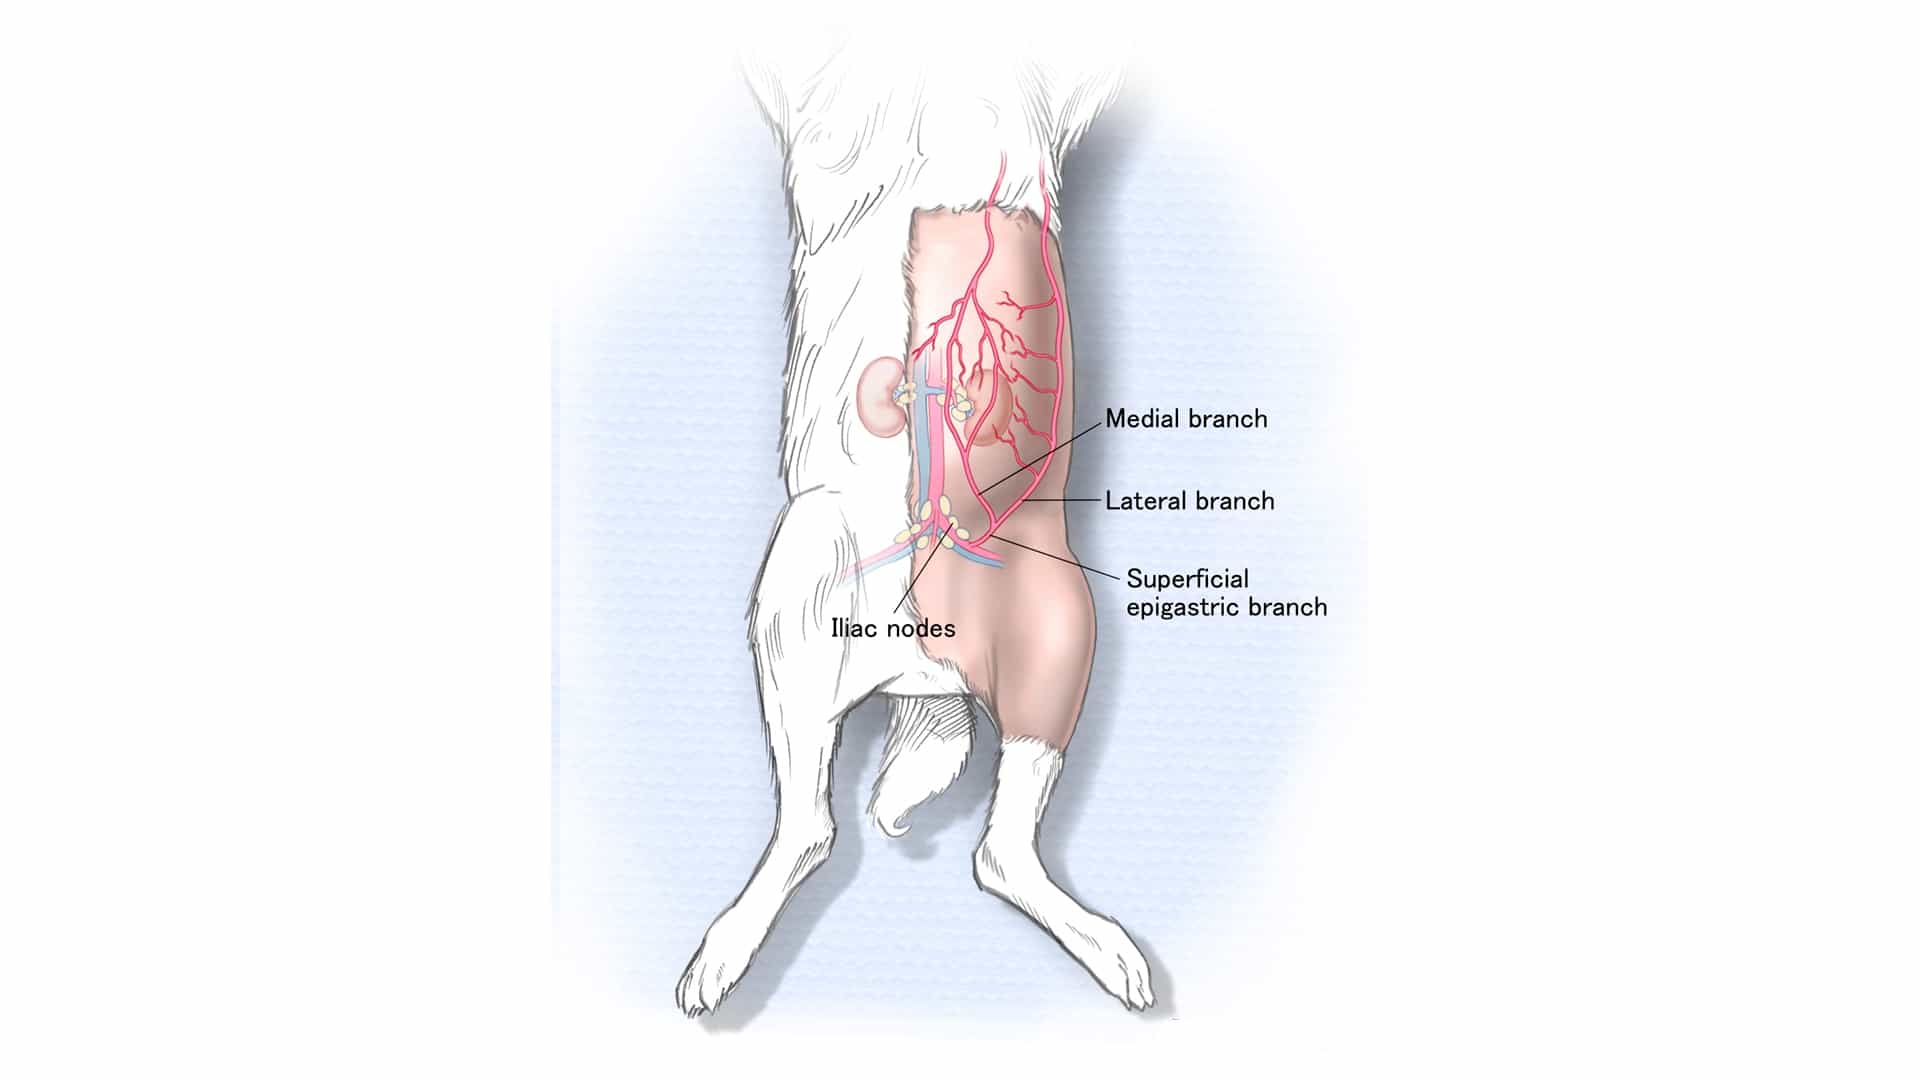
An Experimental Human DIEP Flap Model to Investigate Preservation Strategies for Vascularized Composite Allografts and Free Flaps
Published on: December 5, 2025
Associations of Deep Inferior Epigastric Perforator Flap Weight with Postoperative Complications and Revisions
Joyce X Cui1, Eric Zeng1, Mary L Duet2
1From the Department of Plastic and Reconstructive Surgery, Wake Forest University School of Medicine, Winston-Salem, NC.

Background:
The deep inferior epigastric perforator (DIEP) flap has emerged as the preferred method for autologous breast reconstruction. There is growing interest in identifying factors associated with complications. This study investigates the relationship between DIEP flap weight and postoperative outcomes using a large, DIEP-specific database.
Methods:
We performed a retrospective review of 757 patients (757 oncologic flaps) with a history of breast cancer who underwent DIEP flap reconstruction from 2017 to 2024 at 2 medical sites. Demographics, medical history, operative course, and complications were analyzed.
Results:
Body mass index (BMI) strongly correlated with flap weight (r = 0.79), and both correlated with complication rates (P < 0.001, P < 0.001). Patients were grouped by BMI (<25, 25-30, 30-35, and >35 kg/m2) and subsequently by those with and without complications within a mean of 9.6 months from reconstruction. Adjusted logistic regression revealed that flap weight was associated with higher odds of overall complications [odds ratio (OR) 1.17], minor complications (OR 1.18), fat necrosis (OR 1.27), and wound dehiscence (OR 1.29) in BMI 30-35 group. Heavier flaps were also associated with skin necrosis in the BMI less than 25 group (OR 2.31) and hematoma in the BMI 25-30 group (OR 1.37). Further stratification by flap weight showed trends toward higher rates of minor complications, skin necrosis, and wound dehiscence, although associations were inconsistent across strata.
Conclusions:
Flap weight correlated with complications in select BMI subgroups, most notably BMI 30-35, although findings were inconsistent across groups. Further study is needed to better understand the multifactorial relationship between flap weight and postoperative outcomes.