Related Experiment Video
Updated: Oct 16, 2026
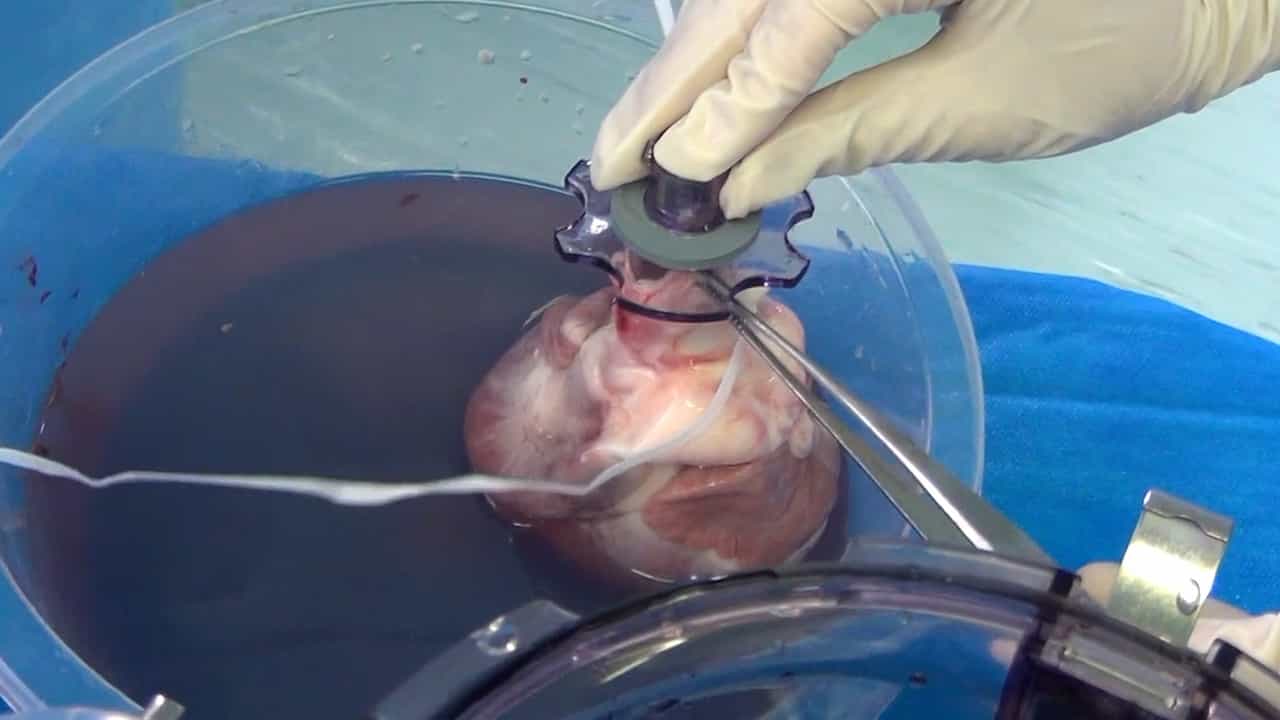
Innovative Strategies for Organ Preservation in Heart Transplantation: Uniform Cooling Preservation and Ex-situ Normothermic Perfusion
Published on: November 28, 2025
[Acute heart failure-management during the first 120 min : Approach for early stabilization and decongestion]
M Buerke1, H Lemm2, A Amerini3
1Medizinische Klinik II, Kardiologie, Angiologie, Internistische Intensivmedizin, St.-Marien-Krankenhaus Siegen, Kampenstr. 51, 57072, Siegen, Deutschland. mbuerke@gmail.com.

Abstract:
Acute heart failure (AHF) is among the most common causes of emergency department, intermediate care, and intensive care unit admission and remains associated with substantial early mortality despite advances in contemporary therapy. The first 120 min of management are particularly critical, as this period determines not only respiratory and hemodynamic stabilization, but also trigger identification, decongestion strategy, and the foundation for subsequent prognostic improvement. This CME article provides a practical, phenotype-based approach to the early management of AHF. The proposed strategy is centered on the rapid classification of patients according to congestion ("wet" vs. "dry") and perfusion ("warm" vs. "cold") status. Stabilization and diagnostic work-up must occur simultaneously. Early assessment should focus on identifying acute coronary syndrome, clinically relevant arrhythmias, hypertensive crisis, pulmonary embolism, structural heart disease, and infectious triggers. In addition to clinical examination, electrocardiography, blood gas analysis, and biomarkers, point-of-care ultrasound with lung ultrasound and focused echocardiography play a pivotal role in the first-line evaluation. From a therapeutic perspective, early noninvasive ventilation in cardiogenic pulmonary edema, prompt vasodilation in hypertensive presentations, and effective decongestion with intravenous loop diuretics constitute the core interventions. In cases of insufficient response, escalation strategies such as sequential nephron blockade or selective use of vasoactive agents should be considered. Structured reassessment at short intervals is essential to detect persistent congestion, evolving hypoperfusion, inadequate therapeutic response, or overlooked differential diagnoses. The article emphasizes that successful acute management must already establish the transition toward guideline-directed long-term therapy during the first hours of hospitalization, including early initiation of evidence-based heart failure medication once hemodynamic stabilization has been achieved.
Related Concept Videos
 01:30
Heart Failure V: Medical Management
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:26
Acute Coronary Syndrome V: Nursing Management
 01:22
Heart Failure VI: Adjunct Therapies
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:30
Heart Failure VII: Nursing Interventions