Related Experiment Video
Updated: Oct 16, 2026
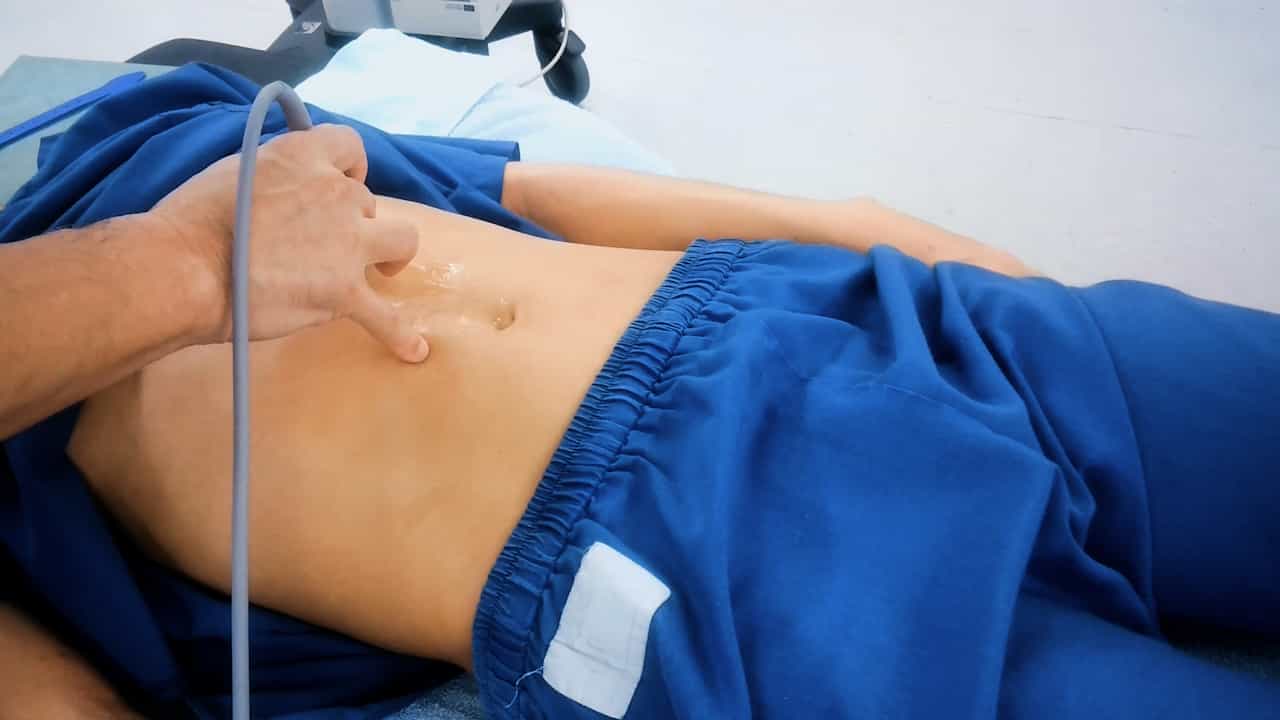
Multimodality Diagnosis of Mesenteric Ischemia
Published on: July 21, 2023
Embolic and atherosclerosis-associated acute mesenteric ischemia: distinct clinical entities with different outcomes
Dominik Peter1, Annette Thurner2, Amos Kroth1
1Department of General, Visceral, Transplantation, Vascular and Pediatric Surgery; University Hospital Wuerzburg, Wuerzburg, Germany.

Background:
Acute arterial occlusive mesenteric ischemia is associated with high mortality. Embolic and atherosclerosis-associated forms differ in vascular pathology, collateral circulation, and ischemic tolerance, which may contribute to differences in clinical presentation and outcomes. This study compared clinical presentation, treatment strategies, and outcomes between embolic acute mesenteric ischemia (EAMI) and atherosclerosis-associated acute mesenteric ischemia (AAMI).
Methods:
This retrospective single-center study included all consecutive patients diagnosed with acute arterial occlusive mesenteric ischemia between January 2004 and March 2026. Patients were stratified into EAMI and AAMI groups. The primary endpoint was in-hospital mortality. Secondary analyses evaluated clinical presentation, imaging findings, and treatment strategies. Multivariable logistic regression was performed to assess the association between etiology and in-hospital mortality.
Results:
Of 216 patients identified, 190 were included in the final analysis (EAMI, 56.8%; AAMI, 43.2%). Patients with EAMI more frequently presented with sudden-onset abdominal pain, whereas AAMI was characterized by acute-on-chronic symptoms and longer symptom-to-treatment intervals. Imaging findings indicative of advanced bowel ischemia, including pneumatosis intestinalis and portomesenteric venous gas, as well as bowel resection at initial surgical exploration, were more common in AAMI (40.2% vs. 21.3%, p = 0.005). In-hospital mortality was higher in AAMI than in EAMI (75.6% vs. 60.2%, p = 0.025). In multivariable analyses, EAMI was independently associated with lower in-hospital mortality (adjusted odds ratios 0.41-0.47; both p < 0.05).
Conclusion:
EAMI and AAMI represent distinct clinical entities with different presentations and outcomes. AAMI is associated with delayed presentation, more advanced ischemic injury at diagnosis, and higher in-hospital mortality. Etiology is independently associated with in-hospital mortality and should be considered in risk stratification and the design of future studies.

Related Concept Videos
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:15
Ischemic Stroke l: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:30
Acute Coronary Syndrome I: Introduction
 01:26
Transient Ischemic Attack l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology