Related Experiment Video
Updated: Oct 16, 2026
Retinal Pigment Epithelium Transplantation in a Non-human Primate Model for Degenerative Retinal Diseases
Published on: June 14, 2021
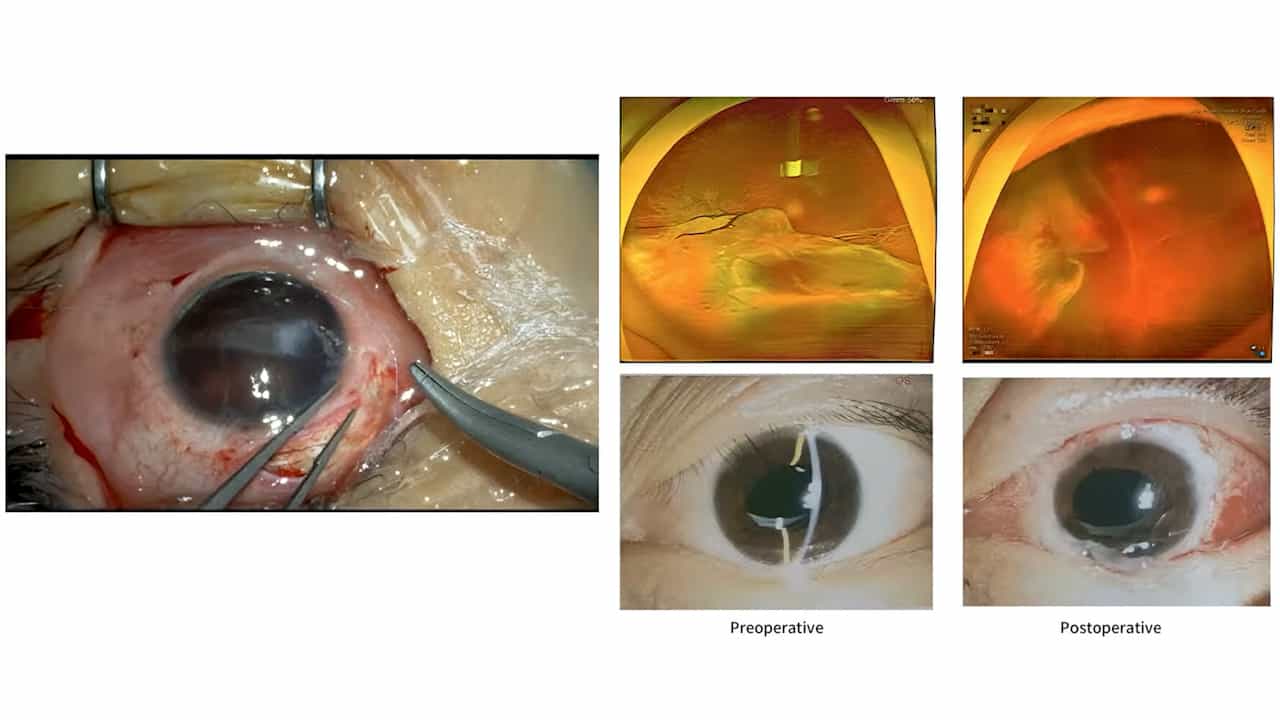
Outcomes of Complex Retinal Detachment Repair with Proliferative Vitreoretinopathy Grade C using the Cincinnati
Denis Huang1, Jack E Feist2, Sloane A McTavish2
1Cincinnati Eye Institute; Department of Ophthalmology, University of Cincinnati.

Purpose:
To analyze the outcomes of an intravitreal methotrexate protocol in eyes that underwent complex retinal detachment (RD) repair for proliferative vitreoretinopathy (PVR).
Design:
Retrospective non-randomized comparative cohort study at a single tertiary ophthalmic center.
Participants:
Patients who underwent vitrectomy for RD with PVR grade C between 2019 and 2025.
Methods:
Three hundred eyes were included and divided into a treatment group of 150 eyes and a comparison cohort of 150 eyes. Patients in the treatment group received the Cincinnati Methotrexate (MTX) protocol, which delivers MTX as a 40 mg/500mL intraocular balanced salt solution infusion during vitrectomy and 200 to 400 μg intravitreal injections at post-operative weeks 1, 3, 6 and 10. Patients in the comparison cohort did not receive perioperative MTX. Multivariable regression analysis was performed to evaluate anatomic and visual outcomes. Minimum follow up interval was 6 months.
Main Outcome Measures:
The primary outcome measures were single surgery success rate (SSSR), postoperative PVR rate, postoperative visual acuity (VA) and final retinal attachment status. Secondary outcomes included adverse events related to MTX.
Results:
Eyes in the MTX group had higher odds of single surgery success (OR 5.15, 95% CI 2.77-10.15, p < 0.001) and lower odds of postoperative PVR (OR 0.15, 95% CI 0.08-0.26, p < 0.001), both of which remained significant with multivariable analysis. The MTX group had lower odds of final anatomic failure (OR 5.21, 95% CI 1.12-49.82, p = 0.03), which was not significant with multivariable analysis. Controlled for tamponade choice and lens status, the MTX group had superior VA at postoperative month 1 (p < 0.001), month 3 (p < 0.001), month 6 (p < 0.01), and month 12 (p = 0.02). There was no difference in serious ocular adverse events of special interest assessed between the two groups.
Conclusion:
A Cincinnati MTX regimen comprised of an intraoperative intraocular infusion and four intravitreal injections at postoperative weeks 1, 3, 6 and 10 was associated with higher single surgery success, lower postoperative PVR, and superior VA in complex RD repair with PVR grade C compared to a contemporaneous consecutive comparator cohort.