Related Experiment Video
Updated: Oct 16, 2026
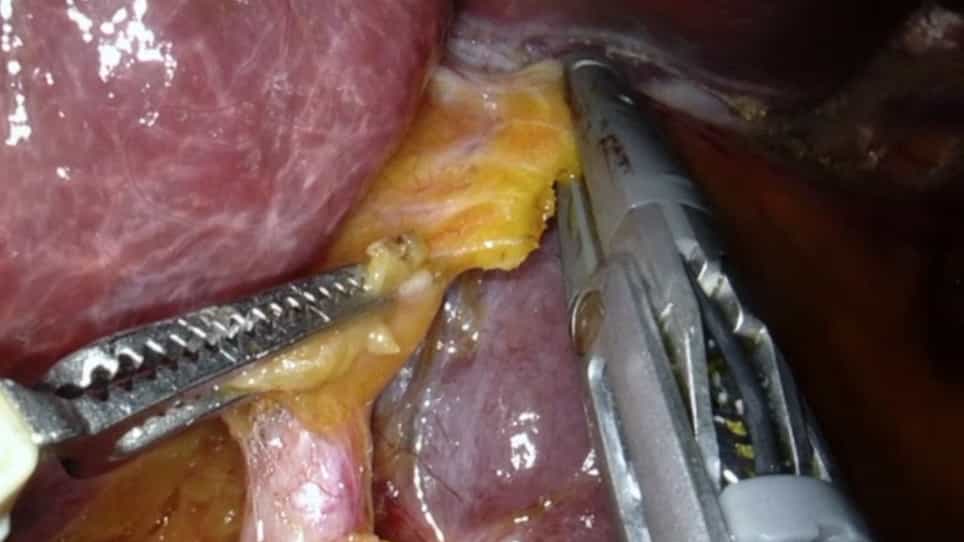
Robotic Left Hepatectomy using Indocyanine Green Fluorescence Imaging for an Intrahepatic Complex Biliary Cyst
Published on: June 24, 2022
Robotic liver resection learning curves stratified by IWATE criteria
Yee L Cheah1, Michelle E McCarthy2, Mohamed E Akoad2
1Department of Surgery, J.C. Walter Jr. Transplant Center, Houston Methodist Hospital, 6550 Fannin St, Sm 1601, Houston, TX, USA. ycheah@houstonmethodist.org.

Background:
Characterizing the learning curve of robotic hepatectomy is important to facilitate safe adoption; however, variability in case complexity can confound the interpretation of non-stratified learning curve analyses. This study evaluated learning curves for robotic hepatectomy stratified according to procedural difficulty.
Methods:
We included consecutive robotic hepatectomies performed by a single surgical team at two institutions between 2017 and 2025. Cases were classified as low-, intermediate-, advanced-, and expert-level based on the IWATE criteria. Cumulative sum (CUSUM) analysis of operative time was performed to define the learning curve for each complexity level.
Results:
Among a total of 174 cases (31 low-, 70 intermediate-, 34 advanced-, and 39 expert-level), the median age was 63 years, and 57% of patients were female. Mean operative time correlated with case complexity, ranging from 165 min in low-level cases to 368 min in expert-level cases (p<0.0001). Throughout the study period, lower-complexity resections continued to be performed while progressively more complex procedures were incorporated. CUSUM analysis demonstrated distinct competency thresholds: 14 cases for low-difficulty procedures and 29 cases for intermediate-level cases. The learning curves were shorter for advanced- and expert-level resections: 17 and 23 cases, respectively. The overall non-stratified learning curve stabilized at 89 cases. The 90-day major morbidity rate was 4%, and overall complication rates were comparable between the pre- and post-competency cohorts.
Conclusions:
IWATE-stratified analysis identified distinct learning curves across procedural complexity levels. The shorter competency thresholds observed for higher-complexity resections suggest that experience gained during lower-complexity procedures accelerates proficiency in complex resections, resulting in overlapping rather than sequential learning curves. These metrics should be interpreted as estimates derived from a real-world practice with an evolving case mix, rather than successive milestones, and may provide a practical framework for implementing robotic hepatectomy.