Related Experiment Video
Updated: Oct 17, 2026

Pre-Chiasmatic, Single Injection of Autologous Blood to Induce Experimental Subarachnoid Hemorrhage in a Rat Model
Published on: June 18, 2021
Pituitary Apoplexy Presenting as a Transient Ischemic Attack: An Endocrine Emergency
Mariana Marques1, Joana Couto2, Joana Urbano2
1Internal Medicine, Hospital Vila Franca de Xira, Vila Franca de Xira, PRT.

Abstract:
Pituitary apoplexy (PA) is an endocrine emergency caused by hemorrhage or infarction of a pituitary adenoma and occurs more frequently in males and patients with macroadenomas. It typically presents acutely with headache, visual disturbances, or impaired consciousness. Focal neurological deficits are uncommon and may be mistaken for a primary cerebrovascular event. Acute secondary adrenal insufficiency is a major contributor to hemodynamic instability and mortality. A 67-year-old man with arterial hypertension, type 2 diabetes mellitus, dyslipidemia, and chronic obstructive pulmonary disease presented with sudden presyncope, followed by dysarthria and right upper limb weakness. He had a five-month history of headache that had worsened abruptly three days before presentation. On admission, he was febrile (38.5 °C), hypotensive (89/49 mmHg), and tachycardic, with dysarthria, mild right central facial palsy, and grade 4 motor strength in the right upper limb (National Institutes of Health Stroke Scale (NIHSS) score of 3). Computed tomography (CT) angiography revealed an enlarged pituitary gland and 90% calcified stenosis of the left internal carotid artery. The focal neurological deficits resolved completely within approximately 30 minutes of arrival, during fluid resuscitation. However, hypotension persisted despite the administration of 2 L of crystalloid. A 200 mg bolus of hydrocortisone was administered for suspected adrenal insufficiency, resulting in prompt hemodynamic recovery. Baseline cortisol was <1 µg/dL, with an inappropriately low adrenocorticotropic hormone (ACTH) concentration. Magnetic resonance imaging (MRI) confirmed a pituitary macroadenoma with recent hemorrhage, without evidence of infarction on diffusion-weighted imaging. The episode was interpreted as a hemodynamic transient ischemic attack precipitated by PA-associated acute secondary adrenal insufficiency. Antiplatelet therapy, initiated for a presumed primary cerebrovascular event, was discontinued, and the patient was managed conservatively. Follow-up confirmed persistent panhypopituitarism, including central diabetes insipidus, requiring long-term hormone replacement. PA may mimic a cerebrovascular event through direct vascular compromise or, as in this case, hypotension superimposed on pre-existing carotid artery disease. Empirical hydrocortisone treatment should not be delayed pending laboratory confirmation of adrenal insufficiency. Early MRI is essential to establish the diagnosis and guide management before antithrombotic or endovascular treatment is initiated when a sellar abnormality is identified.

Related Concept Videos
 01:26
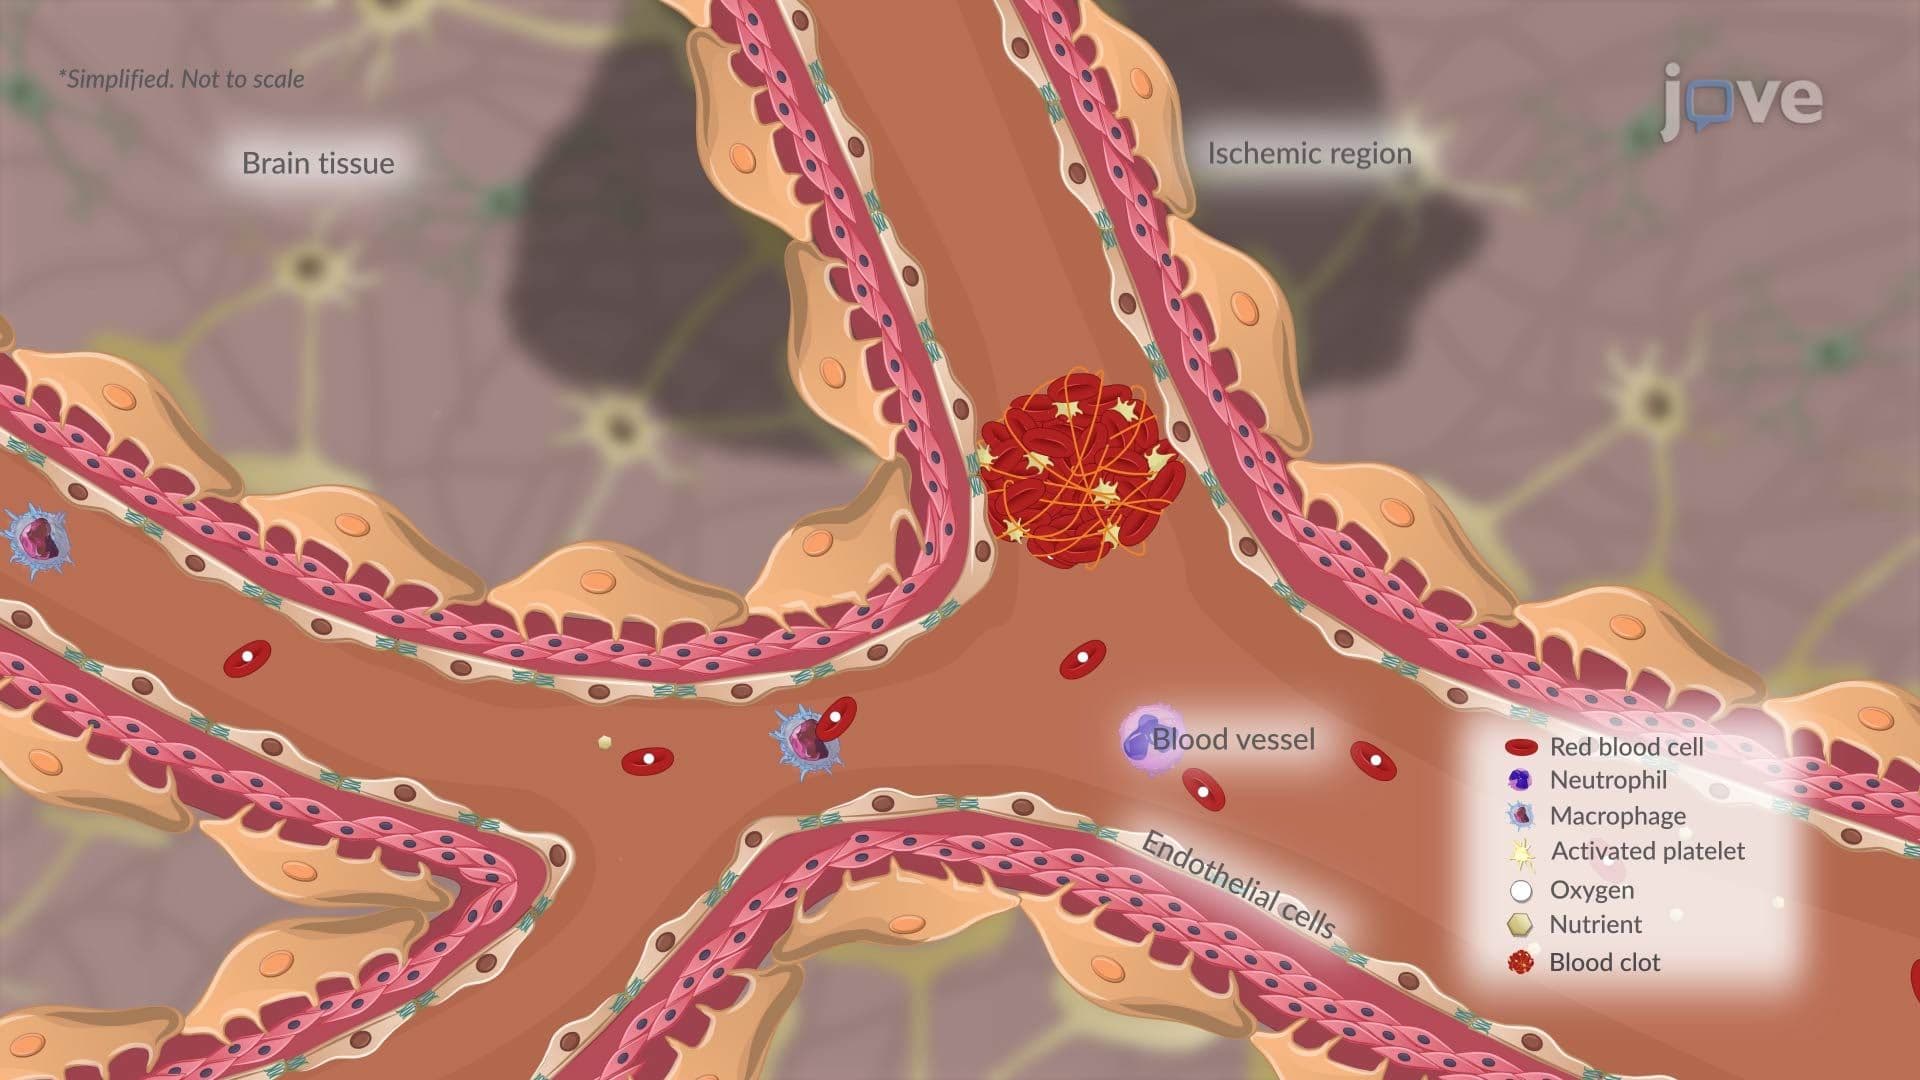
Transient Ischemic Attack l: Introduction
 01:21
Cytotoxic Edema: Pathophysiology
 01:15
Ischemic Stroke l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology
 01:20
Seizures l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology