Related Experiment Video
Updated: Oct 17, 2026
Continuous Telemetric In Utero Tracheal Pressure Measurements in Fetal Lambs
Published on: December 22, 2023
Congenital Lung Malformations and Quantitative Assessment of Infant Tracheal-Bronchial Dimensions
Antonio Mario Bulfamante1, Ugo Maria Pierucci2, Alessandro Campari3
1Paediatric Otolaryngology Unit, Department of Paediatric Surgery, "V. Buzzi" Children Hospital, Milan, Italy.

Background:
Congenital lung malformations (CLMs) are heterogeneous developmental anomalies caused by disrupted airway branching morphogenesis, but whether the central airways are also involved remains unclear. We quantified infant tracheobronchial dimensions in CLMs and compared them with published infant reference values.
Methods:
This retrospective single-center study included 81 of 94 infants with CLMs assessed for eligibility. Exclusions were secretions preventing measurement (n = 3), motion artifacts (n = 7), unavailable preoperative computed tomography (CT) (n = 2), and missing diagnosis (n = 1). Chest CT was performed before 1 year of age and before surgery. Tracheobronchial cross-sectional areas (CSAs) were measured at five standardized levels, natural-log transformed, and compared with expected values from the Chalwadi et al. equations for age 0 completed years. Holm correction was applied to the five overall comparisons; diagnostic subgroup and regression analyses were exploratory.
Results:
Diagnoses were congenital pulmonary airway malformation (CPAM, n = 40), pulmonary sequestration (n = 27), congenital lobar emphysema (n = 7), bronchial atresia (n = 6), and bronchogenic cyst (n = 1). Compared with expected values, the overall cohort showed larger proximal tracheal CSA (loge 3.22 vs. 3.11, p = 0.021; Holm-adjusted p = 0.042), distal tracheal CSA (3.33 vs. 3.21, p = 0.010; Holm-adjusted p = 0.030), right main bronchus (2.91 vs. 2.72, p = 0.007; Holm-adjusted p = 0.028), and left main bronchus (2.57 vs. 2.41, p = 0.002; Holm-adjusted p = 0.010), with no mid-tracheal difference (3.20 vs. 3.26; p = 0.233; Holm-adjusted p = 0.233). CPAM showed enlargement of the proximal trachea (p = 0.037), distal trachea (p = 0.022), right main bronchus (p = 0.017), and left main bronchus (2.62 vs. 2.41, p = 0.017). Pulmonary sequestration showed no significant differences. Congenital lobar emphysema showed reduced mid-tracheal CSA (2.86 vs. 3.26, p = 0.014). Bronchial atresia showed enlarged proximal trachea (p = 0.027), distal trachea (p = 0.027), and left main bronchus (p = 0.017).
Conclusions:
CLMs are associated with quantifiable tracheobronchial alterations during infancy, with distinct subtype-specific patterns. These findings suggest that CLMs may represent disorders of global airway development rather than isolated parenchymal abnormalities.
Related Concept Videos
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:28
Physical Assessment of the Respiratory Tract I: Health History
Subjective Data
Subjective data provides vital information about the patient's health history and symptoms. This data is typically collected through interviews in which patients describe their experiences, symptoms, and concerns.
Health history and key...
 01:15
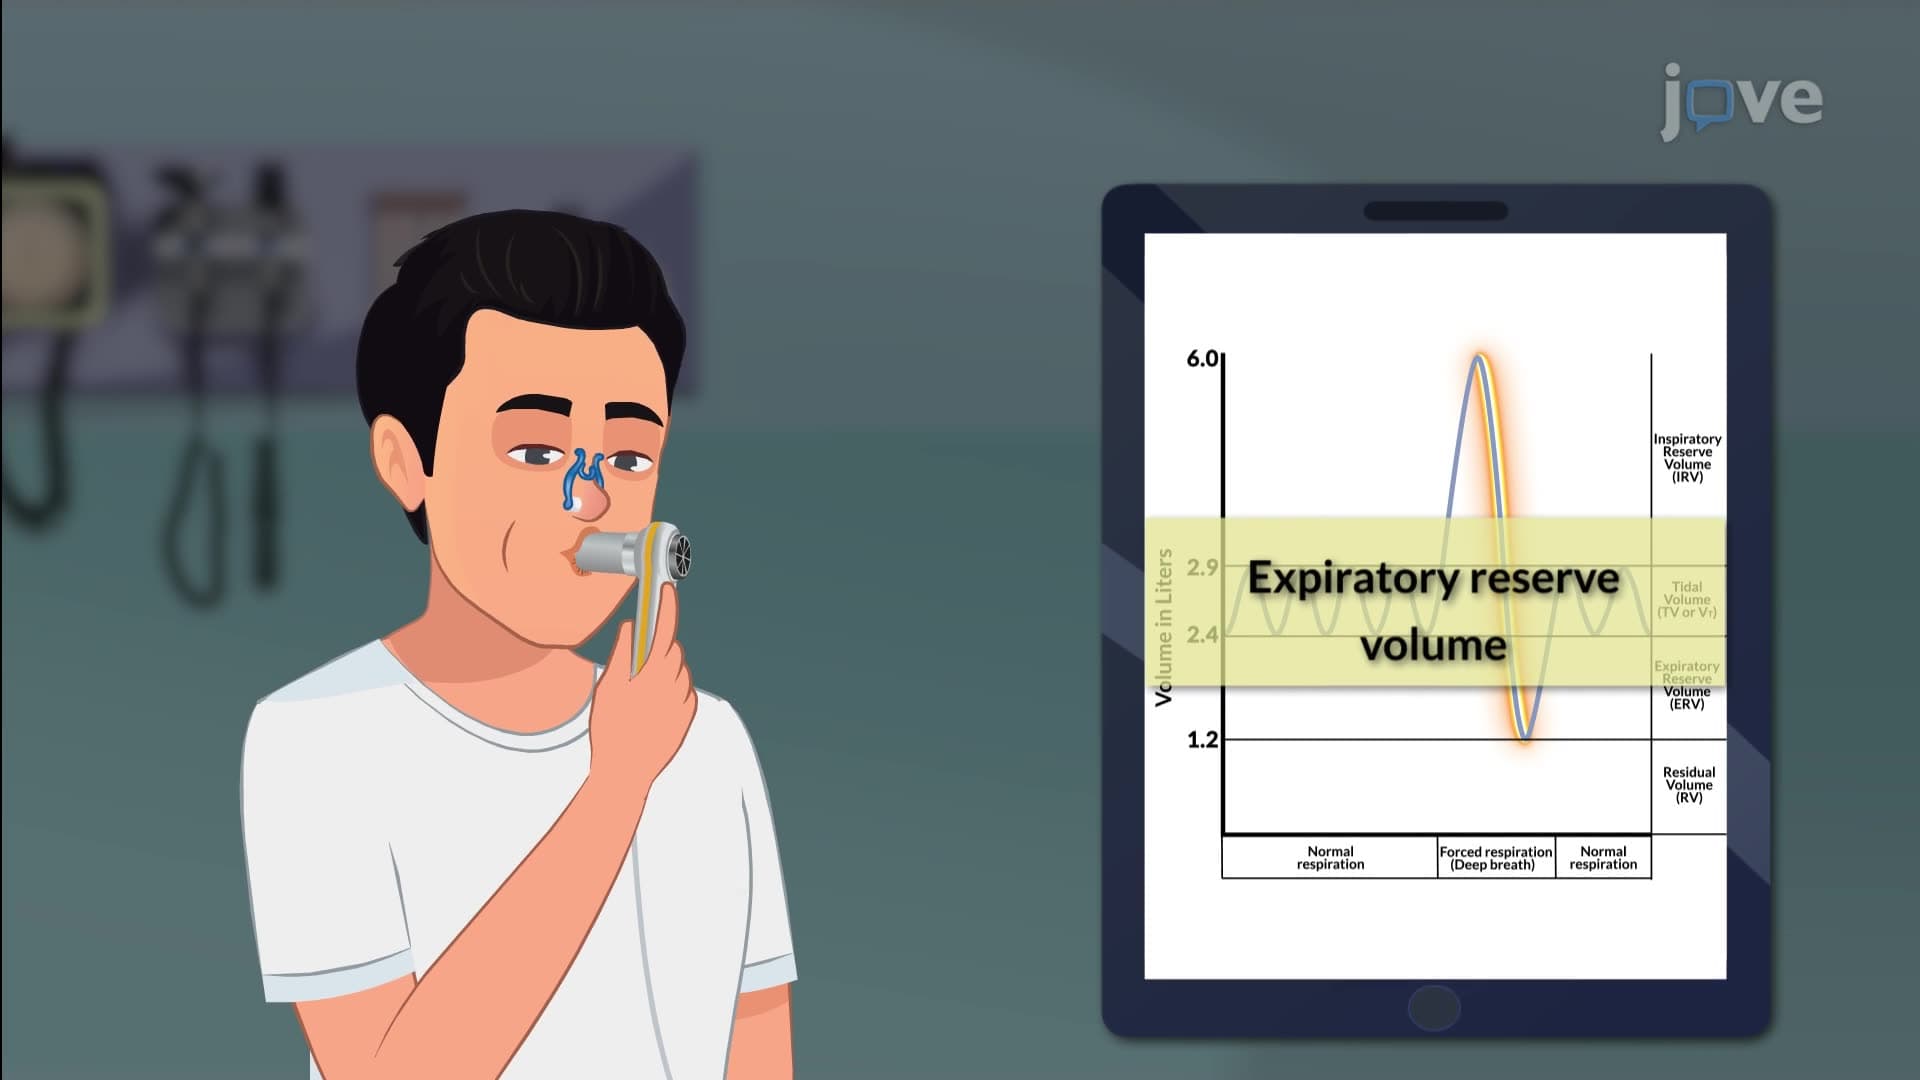
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
Physical Assessment of the Respiratory Tract II: Palpation
Thoracic Palpation
Thoracic palpation detects tenderness, masses, lesions, respiratory excursions, and vocal fremitus. The nurse assesses...
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:31
Anatomy of Respiratory System II: Lower Respiratory Tract
The Larynx
It is located between the pharynx and the trachea, acts as a passageway for air, and hosts several critical structures, such as the epiglottis, vocal cords, and glottis. The epiglottis acts as a gateway, guiding food to the...