Related Experiment Video
Updated: Oct 17, 2026
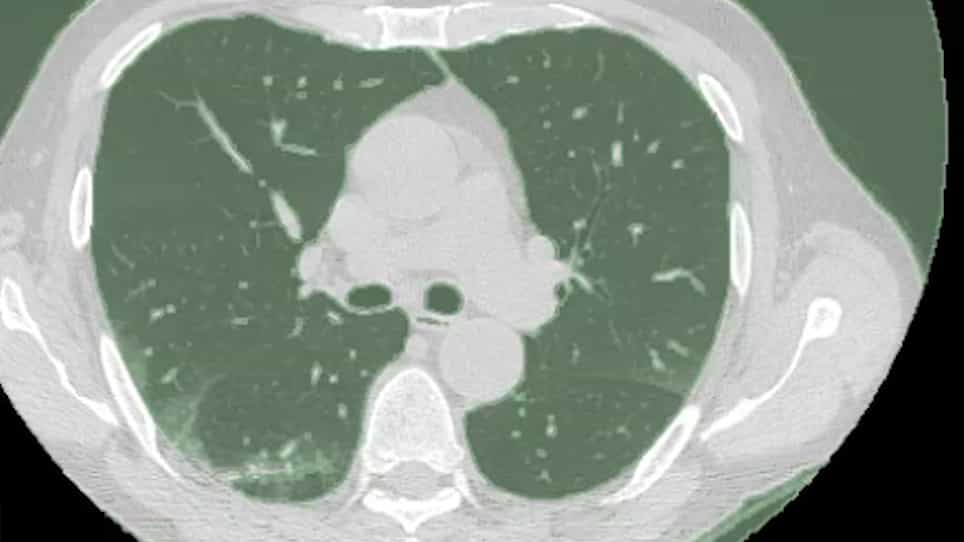
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Expert intuition vs. Algorithmic clustering: Mapping radiological subtypes in pulmonary sarcoidosis
Justyna Sobczak1, Adam J Białas1, Joanna Miłkowska-Dymanowska1
1Department of Pneumology, Medical University of Lodz, Lodz, Poland.

Background:
Pulmonary sarcoidosis is a heterogeneous granulomatous disease with a broad spectrum of clinical and radiological manifestations. While the traditional Scadding classification based on chest radiography remains a cornerstone of disease staging, it provides limited information regarding parenchymal involvement and poorly correlates with functional impairment. High-resolution computed tomography (HRCT) offers superior sensitivity in detecting subtle and early interstitial changes, yet standardized HRCT-based classification systems for sarcoidosis remain underdeveloped.
Aim:
This study aimed to propose and validate a novel HRCT-based classification of pulmonary sarcoidosis grounded in expert consensus, to assess its relationship with clinical symptoms, pulmonary function, and quality of life, and to compare it with data-driven radiological groupings obtained through cluster analysis.
Methods:
The study population included patients with confirmed pulmonary sarcoidosis managed at a tertiary referral center, either as inpatients or outpatients. HRCT scans were evaluated using a modified version of the previously published questionnaire, capturing 22 radiological features per lung lobe. Based on characteristic imaging patterns, four expert-defined subtypes were proposed: (1) Lymphonodal, (2) Disseminated-Nodular, (3) Central, and (4) Fibrotic. Symptom burden was assessed using the Fatigue Assessment Scale (FAS) and the Sarcoidosis Health Questionnaire (SHQ). Spirometric and gas transfer parameters (FEV1, FVC, TL,CO) were recorded. Statistical analyses included ANOVA, Spearman's correlation, and hierarchical clustering (Ward's method with Euclidean distances), with Cohen's kappa used to evaluate concordance between classification systems.
Results:
Four distinct HRCT subtypes were identified through expert assessment, each reflecting varying degrees and distributions of parenchymal involvement. These subtypes differed significantly in clinical and functional presentation. The fibrotic subtype demonstrated the most severe functional impairment, with the highest prevalence of abnormal spirometry and diffusion deficits. In contrast, the lymphonodal subtype exhibited preserved lung function and minimal symptomatology. The Van den Heuvel radiological severity score showed strong correlation with radiological subtype and was significantly associated with FEV1, FVC, TL,CO, and SHQ scores. Unsupervised cluster analysis independently identified four data-driven radiological groups that partially overlapped with expert-defined subtypes, particularly in nodular and central patterns. However, the fibrotic subtype showed less distinct clustering, underscoring its radiological complexity. The agreement between expert-defined and cluster-derived classifications was limited (κ = 0.271), suggesting that the two approaches capture complementary but distinct dimensions of disease morphology.
Conclusions:
HRCT-based radiological subtypes of pulmonary sarcoidosis reflect clinically meaningful differences in symptom burden, ventilatory function, and radiological severity. While expert-driven and data-driven classifications show limited concordance, both provide valuable insights into disease heterogeneity. Radiological phenotyping using HRCT may serve as a practical adjunct to traditional staging systems, offering improved risk stratification and guiding personalized treatment decisions. Further prospective validation is needed to determine its utility in routine clinical practice and to explore its integration with emerging clinical and molecular phenotyping strategies.