Related Experiment Video
Updated: Oct 17, 2026
MRI-guided Focused Ultrasound Thalamotomy for Patients with Medically-refractory Essential Tremor
Published on: December 13, 2017
Unilateral MR-guided laser interstitial thermal therapy thalamotomy for refractory multiple sclerosis tremor:
Mickael Aubignat1, Mélissa Tir2, Martial Ouendo3
1Department of Neurology and Movement Disorders, Amiens Picardie University Hospital, Amiens, France; Research Unit UR-4559 (LNFP) Laboratoire de Neurosciences Fonctionnelles et Pathologies, University of Picardie Jules Verne, Amiens, France.

Background:
Tremor affects many people with multiple sclerosis (MS), is frequently disabling and responds poorly to medication. Deep brain stimulation, gamma-knife radiosurgery and MR-guided focused ultrasound are options, but each has constraints. MR-guided laser interstitial thermal therapy (MRgLITT) is a hardware-free stereotactic thalamotomy providing real-time thermometry, its role in MS tremor is unknown.
Objective:
To describe 12-month clinical, safety and imaging outcomes after unilateral MRgLITT thalamotomy for refractory MS tremor.
Methods:
Single-centre, consecutive case series of four patients with medically refractory MS tremor who underwent robot-assisted unilateral MRgLITT thalamotomy. The primary outcome was the treated-limb Fahn-Tolosa-Marin Tremor Rating Scale (FTM-TRS) at 12 months, scored from standardized videos by a blinded neurologist. Secondary outcomes were patient-reported tremor severity, tremor-related quality of life, adverse events, cognition, mood and MRI lesion characteristics. Analyses were descriptive.
Results:
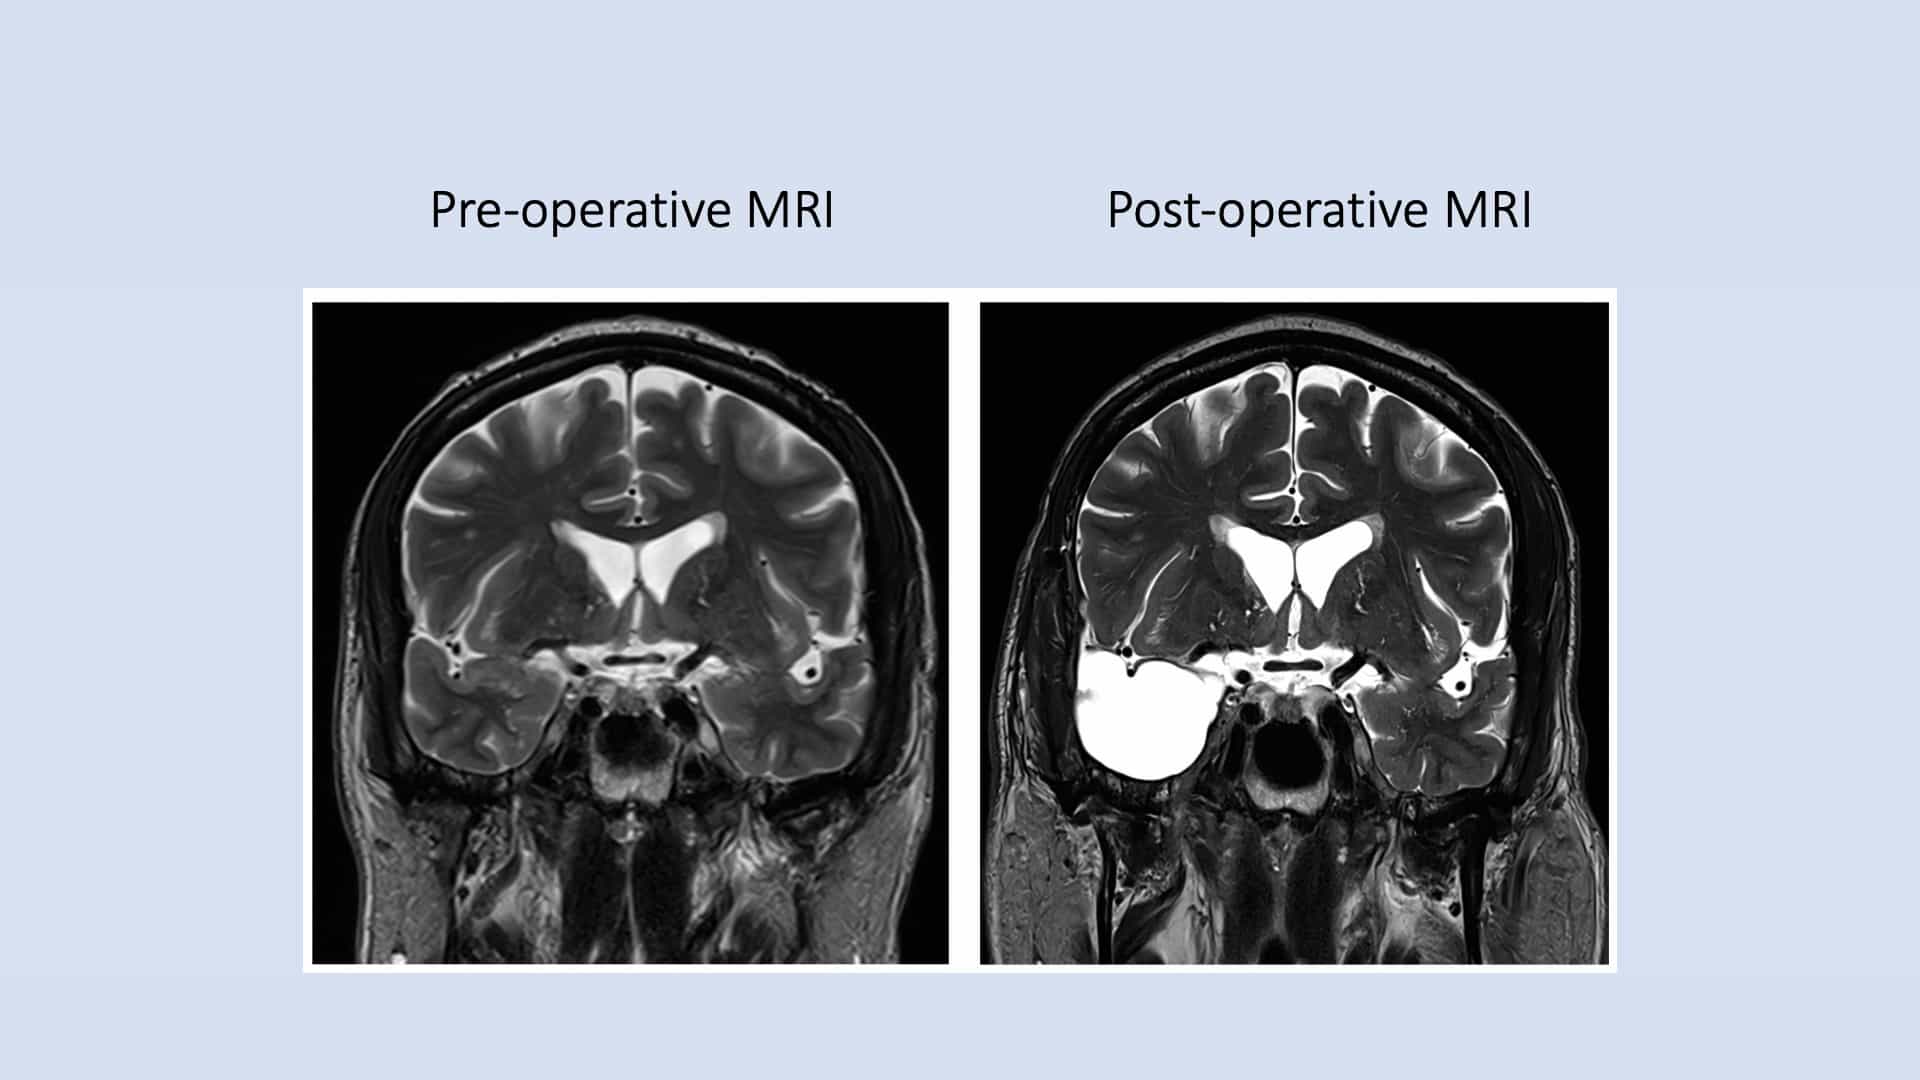
The cohort comprised three secondary-progressive and one relapsing-remitting patient (median EDSS 5.5; median tremor duration 15.5 years). The mean treated-limb FTM-TRS score fell from 15.8 to 5.5 at 12 months (mean per-patient reduction 65.7%, range 41.2-80.0%). Quality of life improved in three of four patients. Acute adverse events occurred in two patients (transient gait ataxia; transient hemiparesis with dysarthria), both resolving by 3 months, none persisting at 12 months. Cognitive decline in one patient and mood deterioration in two, the causes of these changes remain uncertain.
Conclusion:
Unilateral MRgLITT thalamotomy was feasible and produced meaningful, largely sustained tremor reduction within a narrow therapeutic window. Larger controlled studies are required to establish efficacy, durability, safety and function.