Related Experiment Video
Updated: Oct 17, 2026
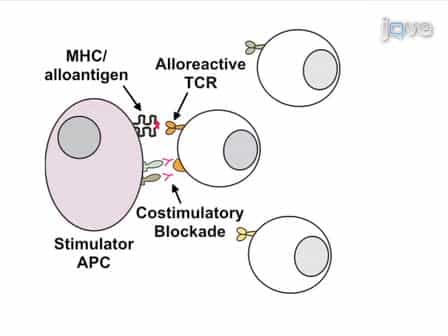
Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
Comprehensive, simplified, and objective comorbidity assessment before allogeneic hematopoietic cell transplantation:
Lorenzo Iovino1, Ningxin Ma2, Chris Davis2
1Fred Hutchinson Cancer Center, Seattle, WA; Department of Medicine, University of Washington, Seattle, WA.

Background:
Pretransplant comorbidity assessment informs risk stratification before allogeneic hematopoietic cell transplantation (allo-HCT), but the optimal balance among comprehensiveness, simplicity, and objectivity of the information captured under the available comorbidity indices (CI) remains uncertain.
Objective(S):
Here, we are comparing the performance of different CIs of assessing pre-HCT comorbidities and predicting outcomes.
Study Design:
We calculated the HCT-CI, the augmented HCT-CI (augHCT-CI), and the recently proposed simplified comorbidity index (SCI) based on a set of fewer comorbidities. We generated a fourth, objective HCT-CI (objHCT-CI), constructed from the measurable components of the augHCT-CI. We analyzed data from 3,473 consecutive single-center allo-HCT recipients transplanted from 2008-2022. We estimated the Harrell's C-index of the four CIs, their time-dependent ROC (Receiver Operating Characteristic) curve, and their ability of stratifying cumulative incidence of non-relapse mortality (NRM) and overall survival (OS).
Results:
All four indices significantly stratified NRM and OS (P<0.001). C-indices for NRM were 0.600 for HCT-CI, 0.632 for augHCT-CI, 0.628 for SCI, and 0.610 for objHCT-CI; corresponding C-indices for OS were 0.584, 0.612, 0.587, and 0.591. On the question on comprehensiveness versus simplicity, among 951 patients classified as SCI score 0, the augHCT-CI identified additional risk heterogeneity: 1-year NRM was 5.4%, 8.1%, and 10.9% for augHCT-CI scores 0, 1-2, and ≥3, respectively (Gray P=0.025), and OS differed significantly across these groups (P<0.0001).
Conclusion(S):
Performance of all indices was comparable. SCI offers simplicity, but may lose prognostic granularity among patients classified as lowest risk. Future tools should improve reproducibility and automation without sacrificing clinically meaningful comorbidity information.
