Related Experiment Video
Updated: Oct 17, 2026

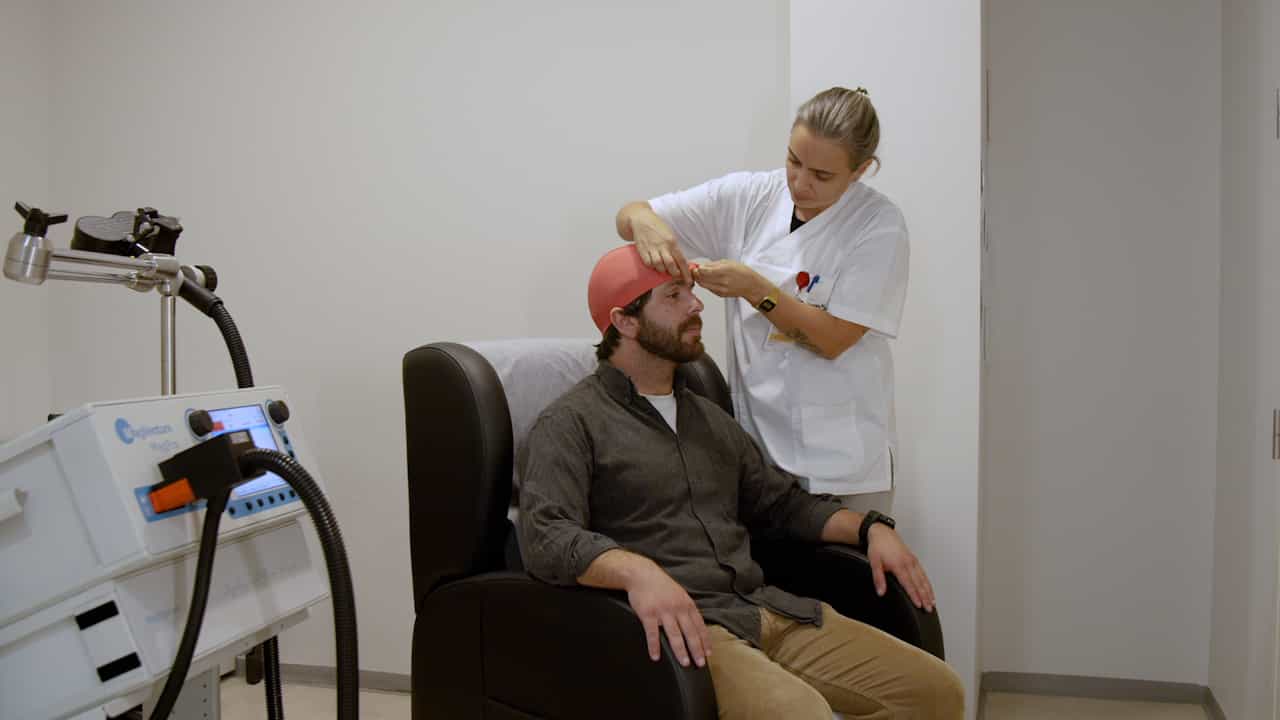
MRI-guided dmPFC-rTMS as a Treatment for Treatment-resistant Major Depressive Disorder
Published on: August 11, 2015
Transcranial alternating current stimulation for major depressive disorder: An updated systematic review and
Yehia Nabil1, Khaled Abdalla Moghib2, Zeyad Tarek1
1Faculty of Medicine, Zagazig University, Zagazig, Egypt.

Purpose:
Transcranial alternating current stimulation (tACS) may modulate neural oscillations implicated in major depressive disorder (MDD). This systematic review and meta-analysis assessed the efficacy, follow-up effects, tolerability, and safety of tACS in adults with MDD.
Methods:
PubMed/MEDLINE, CENTRAL, Scopus, Web of Science Core Collection, and Embase were searched from inception to March 29, 2026, for randomized controlled trials of active tACS in adults with MDD. Primary analyses compared active tACS with sham or inactive control, while active-protocol comparisons were analyzed separately. Random-effects models were used to calculate pooled mean differences (MDs) or odds ratios (ORs) with 95% confidence intervals (CIs). Heterogeneity was assessed using I2, and certainty of evidence was evaluated using the GRADE approach.
Results:
Eleven reports from nine randomized trials were included. Active tACS did not significantly reduce clinician-rated depressive symptom severity compared with control (8 studies, 471 participants; MD -1.80, 95% CI -4.80 to 1.20; I2 = 89.8%), indicating substantial heterogeneity. However, tACS was associated with higher odds of treatment response (8 studies, 680 participants; OR 2.41, 95% CI 1.28-4.56; I2 = 62.1%) and remission (4 studies, 270 participants; OR 4.69, 95% CI 2.37-9.28; I2 = 30.1%). A significant effect was also observed for response at the latest reported assessment (7 studies, 608 participants; OR 2.70, 95% CI 1.62-4.49; I2 = 20.3%). Regarding safety, active tACS increased the likelihood of at least one adverse event (3 studies, 475 participants; OR 1.95, 95% CI 1.12-3.41), while estimates for headache and cutaneous symptoms were imprecise and not significantly different between groups. Overall certainty of evidence ranged from very low to moderate.
Conclusion:
tACS may improve response and remission rates in MDD, but its effect on mean symptom severity remains uncertain. High heterogeneity and limited data for protocol-specific subgroup analyses reduce interpretability, as pooled estimates reflect heterogeneous stimulation parameters rather than specific regimens. Given the small evidence base and limited certainty, routine clinical use cannot be recommended. Well-powered, standardized, and independently conducted trials with longer follow-up are required.