Related Experiment Video
Updated: Oct 17, 2026

Assessment of Intestinal Transcytosis of Neonatal Escherichia coli Bacteremia Isolates
Published on: February 17, 2023
Laboratory correlates of observation and hospitalization decisions in children with acute gastroenteritis: an
1Department of Pediatrics, Özel Gürlife Hospital, Eskişehir, Turkey. dr_mcengiz@hotmail.com.

Objective:
To examine, in children with acute gastroenteritis (AGE), the association between laboratory (and available clinical) findings and the real-world clinician decision to place a child under observation or to admit. The study is explicitly exploratory and association-based, not a prediction model.
Methods:
Single-centre retrospective analysis of 226 children aged 0-18 years (April 2024-March 2026). Disposition was classified hierarchically (outpatient discharge / observation only / hospitalization). Laboratory tests were obtained at clinician discretion at presentation, at intravenous cannulation and before fluids. Group comparisons used Mann-Whitney U with Benjamini-Hochberg FDR across 11 parameters; three-group comparisons used Kruskal-Wallis with Dunn post-hoc. NLR and PLR were assessed as exploratory composites. Logistic models reported adjusted ORs with VIF; discrimination was summarised by ROC AUC with bootstrap optimism correction. Analyses restricted to the tested subgroup (Python 3; SciPy/statsmodels).
Results:
Laboratory testing was obtained in 43% of outpatients versus 98% of observation/hospitalization patients, indicating highly differential, clinician-directed (informative) missingness. Compared with outpatients, children escalated to observation or hospitalization had lower lymphocyte counts and higher neutrophil counts and urea (all FDR p < 0.05). Across the three groups, lower lymphocyte count separated outpatients from escalated patients (H = 20.1, p < 0.001) but did not distinguish observation from admission. In the composite multivariable model, lower lymphocyte count was the strongest correlate (adjOR 0.575, 95% CI 0.419-0.789; p = 0.001). Adding lymphocyte count to available clinical variables (fever, vomiting, measured temperature) was associated with improved model fit within the tested subgroup (likelihood-ratio p < 0.001; apparent AUC 0.75→0.81). As a secondary exploratory observation, the neutrophil-to-lymphocyte ratio showed the numerically highest single-marker discrimination (AUC 0.78, 95% CI 0.68-0.86), though its bootstrap confidence interval overlapped substantially with those of lymphocyte and neutrophil counts. The multivariable escalation model had an optimism-corrected c-statistic of 0.77 (apparent 0.82). No parameter survived FDR correction for the hospitalization-specific outcome. Rotavirus positivity was associated with admission (OR 2.74; p = 0.015).
Conclusion:
Among children who underwent laboratory testing for AGE, lower lymphocyte count was the marker most consistently associated with the clinician's decision to escalate care, with higher NLR a secondary exploratory signal. Because these same laboratory values informed the disposition decision (incorporation bias) and testing was selective, findings describe associations with real-world management within the tested subgroup and are hypothesis-generating rather than predictive or generalisable to all children with AGE.
Related Concept Videos
 01:11
Observational Studies
There are three types of observational studies – Prospective, retrospective, and cross-sectional.
Prospective Study
Prospective studies, also known as longitudinal or cohort studies, are carried out by collecting future data from groups sharing similar characteristics. One example of...
 01:18
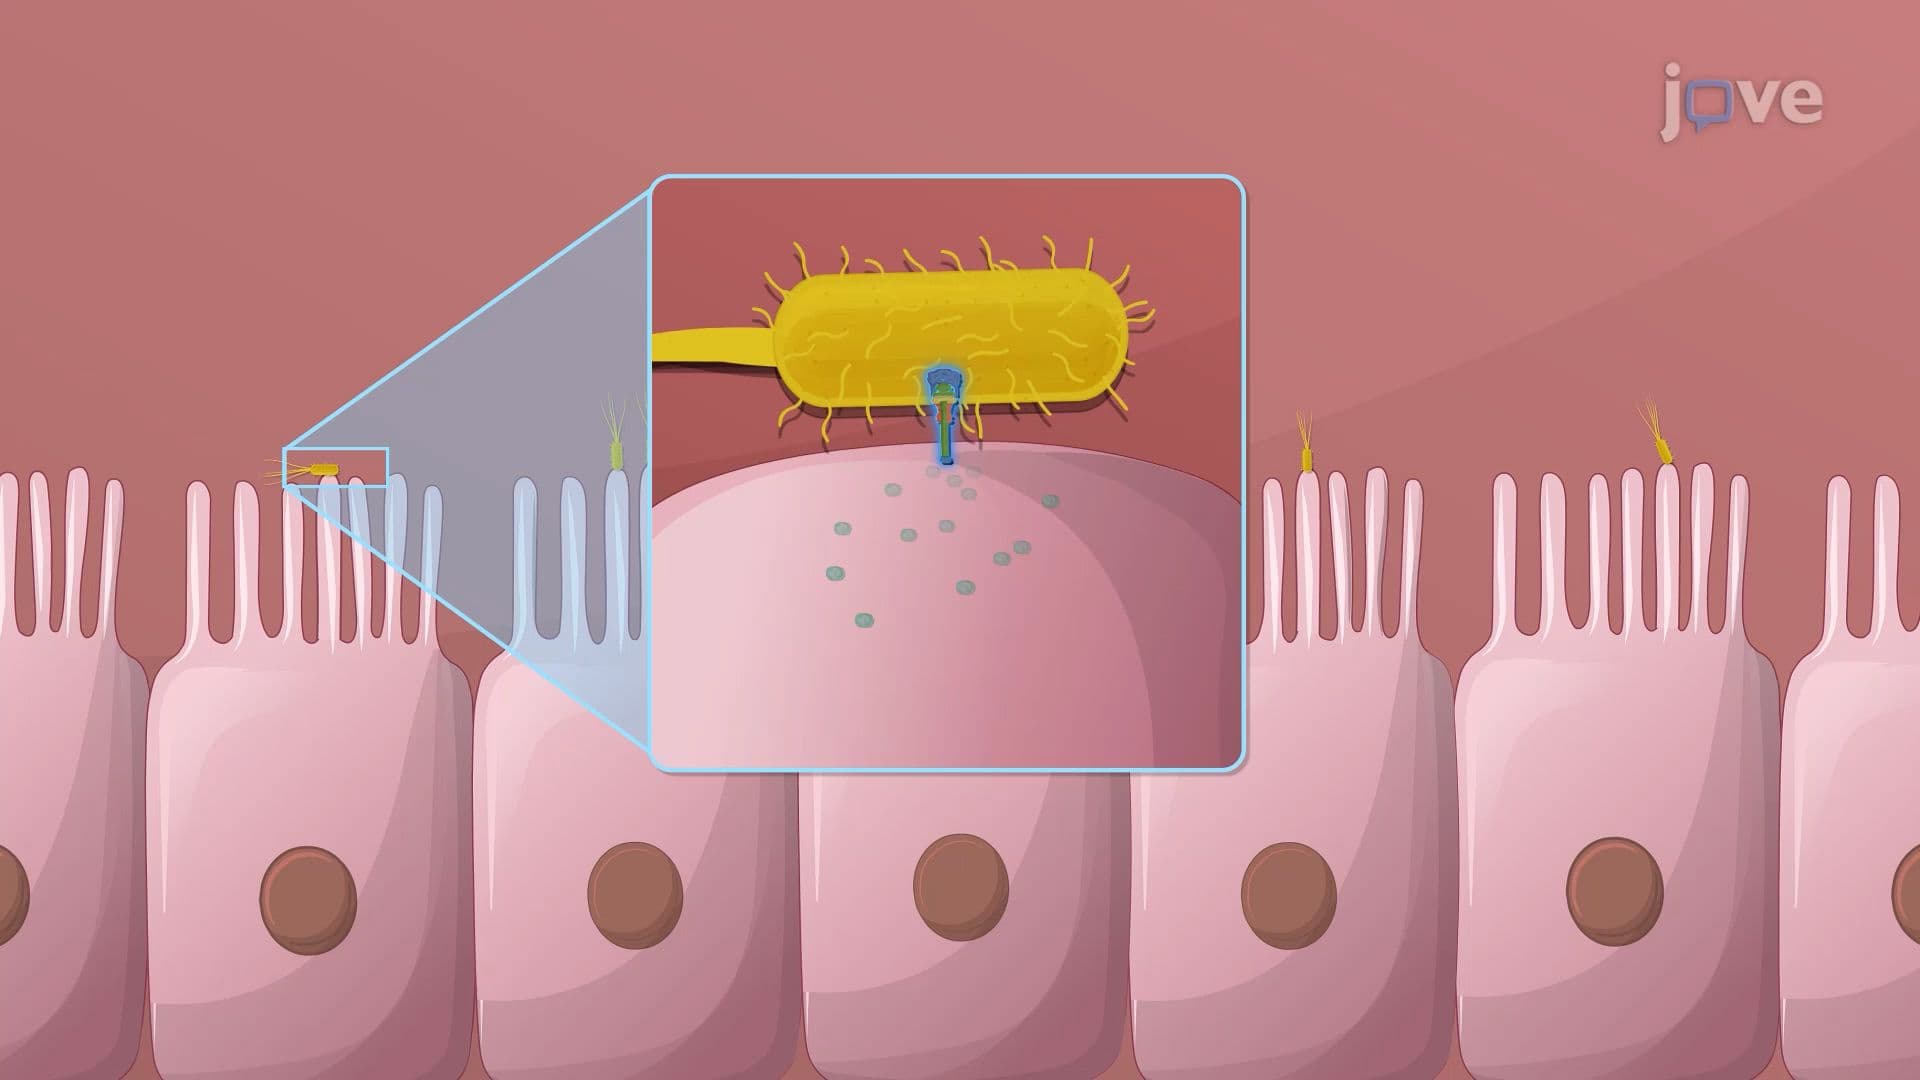
Bacterial Gastroenteritis
 01:29
Assessment of the Gastrointestinal System II: Health Perception Pattern
Health Perception Patterns
Health perception patterns offer valuable insights into a patient's lifestyle habits and how they may impact their GI health. These patterns include:
 01:23
Investigation of Disease Outbreaks
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.