Related Experiment Video
Updated: Oct 17, 2026
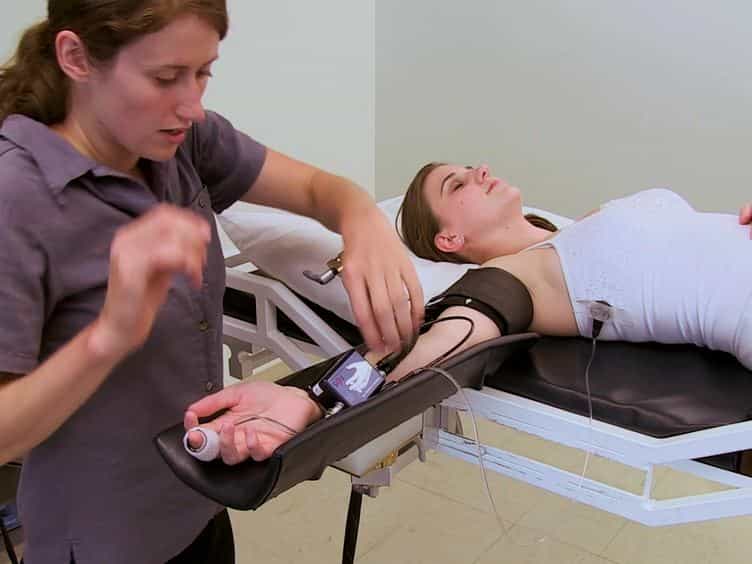
Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
From Mechanism to Management in Vasovagal Syncope: An Integrative Review
Sérgio Laranjo1,2,3,4, Mário Martins Oliveira5,6,7, Isabel Rocha4,6,7
1Departamento de Fisiologia, NOVA Medical School (NMS), Faculdade de Ciências Médicas (FCM), Universidade NOVA de Lisboa, 1169-056 Lisbon, Portugal.

Abstract:
Background/Objectives: Vasovagal syncope is the most common subtype of reflex syncope and a frequent cause of transient loss of consciousness. Although its prognosis is generally benign, recurrent episodes can cause injury, restrict daily activities, and impair quality of life; patients who remain symptomatic despite first-line measures present a therapeutic challenge. This review integrates current evidence on mechanisms, prediction, and treatment, examining whether arterial-pressure defence and baroreflex behaviour provide a useful physiological framework. Methods: We conducted a narrative integrative review of PubMed and ClinicalTrials.gov from inception to June 2026, prioritising randomised trials, meta-analyses, major observational studies, guidelines and multi-society statements. No formal risk-of-bias assessment or de novo quantitative synthesis was undertaken. Results: Current evidence supports a dynamic failure of cardiovascular compensation during orthostatic stress, with variable contributions from impaired vasoconstrictor support and cardioinhibition. Laboratory haemodynamic and autonomic markers may anticipate tilt-test outcome, but this should not be equated with prediction of spontaneous clinical recurrence. Tilt training may modify vasoconstrictor reserve and baroreflex indices, although clinical efficacy varies with protocol and adherence. Therapeutic options extend from counter-pressure manoeuvres and selected pharmacological agents to pacing in highly selected patients with documented clinically relevant asystole; cardioneuroablation remains an emerging intervention. Conclusions: The haemodynamic phenotype may inform treatment selection but should not be used as a stand-alone indication for invasive therapy. We propose an evidence-informed, mechanism-based model of care, incorporating patient-reported outcomes, shared decision-making and cautious evaluation of emerging predictive and interventional approaches.
Related Concept Videos
 01:18
Neural Regulation of Blood Pressure
Baroreceptor Reflex
Baroreceptors, located in the carotid sinuses and aortic arch, detect changes in blood pressure. When blood pressure rises, these stretch-sensitive receptors...
 01:30
Heart Failure V: Medical Management
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:18
Disorders of the Autonomic Nervous System
Raynaud's disease, also known as Raynaud's phenomenon, is a...
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:26
Acute Coronary Syndrome V: Nursing Management