Related Experiment Video
Updated: Oct 17, 2026
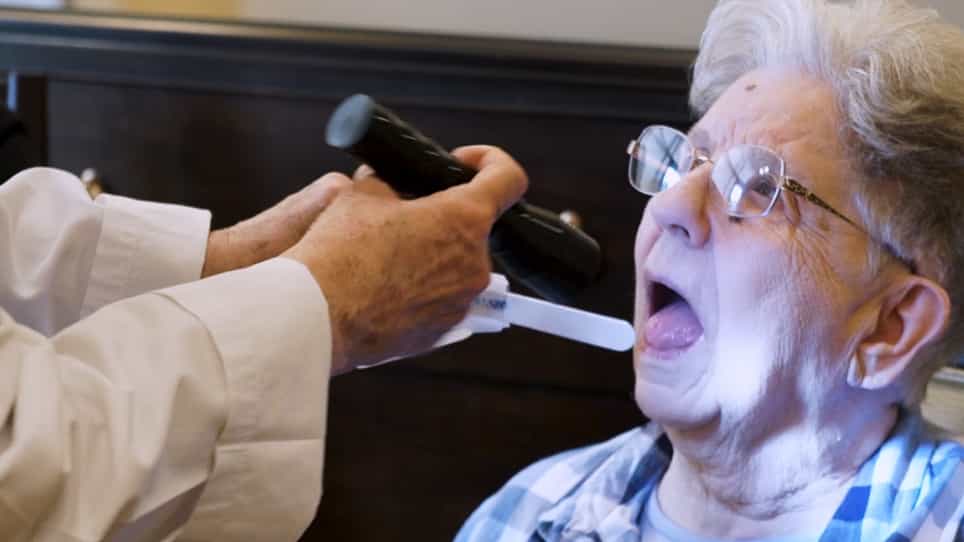
Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Comparative Analysis of Dental Emergency Visits and Dental Readiness Classifications on a Major U.S. Army
Eric Hu1,2, Anna Yoo1,2, James Giesen3
12-Year Advanced Education in General Dentistry Residency Program, Fort Hood, TX 76544, United States.

Introduction:
Optimal oral health is essential to service members' well-being, deployability, and operational performance. Dental emergencies (DEs) result in lost duty time and degrade combat effectiveness, particularly during large-scale combat operations (LSCO), when evacuation and definitive dental care may be limited. Dental Readiness Classifications (DRC) are used to determine service member deployability; however, their effectiveness in predicting and preventing DEs has not been well-characterized using contemporary data. This study evaluated the nature of DEs and its relationship with DRCs at a major U.S. military installation.
Materials And Methods:
This retrospective study reviewed de-identified Military Health System Genesis-Dentrix electronic dental records for active duty service members who presented for DE visits from January 1, 2025, to March 31, 2025. DE visits were identified using Current Dental Terminology codes W0199 (Dental emergency visit), and/or D9110 (Palliative emergency treatment for relief of dental pain). Each DE was categorized into major and sub-categories based on diagnosis at the DE visit. Data collected included association with prior diagnosis, planned treatment, or recent treatment; interval from the most recent comprehensive or periodic dental examination or associated dental visit; DRC status before and after the DE encounter; need for off-post referral through the Active Duty Dental Program (ADDP); and time required to resolve post-encounter DRC 3 conditions or return patients to DRC 1 or 2 status.
Results:
A total of 791 DE visits met inclusion criteria. The most common DE categories were oral surgery (31.9%), restorative non-caries (14.6%), and endodontics (12.5%). Third molar-related conditions comprised most oral surgery DEs, whereas defective restorations, fractured teeth, and molar pulpal diagnoses were leading contributors in other categories. Before the DE encounter, 90.8% of patients were classified as fully medically ready to deploy (DRC 1: 28.9%; DRC 2: 61.9%). Overall, 35.5% of DEs (DRC 1: 23.1%; DRC 2: 35.9%; DRC 3: 72.2%) were associated with a prior diagnosis, planned treatment, or recent treatment, and occurred a median 18.5 days after the associated appointment. Unassociated DEs occurred a median of 152 days after the patient's most recent annual dental examination. After the DE visit, the proportion of patients classified as DRC 3 increased from 9.1% to 22.8%. Post-encounter DRC 3 conditions required a median of 16.5 days to resolve or return to DRC 1 or 2 status. Off-post referral was required for 11.7% of DEs, most commonly for third molar extractions under intravenous sedation, molar endodontic treatment, and crowns.
Conclusions:
A high proportion of DEs occurred among service members classified as DRC 1 or 2 before the emergency encounter, indicating that current DRC definitions are unable to fully identify conditions likely to progress to urgent treatment needs. Although conditions classified as DRC 3 are prioritized and treated promptly, many DRC 2 treatments are delayed and are likely to progress into a DE within 6 months of an annual exam. These findings support refinement of DRC definitions, improved provider calibration, expanded clinical capacity in oral surgery, endodontics, and restorative dentistry, and increased emphasis on prevention and timely treatment to improve operational readiness.