Related Experiment Video
Updated: Oct 17, 2026
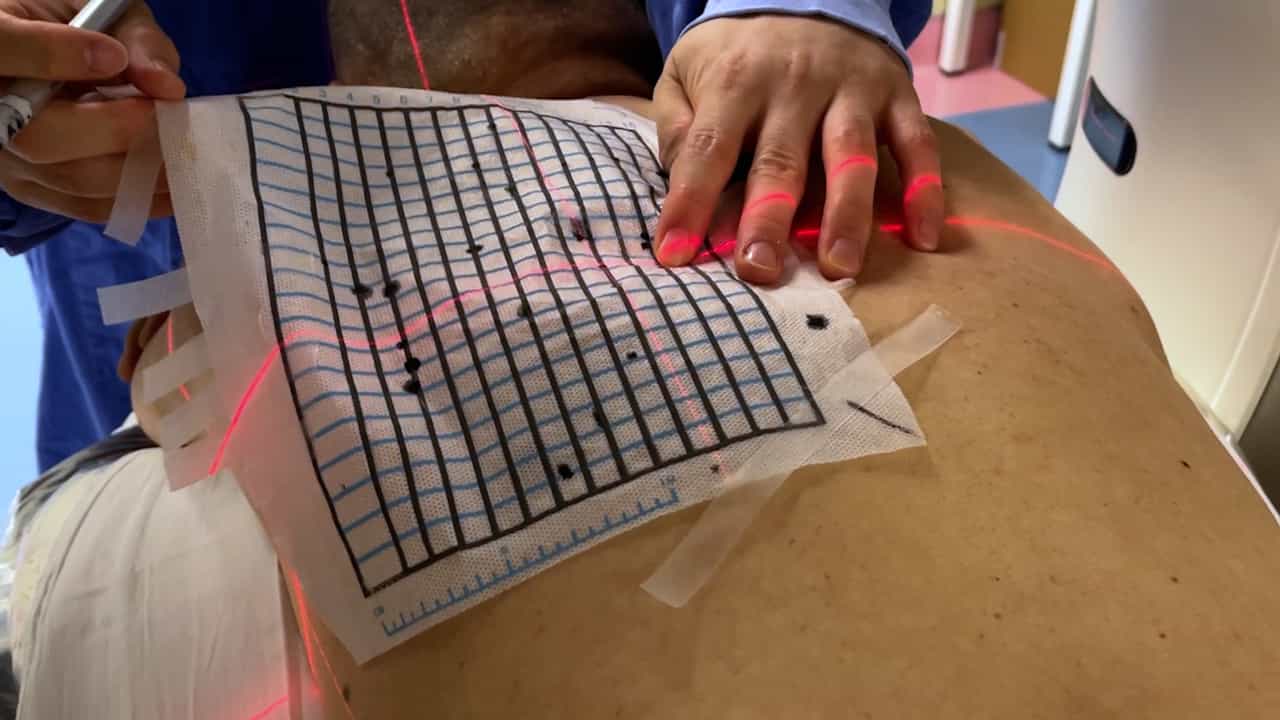
Electromagnetic Navigation Transthoracic Nodule Localization for Minimally Invasive Thoracic Surgery
Published on: May 4, 2022
Nodule Dye-Localization Using Interventional Fluoroscopy for Image-Guided Sublobar Lung Resection
Yueh-Lin Wu1, Kam-Hong Kam1,2, Chi-Yen Liang3
1Division of Thoracic Surgery, Department of Surgery, Ditmanson Medical Foundation Chia-Yi Christian Hospital, Chia-Yi, Taiwan.

Background:
Precise localization is critical for sublobar resection of small pulmonary nodules. We evaluated the safety, technical efficiency, and clinical outcomes of preoperative percutaneous dye-localization using a cone-beam computed tomography (CBCT)-enabled flat-panel detector interventional fluoroscopy system in a hybrid operating room (HOR).
Methods:
We retrospectively reviewed 74 consecutive patients (137 lesions) who underwent image-guided localization followed by video-assisted thoracoscopic surgery (VATS) sublobar resection (wedge resection or segmentectomy) between 2022 and 2023 at Chia-Yi Christian Hospital. Procedural workflow, localization success, surgical margins, and perioperative outcomes were systematically analyzed.
Results:
Technical localization success was achieved in 100% of lesions (mean nodule diameter: 8.59 ± 4.85 mm). The procedure required a mean of 1.31 ± 0.67 puncture attempts per lesion at a mean depth of 5.22 ± 1.86 cm. Procedure-related pneumothorax occurred in 29.7% (22/74) of patients, with 14.9% (11/74) requiring pigtail catheter drainage; pneumothorax occurrence was significantly associated with multiple puncture attempts (p < 0.001) and lower-lobe lesions (p = 0.001). Lower-lobe location was significantly associated with requiring more puncture attempts (p = 0.028). For malignant lesions, the mean pathological resection margin was 17.16 ± 8.73 mm, with 92.31% achieving a margin-to-tumor ratio (MTR) ≥ 1. The mean postoperative hospital stay was 3.04 ± 1.16 days.
Conclusions:
Single-stage image-guided dye-localization and VATS sublobar lung resection in an HOR using a biplane CBCT-enabled platform is safe, feasible, and effective. This streamlined workflow ensures high technical success and adequate surgical margins with manageable complications. Further studies are warranted to evaluate long-term oncological outcomes.