Related Experiment Video
Updated: Oct 17, 2026
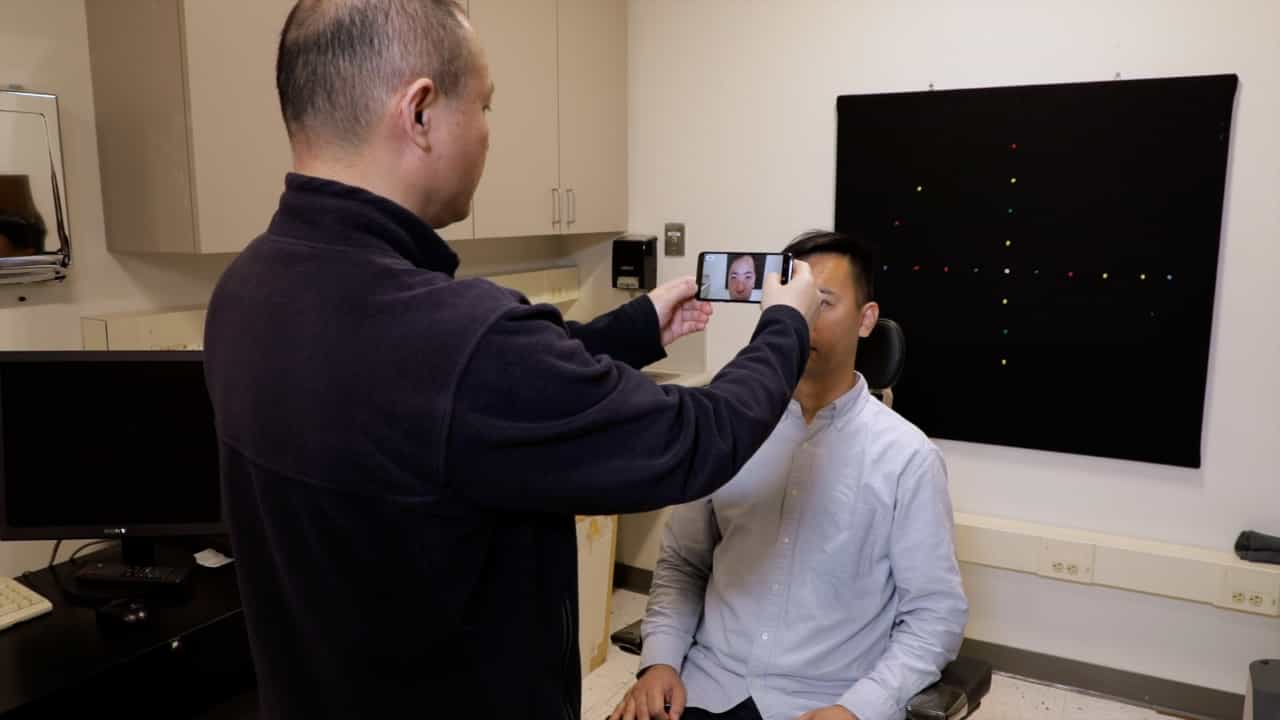
Subjective Refraction Test Using a Smartphone for Vision Screening
Published on: October 18, 2024
Performance of Automated Vision Screening and Refraction in Young Children in Belize
Hannah Istre-Wilz1, Eliza Barnwell1, Emily J Scircle2
1Department of Ophthalmology.

Purpose:
To determine how automated instrument-based screening with the Spot Vision Screener (SVS) (Welch Allyn, Inc/Baxter) compares with standard visual acuity testing in Belizean schoolchildren, and to compare refractive results of the SVS and QuickSee hand-held autorefractor (PlenOptika).
Methods:
During a school-based vision screening program in Orange Walk, Belize, SVS performance was evaluated against visual acuity testing as the reference standard. Children failing visual acuity per American Association for Pediatric Ophthalmology and Strabismus (AAPOS)/National Center for Children's Vision and Eye Health guidelines (20/30 for age 5 years and older, 20/40 for age 4 years, and 20/50 for age 3 years) were considered referrals. SVS performance was assessed under three referral criteria sets: manufacturer thresholds, AAPOS 2021 guidelines, and stricter exploratory thresholds. Agreement between the SVS and QuickSee hand-held autorefractor was analyzed using intraclass correlation coefficients and mean bias.
Results:
Of 1,009 children screened, 692 had both visual acuity and SVS measurements; 11.6% failed visual acuity screening. SVS sensitivity and specificity varied by criteria: manufacturer (45.0%, 95.3%), AAPOS (31.25%, 97.7%), and stricter thresholds (61.24%, 82.0%). Positive predictive value ranged from 30.82% to 64.10%. Stricter criteria increased sensitivity but reduced specificity. Device agreement analysis (589 children) showed moderate correlation for cylinder (intraclass correlation coefficient = 0.724) and sphere (intraclass correlation coefficient = 0.557), with the SVS tending to report higher refractive magnitudes.
Conclusions:
Automated screening using the SVS is a good option in school settings and can complement visual acuity testing, particularly where resources are limited. Referral thresholds should be tailored to program priorities to balance sensitivity and specificity. Agreement between the SVS and QuickSee supports their utility for efficient refractive assessment in community-based programs.

