Radiofrequency Ablation for Selective Reduction in Complicated Monochorionic Twin Pregnancies: Pregnancy-Level and

Introduction:
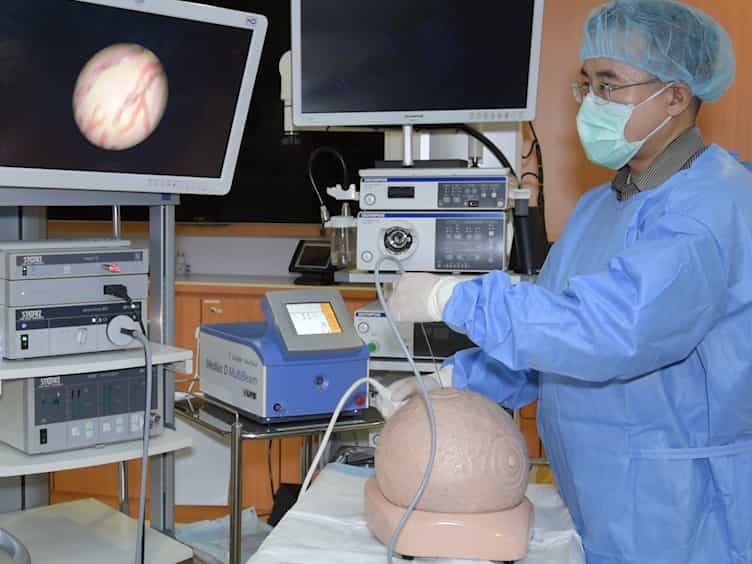
Monochorionic twin pregnancies may be complicated by shared placental vascular anastomoses and hemodynamic interdependence between fetuses. Radiofrequency ablation (RFA) is a vaso-occlusive option for selective reduction when continuation of the affected fetus is expected to endanger the co-twin.
Methods:
This retrospective cohort study included 39 monochorionic twin pregnancies treated with RFA at two tertiary centers between January 2017 and December 2025. Indications were grouped as TTTS/TAPS-related conditions, selective fetal growth restriction (sFGR)-related conditions, twin reversed arterial perfusion (TRAP) sequence, and discordant major fetal anomaly. The primary outcome was live birth of at least one fetus. Secondary outcomes included miscarriage, stillbirth/intrauterine fetal demise, termination after RFA, preterm prelabor rupture of membranes (PPROM), gestational age at delivery, birth weight, neonatal intensive care unit (NICU) admission, neonatal death, and survival to neonatal hospital discharge.
Results:
The main indications were sFGR-related conditions (14/39, 35.9%) and TTTS/TAPS-related conditions (12/39, 30.8%). Live birth of at least one fetus occurred in 38/39 pregnancies (97.4%), and pregnancy-level survival to neonatal hospital discharge occurred in 37/39 pregnancies (94.9%). PPROM after RFA occurred in 2/39 pregnancies (5.1%). Among pregnancies with live birth, median gestational age at delivery was 38.00 weeks (IQR, 34.00-39.00). Exploratory comparisons across indication groups, including direct TTTS/TAPS-related versus TRAP comparisons for gestational age at delivery and procedure-to-delivery interval, were not statistically significant.
Conclusion:
RFA was associated with high rates of live birth and survival to neonatal hospital discharge in this cohort of complicated monochorionic twin pregnancies. Exploratory subgroup comparisons were not statistically significant; therefore, observed indication-specific patterns should be interpreted cautiously and require confirmation in larger multicenter cohorts.