Related Experiment Video
Updated: Oct 18, 2026
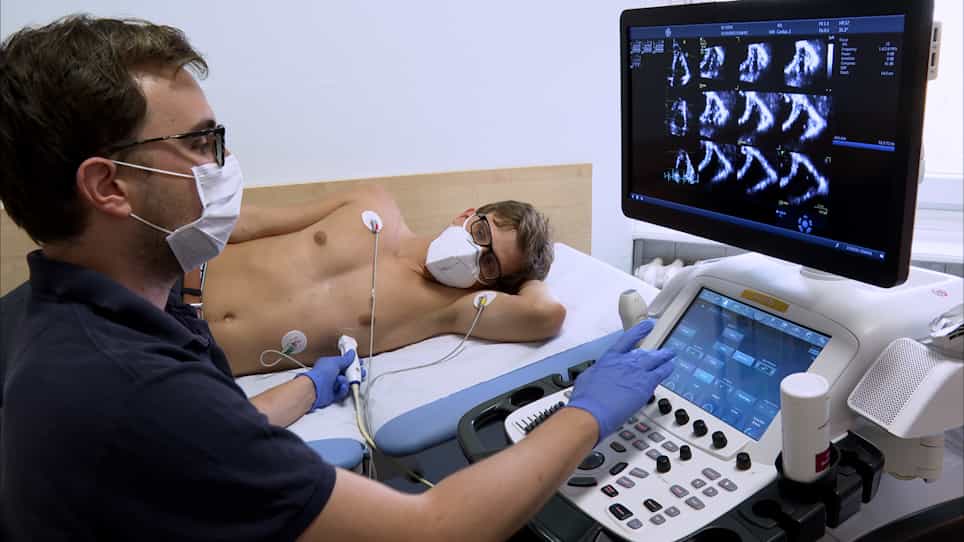
Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Septal dysfunction and Abnormal Systolic Stretch Are Associated with Right Ventricular Dysfunction in Repaired
Emmanuelle Fournier1, Raphael Joye2, Yuval Bitterman2
1Labatt Family heart center, Department of Pediatrics, The Hospital for Sick Children, University of Toronto, Toronto, Canada; Department of Congenital Heart Diseases, Reference center for Complex Congenital Cardiac Disease M3C, Marie Lannelongue Hospital, Le Plessis-Robinson, France.

Aims:
Right ventricular (RV) dysfunction is a major determinant of outcomes after Tetralogy of Fallot repair (rToF). Although right bundle branch block is present in most patients and electro-mechanical dyssynchrony (EMD) has been associated with RV dysfunction, only a subset of patients ultimately develops RV dysfunction. We hypothesized that septal dysfunction is a key feature associated with the development of EMD-induced RV dysfunction in rToF.
Methods:
We retrospectively studied 126 pediatric rToF patients (median age 14.7 years) with contemporaneous ECG, echocardiography, and cardiac magnetic resonance (CMR) between 2019-2025. Septal mechanics were quantified by strain-derived systolic rebound stretch (SRS) and further combined with RV free-wall mechanics into a systolic stretch index (SSI). RV mechanical dyssynchrony was visually classified, with septal contraction abrogation and systolic stretch as key features. Multivariable models evaluated associations between systolic stretch parameters and RV dysfunction (CMR-derived RV ejection fraction (EF) ≤ 46%), adjusting for relevant covariates.
Results:
RV dysfunction was present in 24.6% of patients. Patients with >moderate RV outflow tract obstruction (peak gradient >40 mmHg) were excluded, median pulmonary regurgitant fraction was 35% (IQR, 26-44%). Median SSI was higher in patients with RV dysfunction than in those without (8.9% (IQR 3.2-11.3) vs 2.9% (IQR 1.5-5.5), p<0.001). Premature termination of septal deformation with subsequent stretching, quantified by SRS, was associated with RV dysfunction (p<0.001). Worse septal stretch patterns were associated with RV dysfunction, larger RV end-systolic indexed volume, and longer QRSd (p<0.001). Higher SSI was independently associated with lower RVEF (p<0.001) after adjustment for age, QRSd, RV dilation, and surgical substrate (p<0.001), whereas QRSd lost significance on RVEF after adjusting for SSI. RVEF was lower at SSI values >4%. SSI demonstrated excellent intraobserver and interobserver reproducibility (ICC 0.996 and 0.997, respectively).
Conclusions:
In pediatric rToF, RV dysfunction was associated with abnormal septal contraction and systolic stretch. RV-SSI, integrating inefficient RV mechanics via septal and RV free-wall systolic stretch, was independently associated with RV dysfunction beyond QRSd, RV volumes and pulmonary regurgitation severity. These findings may help characterize RV electromechanical phenotypes and provide a rationale for future studies evaluating RV resynchronization therapy.
Related Concept Videos
 01:22
Mitral Stenosis I: Introduction
 01:20
Mitral Regurgitation I: Introduction
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:25
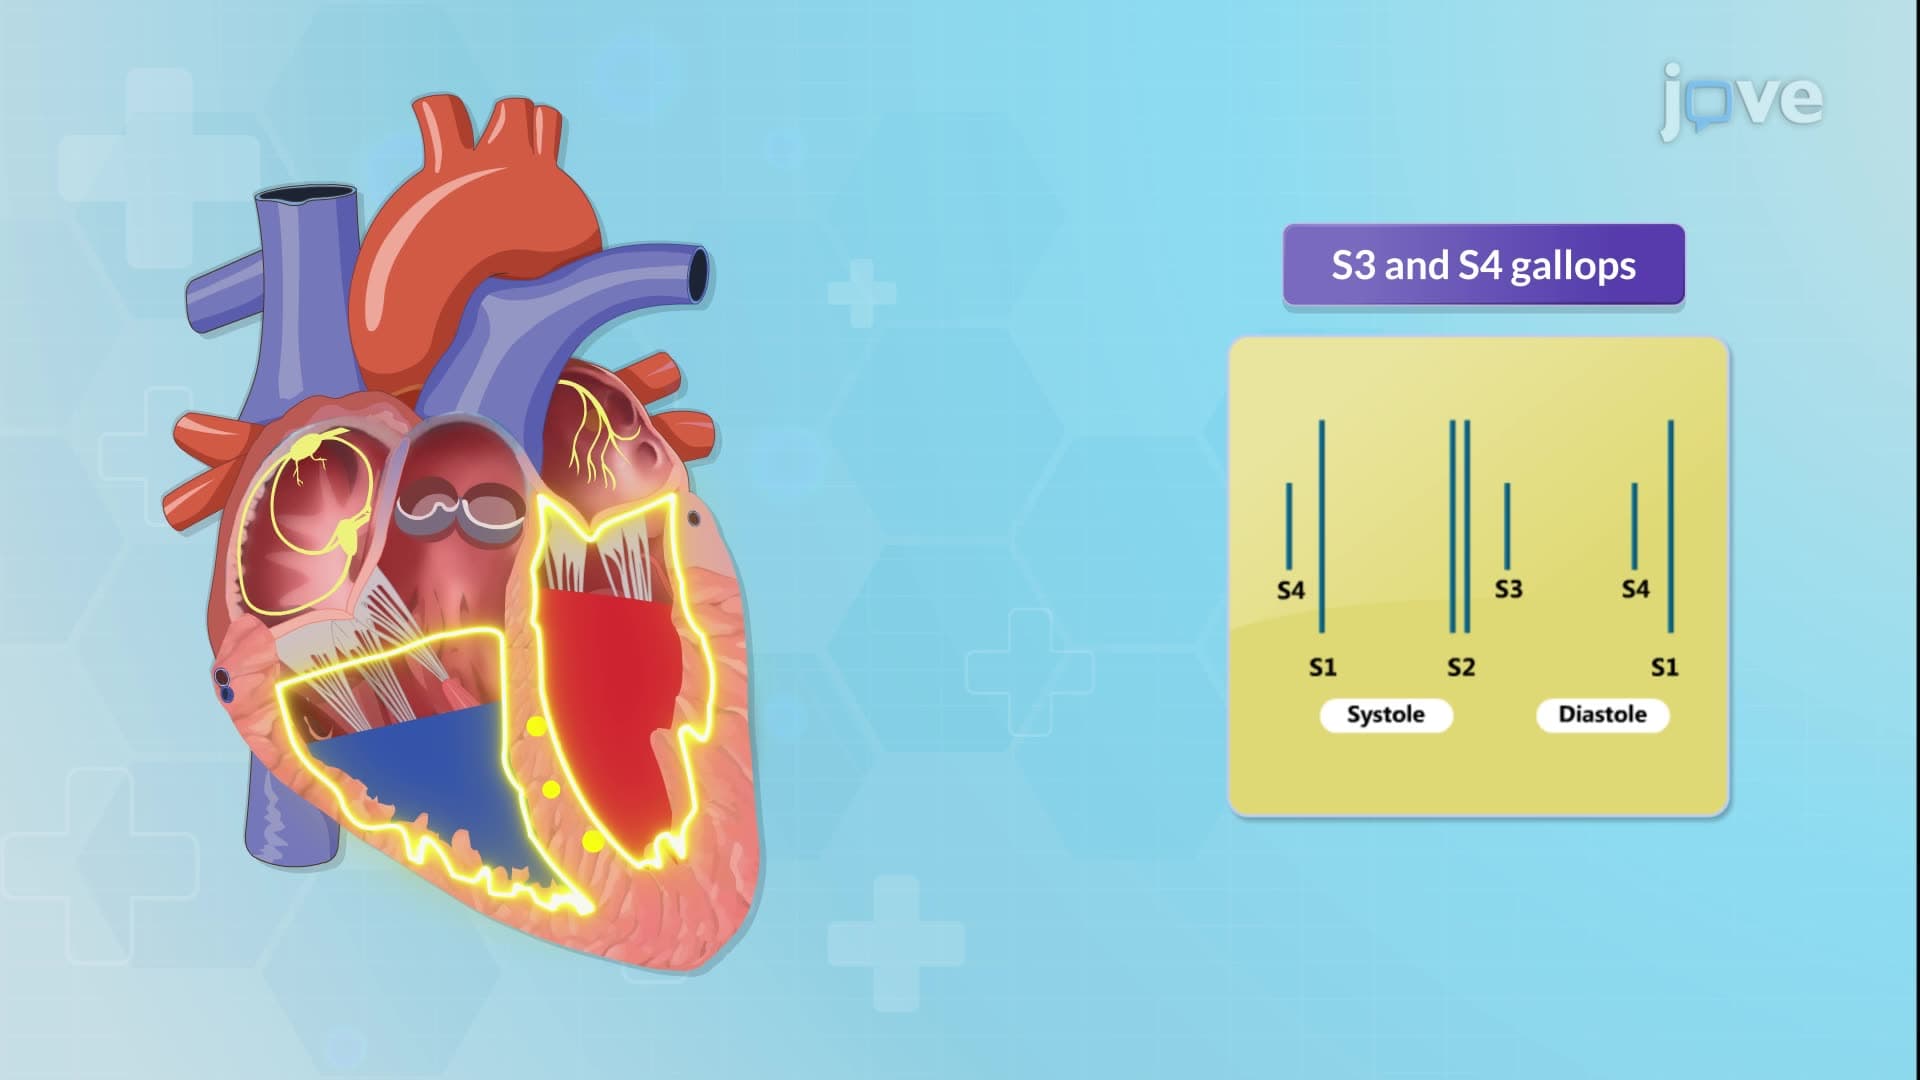
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests