Related Experiment Video
Updated: Oct 18, 2026

A Bedside, Single Burr Hole Approach to Multimodality Monitoring in Severe Brain Injury
Published on: March 26, 2019
Neuroendoscopic-Assisted vs. Conventional Burr-Hole Drainage for Septated Chronic Subdural Hematoma: A Comparative
Wentao Lai1,2, Guanlin Huang1,2, Chuanyun Liu3
1Department of Neurosurgery, Ganzhou Hospital-Nanfang Hospital, Southern Medical University, Ganzhou, China.

Objective:
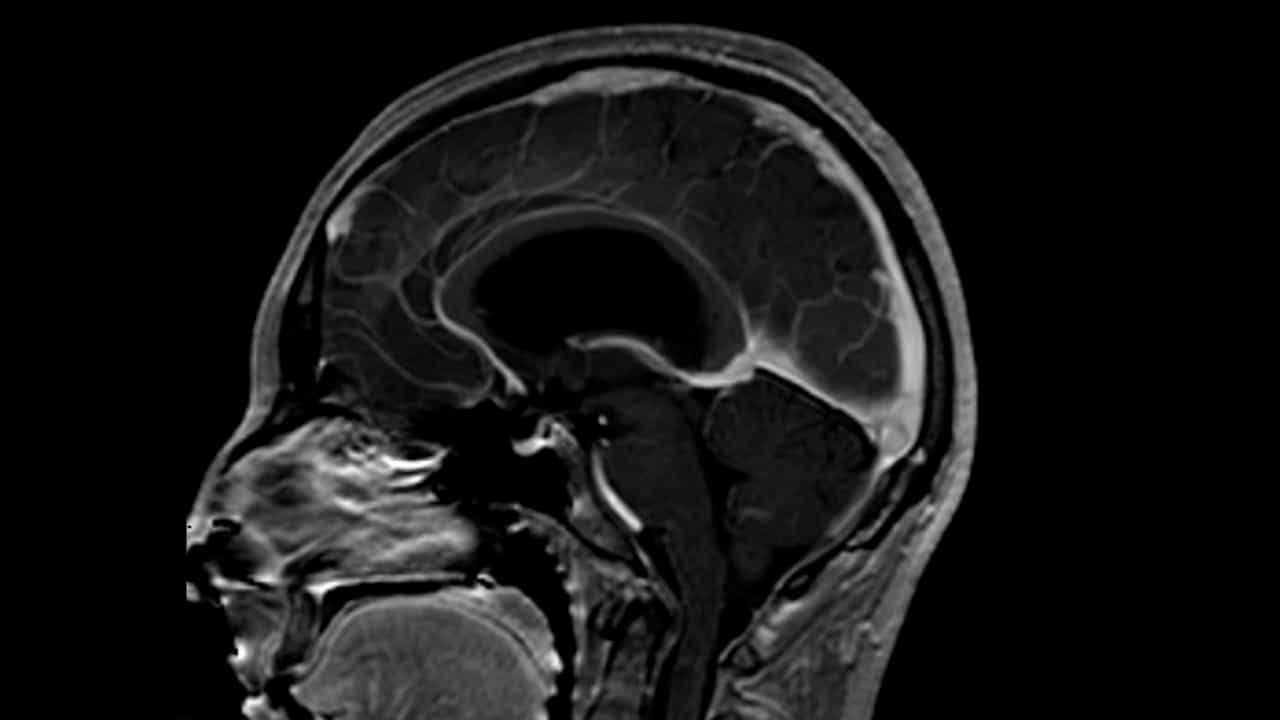
Chronic subdural hematoma (CSDH) is prevalent in the elderly. Its septated variant poses a significant surgical challenge, as conventional burr-hole drainage often yields suboptimal results due to incomplete evacuation. Neuroendoscopy has emerged as a potential solution, but robust comparative evidence is lacking.
Methods:
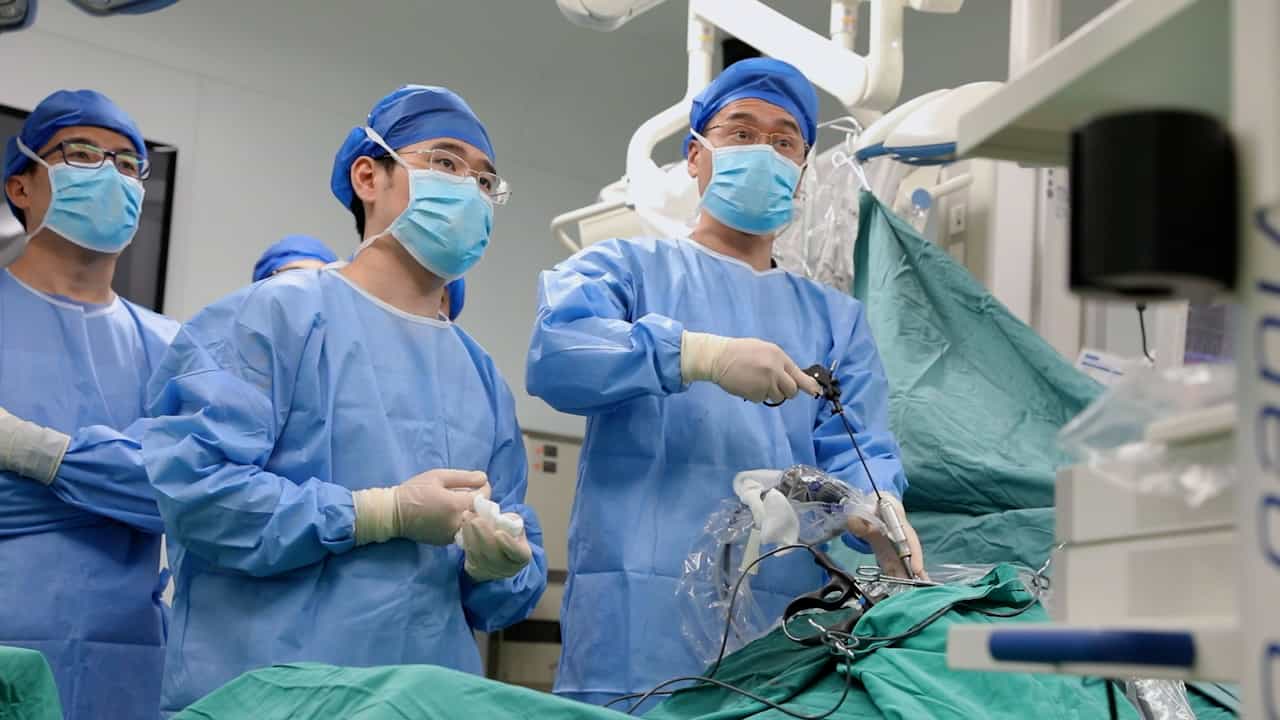
In this single-center retrospective cohort study, we enrolled 100 patients with radiologically confirmed septated CSDH. Fifty-two underwent neuroendoscopic-assisted evacuation (Endoscopic Group), and 48 underwent conventional burr-hole drainage (Burr-Hole Group). We compared intraoperative metrics (operative time, blood loss, irrigation volume, hematoma evacuation rate), drainage duration, recurrence, and neurological/functional outcomes (mRS, NIHSS, ADL, GOS) at 6 months.
Results:
The Endoscopic Group demonstrated a significantly higher hematoma evacuation rate (89.96% vs. 81.64%, p < 0.001) with substantially less irrigation fluid (587 vs. 1538 mL, p < 0.001), despite a longer operative time (68.34 vs. 47.52 min, p < 0.001). The endoscopic approach also led to shorter drainage retention (median 1.0 vs. 2.0 days, p < 0.001) and a significantly reduced recurrence rate (0% vs. 12.5%, p = 0.010). At 6 months, the Endoscopic Group showed superior outcomes, evidenced by more favorable mRS distributions (p = 0.004), lower NIHSS scores (7.42 vs. 8.26, p = 0.006), higher ADL scores (92.78 vs. 84.45, p < 0.001), and better GOS ratings (p = 0.014). Overall complication rates were comparable (5.8% vs. 14.6%, p = 0.134).
Conclusion:
Neuroendoscopic-assisted burr-hole evacuation is a highly effective strategy with a favorable safety profile for septated CSDH. By ensuring more complete evacuation via direct septal disruption, this technique facilitates faster recovery, significantly lowers recurrence, and improves long-term functional outcomes, justifying the longer operative time.