Related Experiment Video
Updated: Oct 18, 2026

Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome (ARDS)
Published on: April 7, 2021
Electrolyte redistribution during acute respiratory acid-base changes: an in vivo study using apnoea testing
Micah L A Heldeweg1, Martin Krbec2, Martin Vancura3
1Department of Anaesthesiology, Amsterdam University Medical Centres, Amsterdam, The Netherlands; Department of Intensive Care, Amsterdam University Medical Centres, Amsterdam, The Netherlands; Department of Anaesthesia and Intensive Care Medicine, The Third Faculty of Medicine, Charles University and FNKV University Hospital, Prague, Czech Republic.

Background:
Acute respiratory acid-base changes induce pH-dependent electrolyte redistribution. Although this response has been characterised in vitro, the in vivo changes depend on multicompartment buffering and remain poorly defined.
Methods:
We conducted a multicentre retrospective study of patients undergoing apnoea testing for organ donation after determination of brain death, a clinical model allowing in vivo study of acute ventilatory changes. The primary outcome was the pH-dependent change in strong ion difference (SID). Secondary analyses examined individual electrolytes, pH-SID effect modification by physiological variables, and how well the derived model agreed with observed SID changes compared with a simple bedside pH-correction method (ΔSID=-15×ΔpH).
Results:
In 263 participants, pH decreased from 7.40 (0.07) to 7.23 (0.07) and returned to 7.40 (0.08). Per pH unit increase, SID changed by -11.7 meq L-1 (95% CI -13.1 to -10.3; P<0.001), driven primarily by sodium ion (Na) (52% of change -7.2 mM; P<0.001) and chloride ion (Cl) (36% of change +3.7 mM; P<0.001). Higher haemoglobin concentration was associated with a higher pH-dependent SID change, together explaining 53% of within-patient variability. Agreement between predicted and observed SID changes was only modestly improved by using the derived model vs a simplified pH-correction model (sd of differences 1.74 vs 1.92 meq L-1).
Conclusions:
Acute respiratory acid-base disturbances produce in vivo Na and Cl redistribution associated with pH change that are modulated by haemoglobin concentration. The observed pH-dependent electrolyte redistribution is consistent with physiological buffering and can be reasonably approximated using a simple bedside pH-correction model.
Related Concept Videos
 01:18
Respiratory Regulation of Acid-Base Balance
When carbon dioxide levels increase in the blood, more H+ and HCO3⁻ are produced, leading to a...
 01:24
Diagnosing Acidosis and Alkalosis
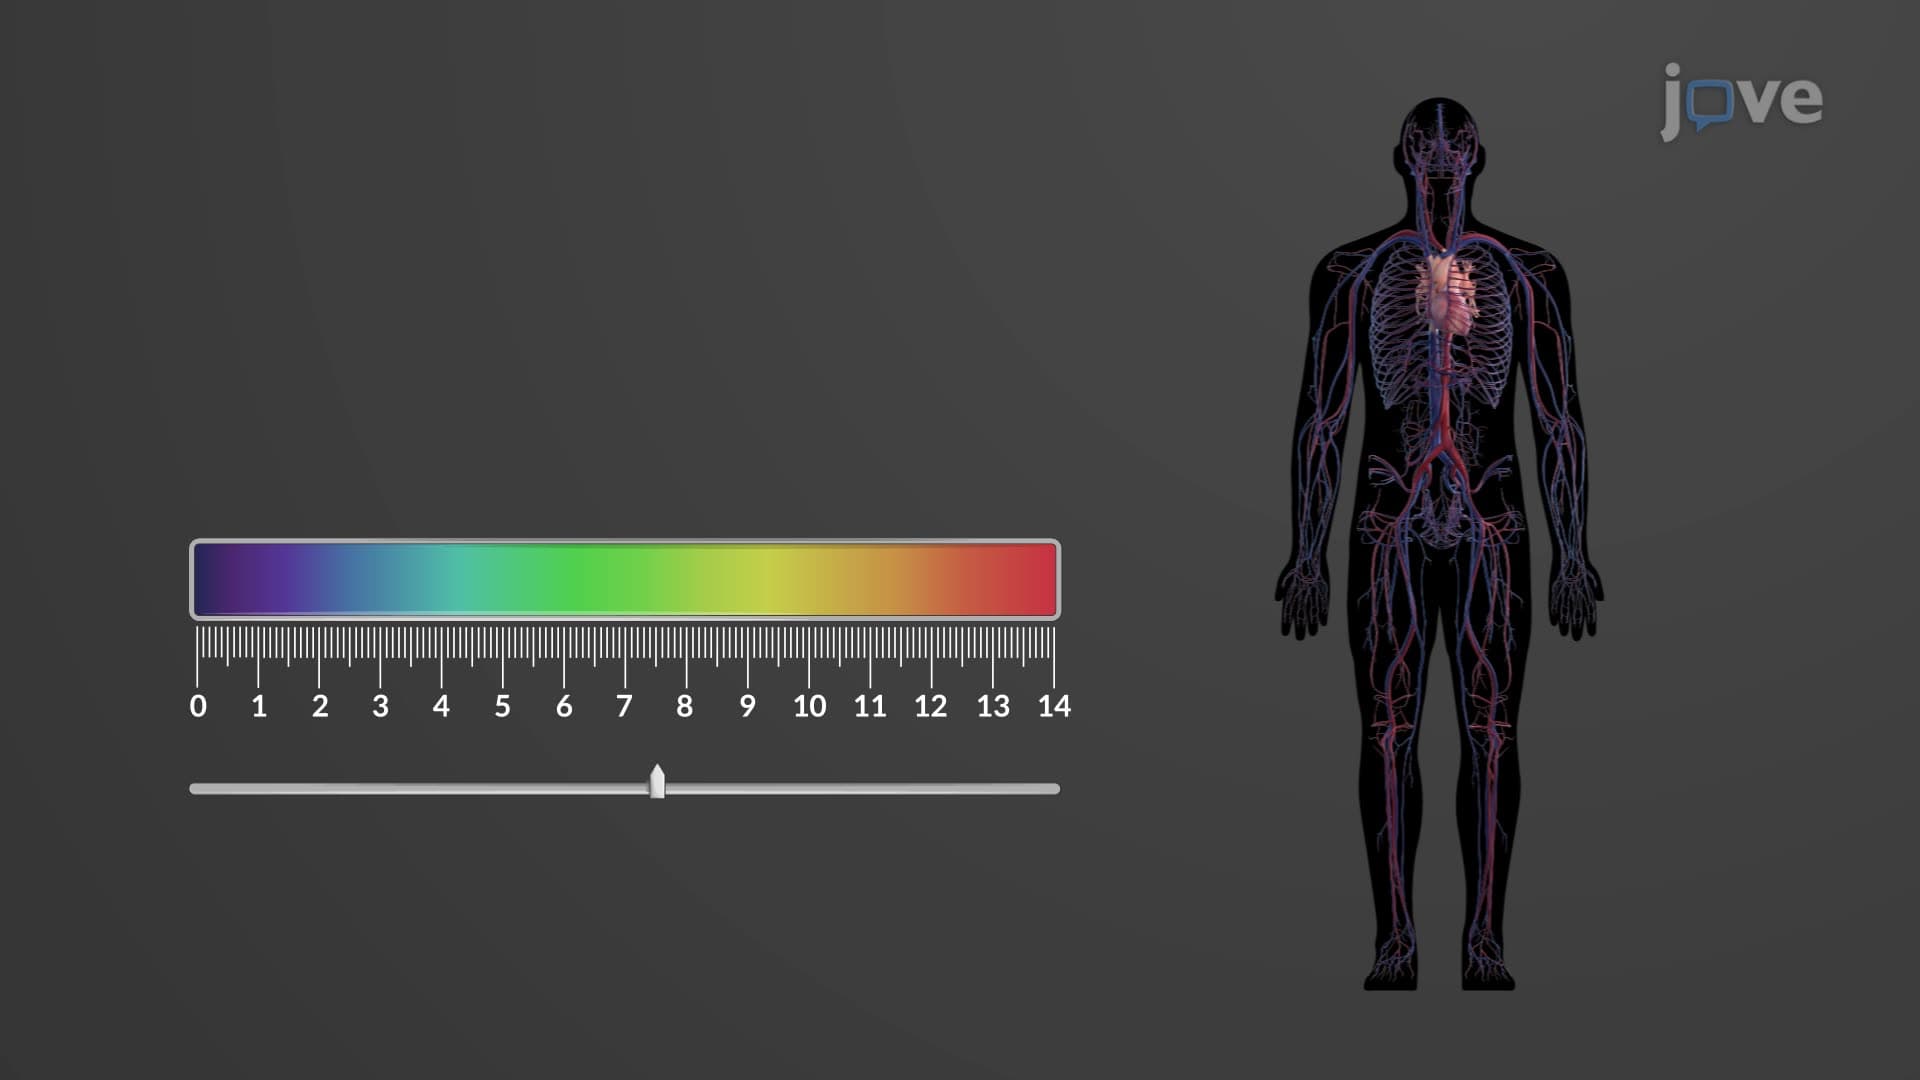
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and HCO3− values are examined to...
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...
 01:28
Compensation Mechanisms
Respiratory Compensation
This mechanism addresses metabolic-induced pH imbalances by adjusting breathing rates. Respiratory compensation begins within minutes of detecting a pH...
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting, or...