Related Experiment Video
Updated: Oct 18, 2026
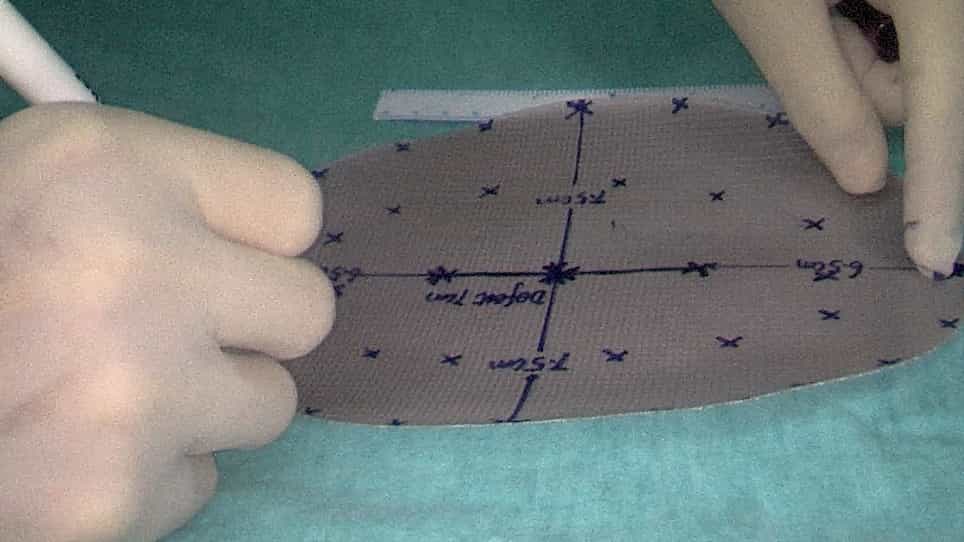
Application of a New Mesh Fixation Method in Laparoscopic Incisional Hernia Repair
Published on: December 23, 2022
International expert consensus on managing elective hernia repair in patients with Crohn's disease using the Delphi
Hans Lovén1,2, Frederik Helgstrand1, Hans Friis-Andersen3
1Center for Surgical Science, Zealand University Hospital, Køge, Denmark.

Background:
Patients with Crohn's disease (CD) may be predisposed to mesh-related complications such as impaired wound healing and fistula formation following hernia repair. With limited evidence and no established guidelines for hernia repair in CD, this Delphi study aimed to establish a hernia expert consensus on elective inguinal, incisional, and parastomal hernia repair in patients with CD.
Methods:
A three-round Delphi process including 21 hernia experts from Europe and the USA was conducted between 24 April and 15 October 2025. The primary outcome of interest was a consensus ≥ 75% among participants. Near consensus was defined as ≥ 70% agreement. Statements were developed from participant comments and questionnaire responses. Experts evaluated statements on timing, surgical approach, and mesh selection (synthetic non-absorbable, synthetic absorbable, biosynthetic, biological, and non-mesh) across different CD subtypes in elective inguinal, incisional, and parastomal hernia repair. Patients were categorized into three CD subtypes, namely abdominal fistulizing Crohn's disease (FCD), isolated perianal FCD, and non-FCD, with each assessed in both active and non-active inflammatory disease states.
Results:
Consensus or near consensus was achieved for 12 of 20 items (60%) in Round 1, 17 of 33 items (52%) in Round 2, and 13 of 29 items (45%) in Round 3. Overall, 42 of 72 unique items reached consensus (34 items) or near consensus (8 items). It was suggested that elective hernia repair should be avoided in CD patients with active inflammation, regardless of abdominal FCD or non-FCD. In non-active CD, synthetic non-absorbable mesh was suggested for inguinal, incisional, and parastomal hernia repair. Standard mesh placement was recommended for inguinal hernias, whereas retromuscular or preperitoneal mesh placement was recommended for incisional and parastomal hernias. No consensus was reached to avoid elective repair in isolated perianal FCD with active inflammation. The use of non-mesh repair, synthetic absorbable, biological, or biosynthetic mesh was generally not recommended in the elective setting.
Conclusions:
Consensus was reached that CD with non-active inflammation does not require deviation from standard hernia repair principles provided that the mesh is positioned in extraperitoneal positions. However, patients with CD may have an increased perioperative risk and the surgical management should be guided by shared decision-making.
