Related Experiment Videos
Microbiome-Endocannabinoidome Crosstalk as an Immunometabolic Rheostat in Inflammatory Disease
Reuben S Maghembe1,2, Donath Damian3, Samweli Bahati1,2
1Department of Microbiology and Parasitology, Faculty of Medicine St. Francis University College of Health and Allied Sciences Ifakara Tanzania.

Abstract:
Chronic inflammatory diseases reflect disrupted coordination among microbial ecology, epithelial barriers, lipid signaling, and immunity. The microbiome-endocannabinoidome (eCBome) axis is already recognized as a regulator of metabolism, permeability, and inflammatory tone; the unresolved issue is how to distinguish direct crosstalk from parallel or associative changes. This review therefore operationalizes the axis as an immunometabolic rheostat defined by five measurable domains: microbial functions and metabolites, compartment-specific eCBome ligands and enzymes, barrier integrity and microbial translocation, immune-cell programming, and tissue or clinical outcomes. We distinguish classical endocannabinoids (anandamide and 2-arachidonoylglycerol) from the endocannabinoid-related N-acylethanolamines palmitoylethanolamide and oleoylethanolamide, which act prominently through PPARα, TRPV1, GPR119, and related pathways. Evidence is appraised as direct causal, mechanistically supportive, associative, or hypothesis-generating. The strongest causal foundation links microbiota manipulation to intestinal eCBome tone, permeability, and metabolic endotoxemia, while disease-specific evidence is most developed in obesity-associated inflammation and inflammatory bowel disease. Engineered Lactobacillus paracasei platforms that produce PEA or OEA in situ provide particularly informative proof-of-concept because they couple a defined microbial perturbation to lipid-mediator release, receptor-dependent barrier effects, and inflammatory or metabolic outcomes. By contrast, evidence in MASLD/MASH, neuroinflammation, and systemic autoimmunity remains more compartment-dependent and heterogeneous. Clinical translation must account for the psychiatric toxicity that ended centrally active CB1 antagonism with rimonabant, the target and off-target complexity of FAAH/MAGL inhibition, and limitations of surrogate barrier biomarkers. A causal roadmap should combine gnotobiotic and loss-of-function models, isotope tracing, organoids, and gut-on-chip systems with tissue-resolved lipidomics and longitudinal, biomarker-enriched human trials.
Related Concept Videos
 01:18
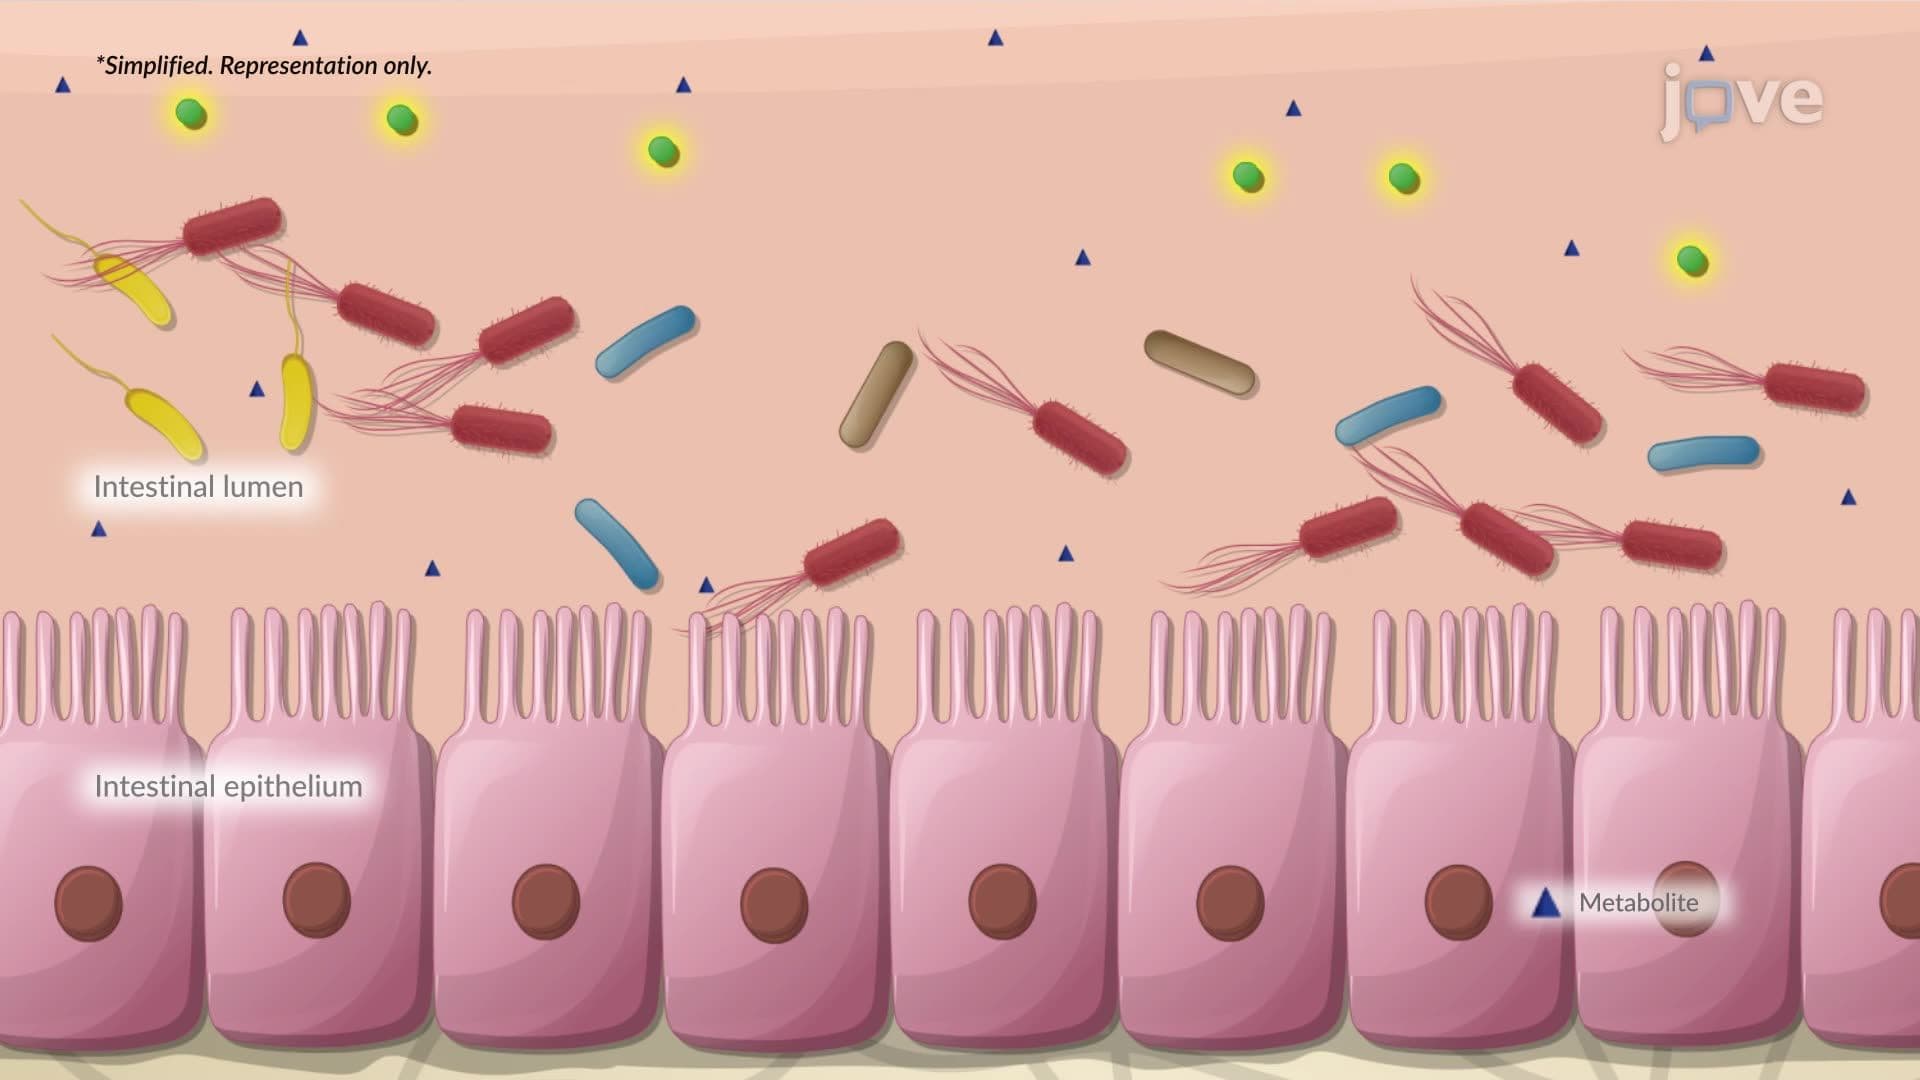
Dysbiosis of the Gut Microbiota
 01:22
Gut-Brain Axis
 01:25
Inflammatory Bowel Disease III: Crohn's Disease
 01:18
Functions of the Gut Microbiota
 01:21
Microbiota Modulation by Antibiotics
 01:27
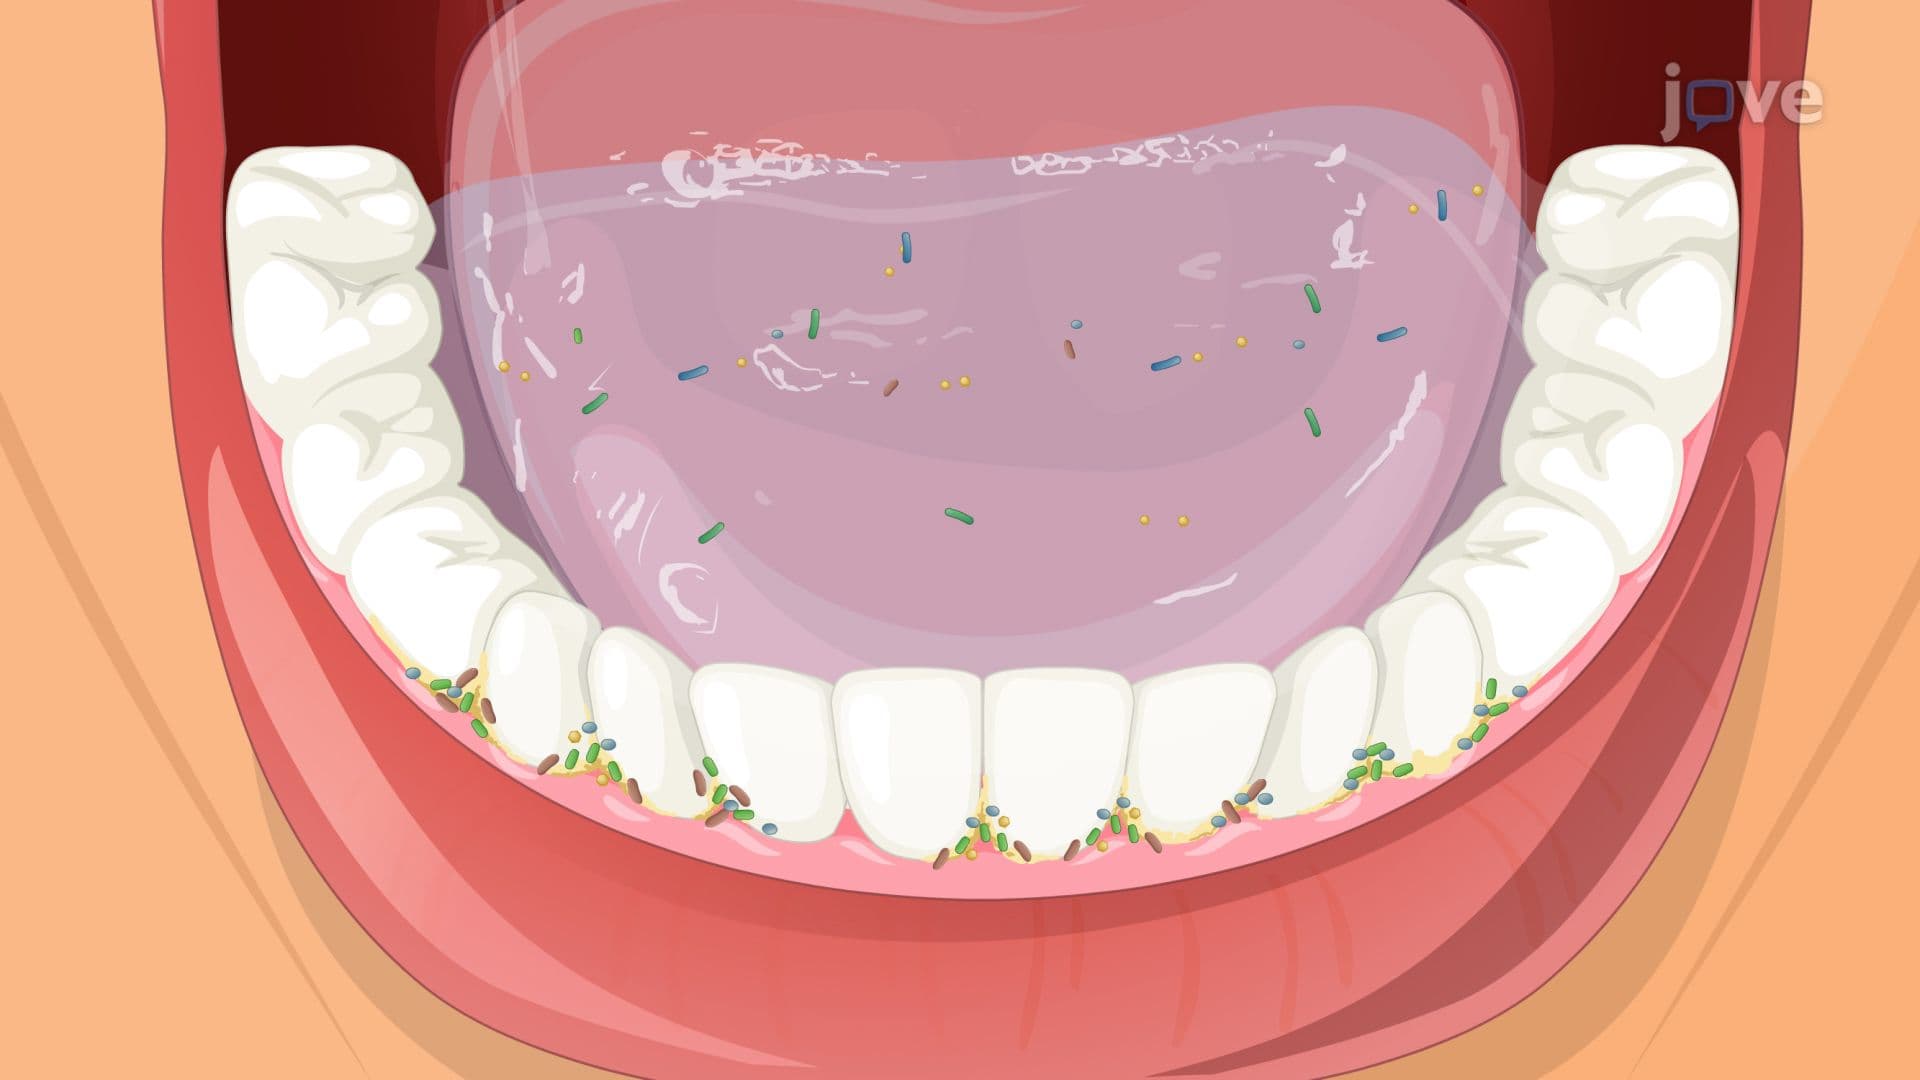
The Oral Microbiota