Related Experiment Video
Updated: Oct 19, 2026
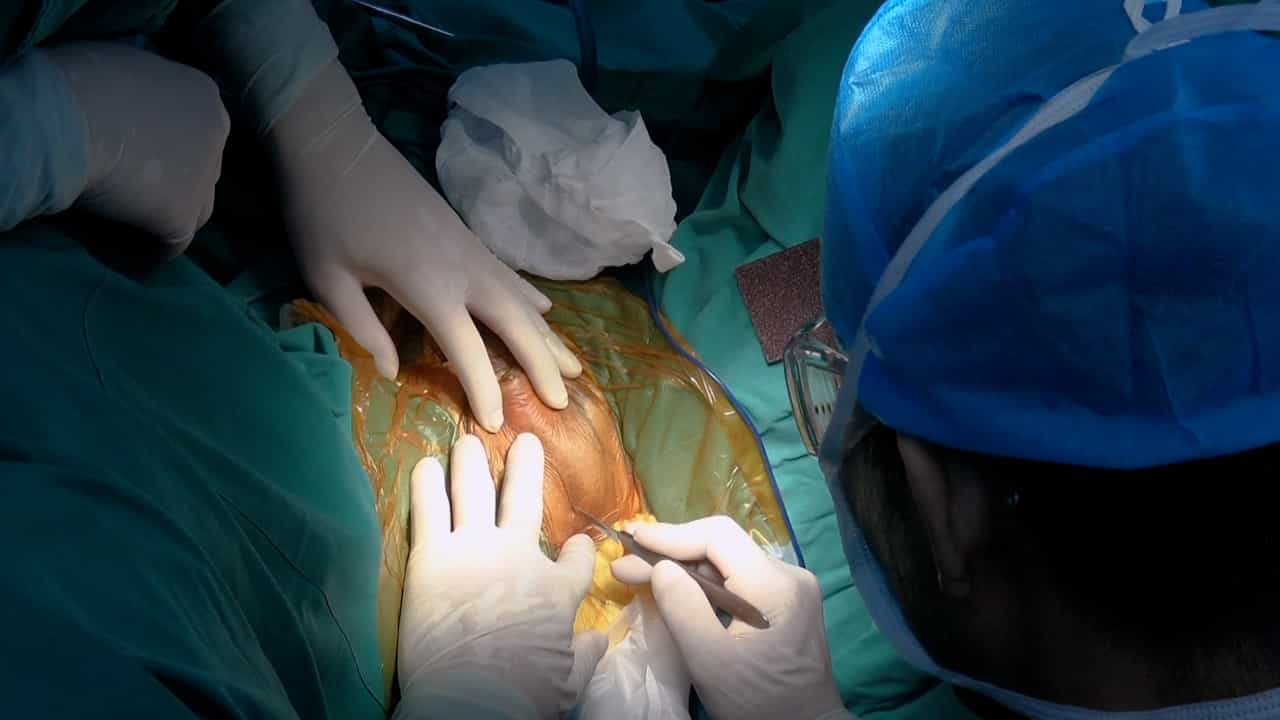
Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
Patient-Centered Transition to Clean Intermittent Catheterization After a Sacrectomy for Sacral Chordoma: A Case
Irina G Semenenko1, Mars Abdaev2, Alexander V Bulatov2
1Outpatient Department, Federal Neurosurgical Center, Ministry of Health of the Russian Federation, Novosibirsk, RUS.

Abstract:
Sacral chordoma may cause progressive neurological and pelvic organ dysfunction, while definitive surgery can require sacrifice of sacral nerve roots and result in permanent neurogenic bladder. We report a 57-year-old woman with an S2-S4 sacral chordoma presenting with severe lumbosacral pain and voiding dysfunction. Initial imaging demonstrated a 70 × 50 × 42 mm lesion extending into the sacral canal and presacral space. On day three, she underwent a limited decompressive resection of the intraspinal component to relieve root compression and obtain tissue for diagnosis. Histopathology and immunohistochemistry confirmed chordoma. Continued tumor growth was documented, reaching 72 × 51 × 81 mm by week 11. A two-stage procedure was then performed, consisting of endoscopic mobilization of the tumor and pelvic vessels followed by midline S2-S5 sacrectomy. The S1 roots were preserved, whereas the S2-S5 roots were sacrificed. Postoperatively, the patient developed clinically complete bladder atony with painless urinary retention and a bladder volume of 700 mL with 700 mL residual urine. Temporary urethral catheter drainage was used, and an Escherichia coli urinary tract infection was successfully treated. The catheter was removed three days before discharge, after which the patient learned and independently performed clean intermittent catheterization. At follow-up, she continued self-catheterization without significant psychological distress. Imaging at month six showed a small stable residual tumor without further growth; proton therapy had not been performed because of a postoperative cerebrospinal fluid collection. This case illustrates that selection of a bladder-emptying strategy after sacral tumor surgery should integrate oncological prognosis, neurological injury, functional status, patient preferences, and structured education. Clean intermittent catheterization can remain feasible even after initial apprehension when training is individualized and supported across inpatient and outpatient care.
