Related Experiment Video
Updated: Oct 19, 2026

Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Early respiratory effects of long-term cement dust exposure: association with exercise capacity in asymptomatic
Konstantinos Pigakis1,2, Aggeliki Kontopodi3, Vasileios Stavrou4
1Department of Respiratory Medicine, Creta InterClinic Hospital, Heraklion, Greece. k_pigakis@yahoo.gr.

Purpose:
Long-term occupational exposure to cement dust is associated with respiratory disease, yet early subclinical impairment may not be detected using conventional spirometry. This study aimed to investigate small airway dysfunction (SAD) as an early marker of respiratory effects and its association with exercise capacity in asymptomatic cement workers.
Methods:
We studied 500 non-smoking, non-asthmatic, non-atopic cement industry workers aged 35 years or older, with at least 10 years of occupational exposure to cement dust. Participants underwent spirometry, static lung volume measurements, impulse oscillometry (IOS) and cardiopulmonary exercise testing (CPET). Workers with evidence of SAD were compared to those with normal small airway function.
Results:
Small airway dysfunction was identified in a subset of workers despite preserved spirometry. The SAD group exhibited a 19.4% reduction in VO2 peak compared to the non-SAD group (29 ± 2.3 vs. 36 ± 2.0 ml/kg/min, p < 0.05). This functional limitation was further characterised by a significantly lower breathing reserve (34% vs. 43%, p < 0.05) and increased ventilatory requirements during exercise.
Conclusions:
Subclinical respiratory impairment may occur in a significant proportion of asymptomatic workers with long-term exposure to cement dust. SAD may serve as an early functional marker of occupational lung disease. Conventional spirometry underestimates the functional impact of exposure; therefore, sensitive techniques should be integrated into occupational surveillance for early detection and support preventive workplace strategies.


Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
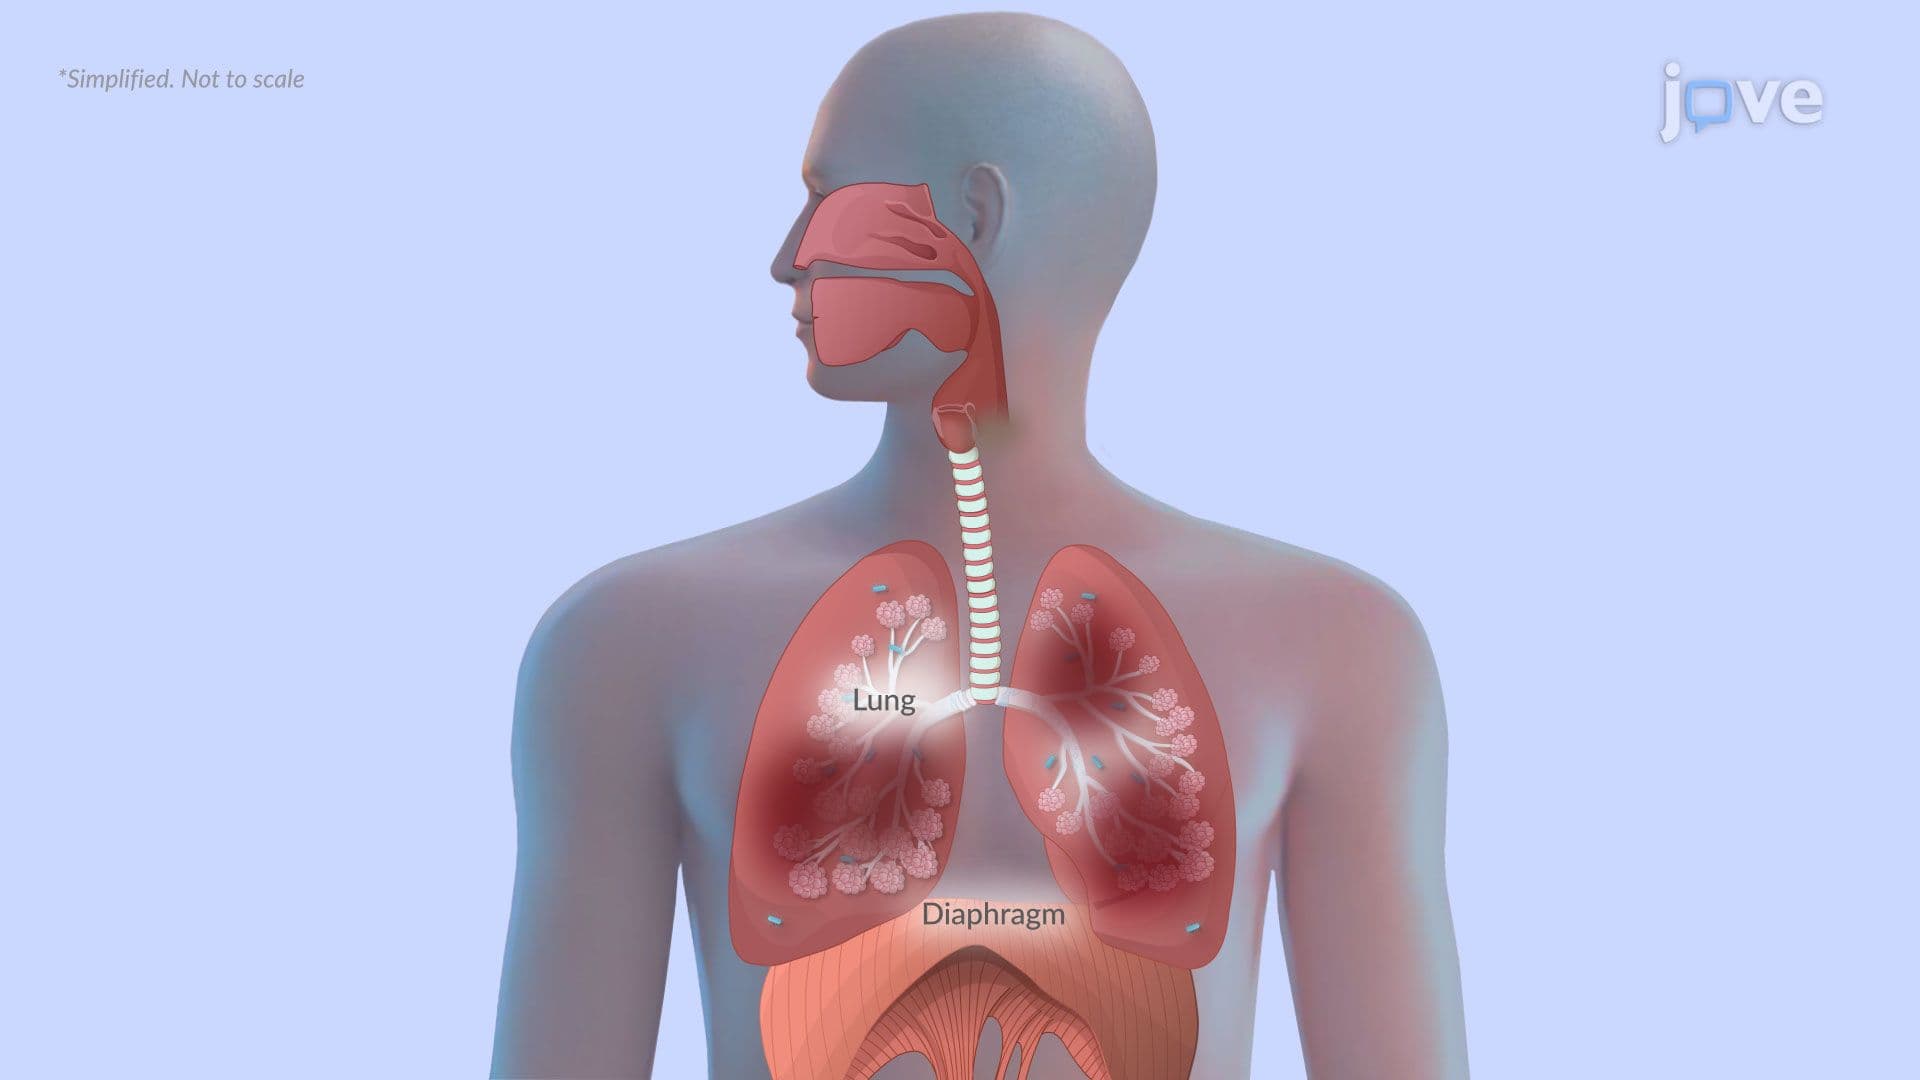 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
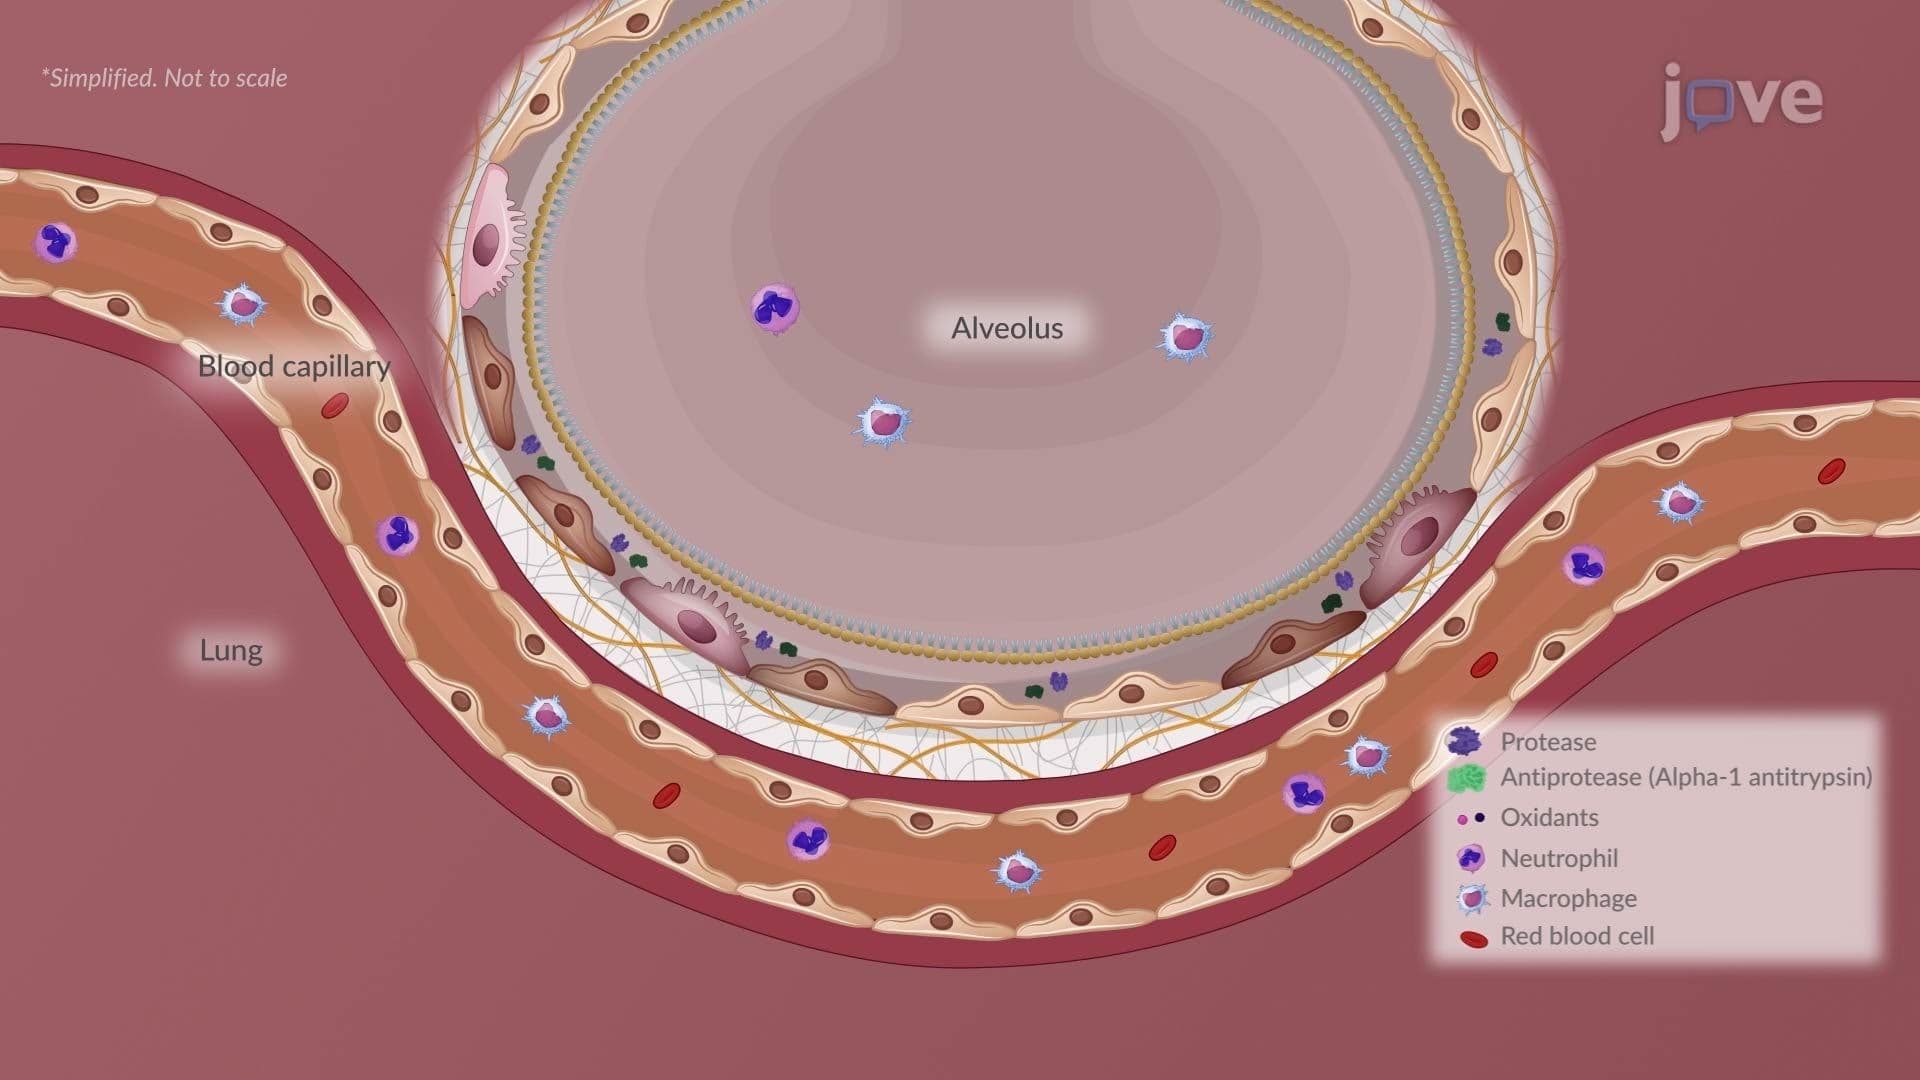 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...