Related Experiment Video
Updated: Oct 19, 2026
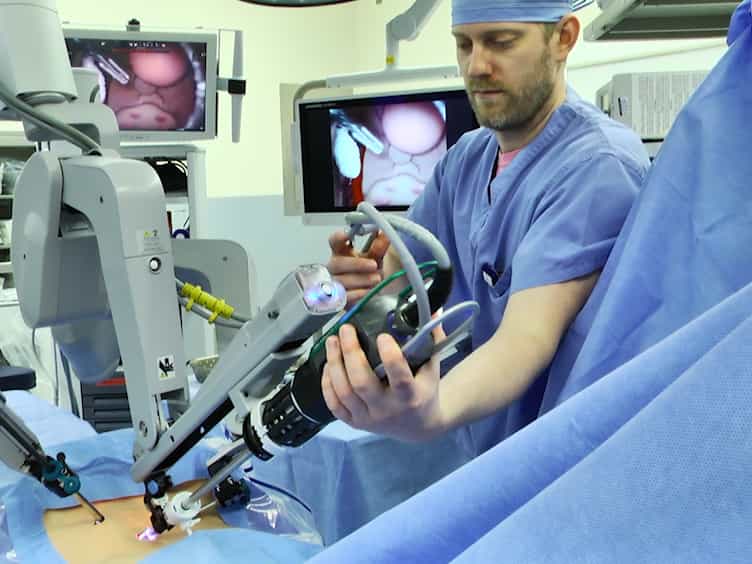
Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Robotic Simulation Training in Reducing the Learning Gap Between Expert Surgeons and Novice Trainees: A Prospective
Man Hon Tang1, Audrey Ng Jing Ting1, Joachim Yau Wen Kien1
1Department of Surgery, Woodlands Hospital, Singapore, Singapore.

Objective:
Robotic-assisted surgery is increasingly adopted across surgical disciplines, yet structured training paradigms for novice trainees remain limited. Whether simulation-based robotic training can narrow the technical skill gap between experienced surgeons and trainees with varying levels of surgical experience is not well established. We aim to evaluate whether novice trainees can achieve comparable robotic suturing proficiency to expert surgeons following a standardised robotic simulation training programme, and to characterise the perceived learning curves across cohorts of varying surgical experience.
Design:
A prospective, single-blinded study was conducted at Woodlands Hospital, Singapore, using the Cornerstone Robotics Sentire Surgical System.
Setting:
Following simulation training modules, participants performed a standardised robotic suturing task. Two blinded assessors independently scored performance using the validated Global Evaluative Assessment of Robotic Skills (GEARS) instrument. Task completion time and participant self-assessment questionnaire scores were collected as secondary outcomes.
Participants:
Four different cohorts with 5 participants each were recruited: Consultant surgeons (CS), Surgical Residents (SR), Non-surgical trainees (NST) and Year-5 Medical Students (M5). All participants were naïve to robotic surgery.
Results:
Mean total GEARS scores 26.4, 23.5, 19.2 and 13.7 (out of 30) in the CS, SR, NST and M5 groups respectively. There was no significant difference in scores between CS and SR group (p=0.489) but scores were significantly lower for NST and M5 when compared to the CS (p=0.013 and p<0.001). Median task completion times were: 5.92, 5.87, 9.75 and 14.0 minutes in the CS, SR, NST and M5 group respectively. Only the M5 timings were significantly longer compared to CS (p=0.08). Self-reported questionnaire scores showed a similar hierarchical pattern.
Conclusions:
Robotic simulation training can potentially narrow the technical skills gap between expert surgeons and trainees, particularly for surgical residents. These findings support the integration of earlier robotic training in surgical education curricula.