Related Experiment Video
Updated: Oct 19, 2026
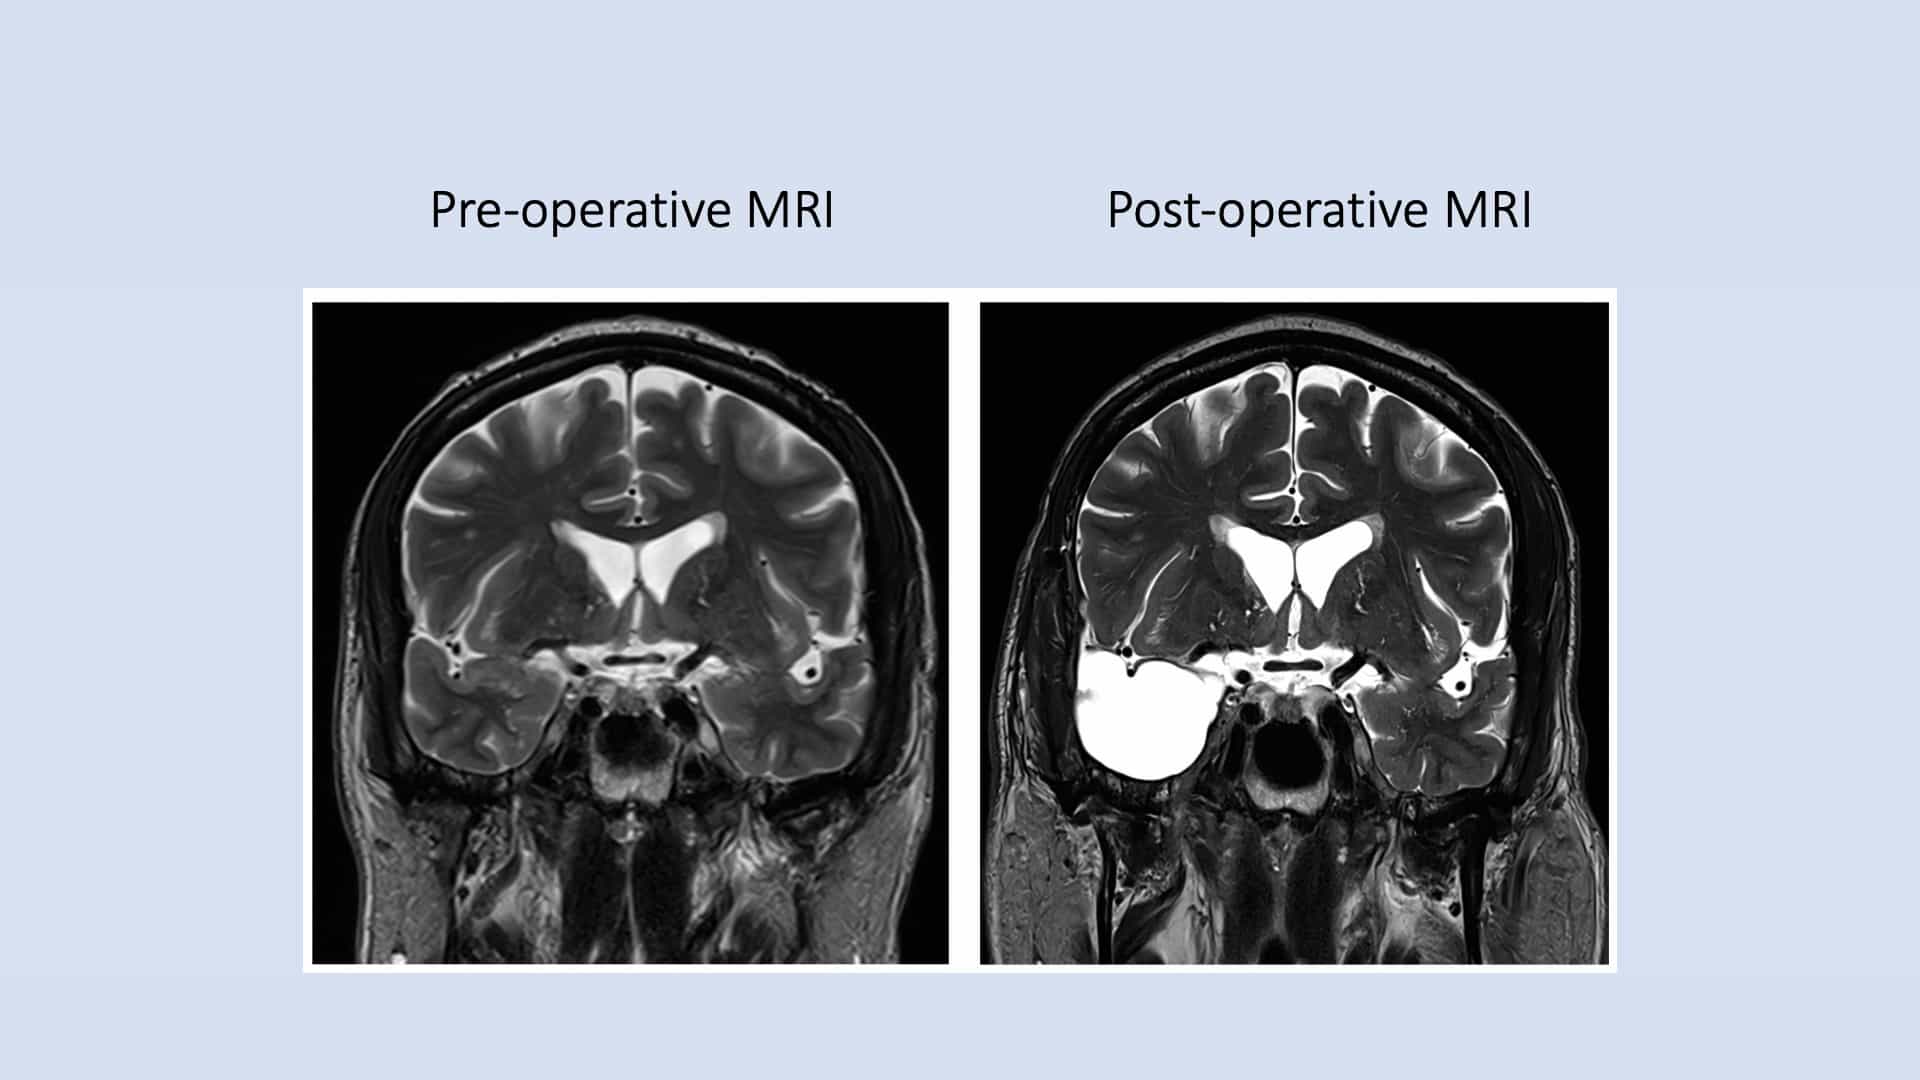
Anteromesial Temporal Lobectomy for Medically Intractable Temporal Lobe Epilepsy: An Operative Study
Published on: August 15, 2025
Contralateral piriform cortex alterations after surgery for temporal lobe epilepsy: A pilot MRI volumetry study
Gökhan Pek1, Sena Ünal2, İhsan Doğan3
1Ankara University Faculty of Medicine, Department of Neurology, Ankara, Türkiye.

Purpose:
Temporal lobe epilepsy (TLE) is increasingly conceptualized as a network disorder, with the piriform cortex as an implicated region. We characterized postoperative contralateral piriform cortex-cortical amygdala (PCA) structural and perfusion-related changes in a small seizure-free TLE cohort.
Methods:
Nine patients with drug-resistant TLE who underwent epilepsy surgery and achieved postoperative seizure freedom were included in this single-center pre-post pilot study. Bilateral PCA was manually delineated on 3D T1-weighted MRI using ITK-SNAP, and volumes were normalized to total intracranial volume derived from CAT12 segmentation. Eight atlas-derived contralateral temporal lobe regions were examined as exploratory regional-specificity comparisons. In patients with available pulsed arterial spin labeling (PASL), piriform and putaminal signal intensities were measured by region-of-interest analysis. Non-parametric paired tests were used; secondary and exploratory analyses were corrected using the Benjamini-Hochberg false discovery rate (FDR) procedure.
Results:
Normalized to total intracranial volume (TIV) contralateral PCA volume decreased postoperatively (Wilcoxon Z = -2.073, exact two-tailed p = 0.039; r = 0.69). None of the eight atlas-derived contralateral temporal regions showed a significant pre-post volume change. Contralateral putamen-normalized piriform signal intensity did not change significantly (Z = -0.105, p = 0.917), and no secondary or exploratory analysis remained significant after FDR correction.
Conclusions:
In this hypothesis-generating pilot cohort, contralateral PCA volume decreased after epilepsy surgery, whereas the PASL-derived signal-intensity measure did not show a corresponding group-level change. These observations do not establish a surgery-induced network mechanism and require confirmation in larger controlled longitudinal cohorts.
