Related Experiment Video
Updated: Oct 20, 2026
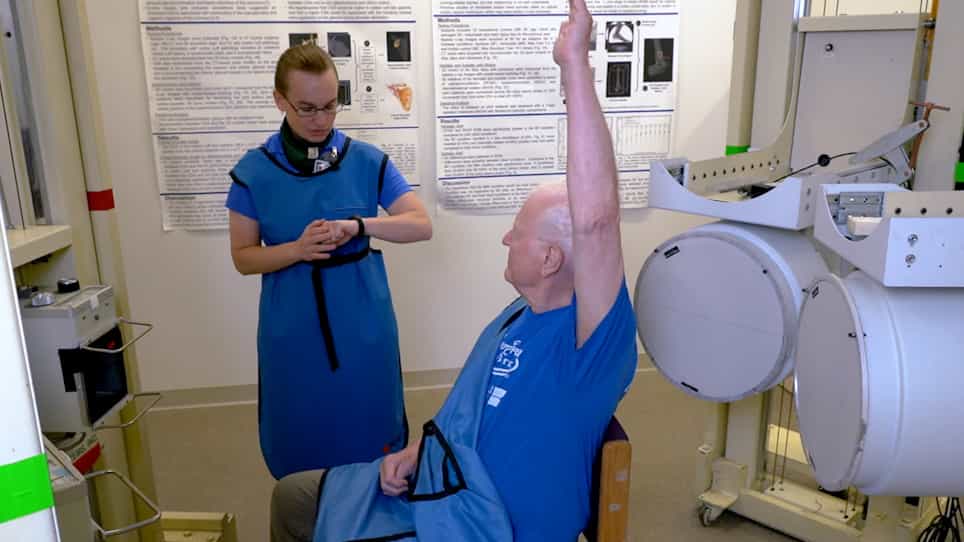
Measuring 3D In-vivo Shoulder Kinematics using Biplanar Videoradiography
Published on: March 12, 2021
Biomechanical analysis of shoulder pseudoparalysis as per the Collin classification of massive rotator cuff tears: an
David T Axford1, Robert Potra2, Richard Appleyard2
1Department of Mechanical and Materials Engineering, Western University, London, Canada; Macquarie University Translational Orthopaedic Research Lab (MQ TOR LAB), Faculty of Medicine, Health and Human Sciences, Macquarie University, Sydney, Australia.

Abstract:
Clinical investigations have shown strong correlations between rotator cuff tear patterns and reduced active range of motion; however, no biomechanical study has investigated the effect of tear pattern on shoulder function for all Collin classification types. The purpose of this study was to investigate the effect of rotator cuff tear pattern on joint kinematics, muscle function, and acromial strains during simulated ex-vivo shoulder elevation. An ex-vivo shoulder simulator performed four motions including scapular plane abduction, forward flexion, internal rotation, and external rotation in seven cadaveric specimens (mean age 56 ± 6 years). Each motion was performed for seven shoulder conditions: intact, supraspinatus deactivation (type S), and deactivation types A through E according to the Collin classification. Joint kinematics, muscle force, and acromial strains were reported for each motion and condition. Deactivation of three rotator cuff tendons resulted in a significant reduction in arm elevation during scapular plane abduction and forward flexion (p≤.012 for type B, C, and E) while deactivation of the entire anterior or posterior rotator cuff resulted in loss of internal or external rotation active range of motion (p<.001). All deactivation patterns led to higher anterior and lateral deltoid forces than the intact shoulder (p≤.049). Internal and external rotation stability was maintained in types A and D with significantly higher force in the inferior subscapularis and teres minor (p<.001), respectively. Finally, rotator cuff deactivation led to increased maximum principal strain in the acromion and scapular spine compared to the intact shoulder.
