Related Experiment Video
Updated: Oct 20, 2026
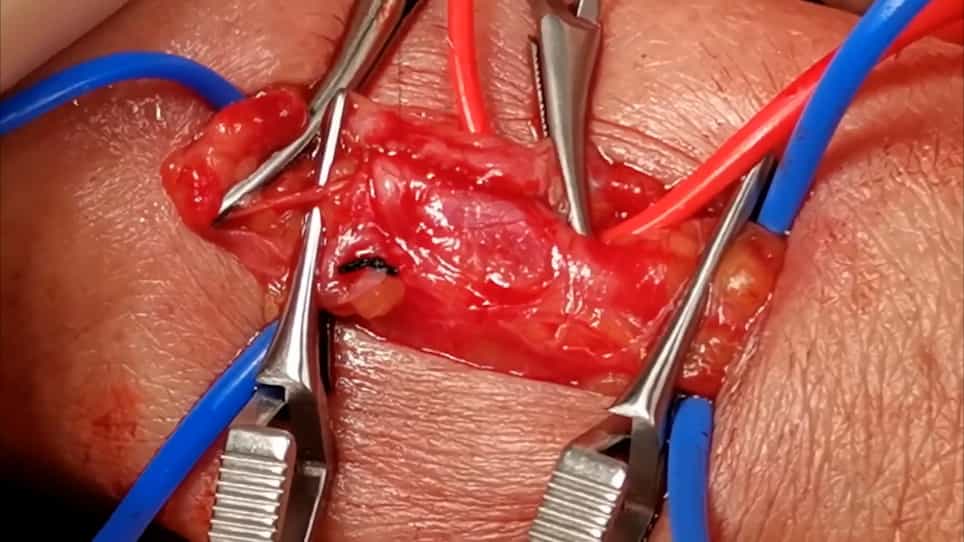
Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
A single-center before-and-after study of physiology-first algorithmic surveillance versus standard observation for
Ari D Kramer1, Tyler Cunningham1
1Division of Vascular Access, Department of Surgery, Spartanburg Regional Medical Center, Spartanburg, SC.

Objective:
To evaluate whether a structured, physiology-first surveillance protocol improves arteriovenous fistula clinical maturation rates and reduces time to cannulation readiness compared with standard postoperative observation.
Methods:
Two consecutive cohorts of surgically created arteriovenous fistulas by a single surgeon at a community-based center were compared: a standard observation cohort (January-May 2025; 64 created, 58 analyzable) and a physiology-first cohort (June 2025-March 2026; 52 created, all analyzable) managed with a structured protocol featuring standardized 2.7-mm anastomosis, day-of-creation baseline flow documentation, structured ultrasound surveillance at weeks 2 and 4, and defined failure-to-progress intervention triggers and procedure. Salvage intervention for both cohorts included kinetic endovascular micro-incision creation followed by angioplasty with a drug-coated balloon.
Results:
Overall maturation increased from 75.9% (44/58) to 92.3% (48/52; P = .022). Unassisted maturation rose from 53.4% (31/58) to 69.2% (36/52). The overall median time to clinical maturation decreased from 49 days (interquartile range, 42-68) to 30 days (interquartile range, 26-43; P < .001). Salvage intervention success was comparable between cohorts. Day-of-creation flow documentation increased from 0% to 100%, and no steal syndrome was observed (0/52) with the new physiology-first protocol.
Conclusions:
As a quality-improvement evaluation, the physiology-first protocol generated a clear and consistent signal of improved maturation outcomes: access failure decreased, unassisted maturation increased, overall maturation increased, and median time to cannulation readiness decreased. These findings support adopting the protocol as a meaningful adjunct to care and warrant multicenter evaluation.