Related Experiment Video
Updated: Oct 20, 2026
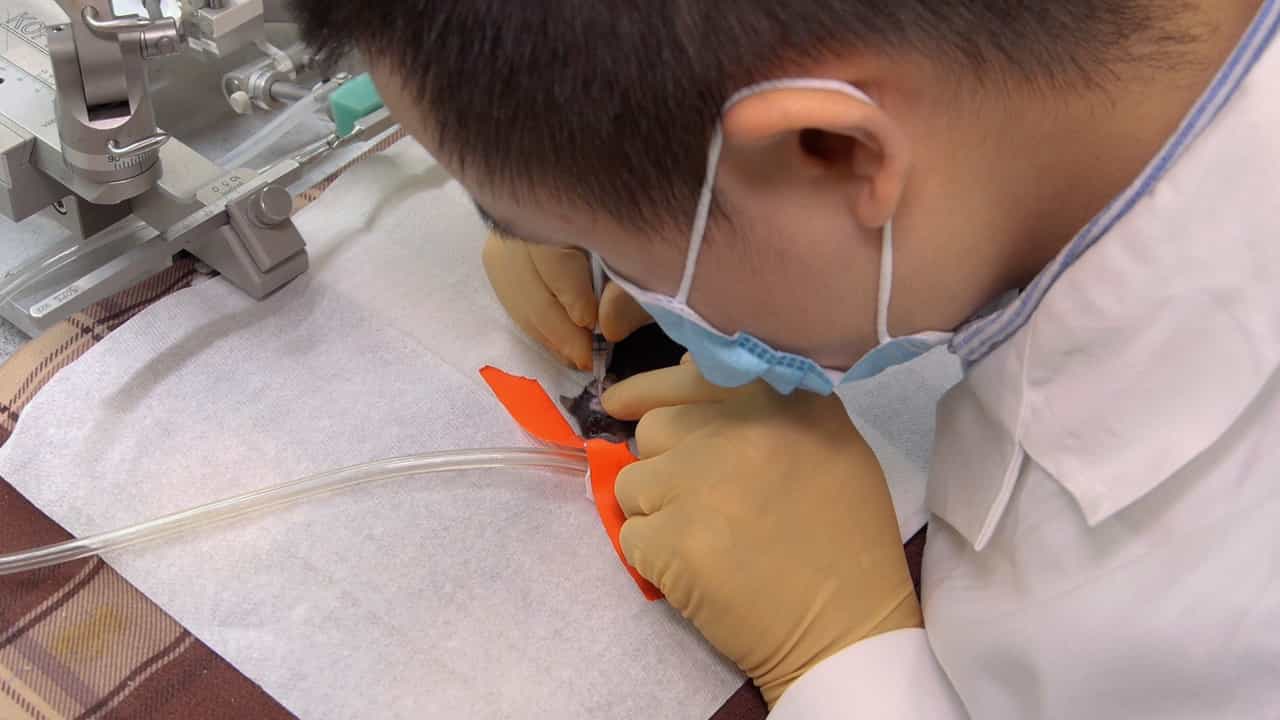
Temporomandibular Joint Pain Measurement by Bite Force and Von Frey Filament Assays in Mice
Published on: September 13, 2024
Association between malocclusion and temporomandibular joint disorders: evidence from a Mendelian randomization study
Zhouqiang Wu1,2, Sen Wang1, Chang Liu1
1Department of Orthodontics, Stomatology Hospital, School of Stomatology, Zhejiang University School of Medicine & Clinical Research Center for Oral Diseases of Zhejiang Province & Key Laboratory of Oral Biomedical Research of Zhejiang Province & Cancer Center of Zhejiang University, 310006 Hangzhou, Zhejiang, China.

Background:
Although malocclusion and temporomandibular joint disorders (TMD) frequently co-occur in clinical practice, controversy persists regarding whether this overlap reflects a pathophysiological causal relationship or incidental concurrence. This study aimed to investigate the potential association between malocclusion and TMD using a bidirectional two-sample Mendelian randomization (MR) approach.
Methods:
Bidirectional two-sample MR was performed to evaluate the potential causal relationship between malocclusion and TMD. Summary statistics for malocclusion were obtained from the FinnGen consortium, while TMD datasets were obtained from the FinnGen consortium and an independent genome-wide association study (GWAS) of the UK Biobank (UKB). To account for multiple comparisons, a Bonferroni-corrected significance threshold of 0.00625 was applied. The strength of the instrumental variables (IVs) was assessed using F-statistics. Causal inference was conducted using multiple MR methods, including inverse variance weighted (IVW), maximum likelihood estimation, MR-Egger regression, weighted median (WM), and penalized weighted median analyses. Sensitivity analyses were performed using Cochran's Q test for heterogeneity, MR-Egger intercept analysis, Mendelian Randomization Pleiotropy RESidual Sum and Outlier (MR-PRESSO) global outlier assessment, and iterative leave-one-out validation.
Results:
Convergent evidence from IVW, WM, and penalized weighted median estimators suggested potential causal effects of distal bite, deep bite, and open bite on TMD susceptibility. After Bonferroni correction, deep bite remained significantly associated with TMD. The mean F-statistics for the IVs ranged from 22.23 to 23.62 across malocclusion types, indicating adequate instrument strength. Reverse MR analysis using 130 TMD-related Single Nucleotide Polymorphisms (SNPs) showed no evidence supporting a causal effect of TMD on malocclusion.
Conclusions:
This MR study provides evidence that several malocclusion types, including distal bite, deep bite, and open bite, are potentially causally associated with TMD, with deep bite showing the strongest association.
