Related Experiment Video
Updated: Oct 21, 2026
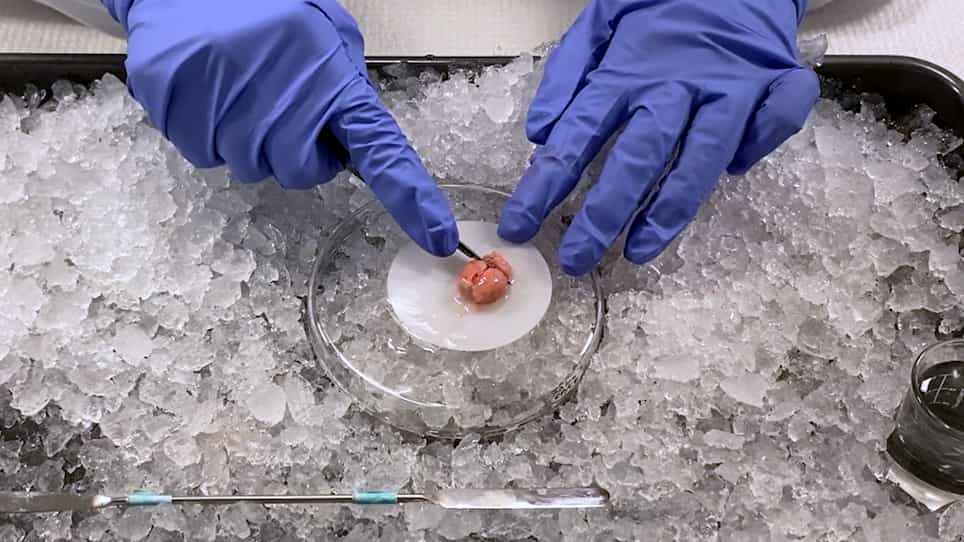
Assessing Changes in Synaptic Plasticity Using an Awake Closed-Head Injury Model of Mild Traumatic Brain Injury
Published on: January 20, 2023
Developing an Empirically Derived Head Trauma Burden Assessment Score for Intimate Partner Violence-related
Nicola L de Souza1, Divya Jain, Eamonn Kennedy
1Author Affiliations: Traumatic Brain Injury and Concussion Center, Department of Neurology, University of Utah School of Medicine, Salt Lake City, Utah (de Souza, Kennedy, Clark, Read, Velez, Andersen, Tate, E. A. Wilde, and Esopenko); George E. Wahlen VA Salt Lake City Healthcare System, Salt Lake City, Utah (Kennedy and Andersen); Department of Rehabilitation and Human Performance, Icahn School of Medicine at Mount Sinai, New York City, New York (Jain, Carlsson, Dorman, Kajankova, Olis, and Esopenko); Division of Epidemiology, University of Utah School of Medicine, Salt Lake City, Utah (Kennedy); Department of Psychology, Pennsylvania State University, University Park, Pennsylvania (Baird, Carter, Chase, Cwiek, Lan, Lockhart, Méndez-Fernández, Mullin, Rebuck, Sakamoto, and Hillary); cBRAIN, Department of Child and Adolescent Psychiatry, Psychosomatics, and Psychotherapy, Ludwig-Maximilians-University, Munich, Germany (Koerte); Psychiatry Neuroimaging Laboratory, Department of Psychiatry, Mass General Brigham, Harvard Medical School, Boston, Massachusetts (Koerte, and Lin); Department of Psychology, Virginia Polytechnic Institute and State University, Blacksburg, Virginia (Read, and Marshall); Department of Radiology, Brigham and Women's Hospital, Harvard Medical School, Boston, Massachusetts (Lin); Center for Clinical Spectroscopy, Brigham and Women's Hospital, Harvard Medical School, Boston, Massachusetts (Lin); and Social Life and Engineering Sciences Imaging Center, University Park, Pennsylvania (Hillary).

Objective:
To develop a statistically derived and clinically informed intimate partner violence-related head trauma (IPV-HT) Burden Assessment Score that accounts for diverse brain injury mechanisms (eg, nonfatal strangulation, blunt force), exposure chronicity, and injury severity.
Setting:
Community-based sample.
Participants:
Females (N = 146; 38.7 ± 10.2 years old, 56.8% White/Non-Hispanic) reporting at least 1 IPV-HT on the Brain Injury Screening Questionnaire IPV module (BISQ-IPV).
Design:
Cross-sectional analysis.
Main Measures:
Candidate variables representing injury mechanism, frequency, severity, and IPV relationship history were extracted from the BISQ-IPV. Multicollinearity screening and multivariable linear regression selected variables predicting Rivermead Postconcussion Symptoms Questionnaire (RPQ) total scores. Leave-one-out elimination identified the most predictive variables determined by change in R2 when removed. Retained variables were standardized and combined to calculate the IPV-HT Burden Assessment Score, normalized to range 1-100 (low-to-high burden). Scores were correlated with Adverse Childhood Experiences questionnaire (ACEs), Headache Impact Test (HIT-6), cognition subscale of the Quality of Life in Neurological Disorders (NeuroQoL), Post-traumatic Stress Disorder Checklist for DSM-5 (PCL-5), Generalized Anxiety Disorder (GAD-Q-IV), and Center for Epidemiologic Studies Depression Scale (CES-D).
Results:
Five variables were retained in the final model, achieving 25% explainability of RPQ total scores (R2 = 0.25; adjusted R2 = 0.22). Count of unique IPV-related brain injury mechanisms explained most RPQ variance (∼19%), followed by number of IPV relationships, and duration of the 3 most severe relationships. The model also retained the proportion of injuries due to nonfatal strangulation meeting brain injury criteria and the average brain injury severity. The final IPV-HT Burden Assessment Score (mean = 31.7 ± 18.24, range = 2-86) positively correlated with ACEs (r = 0.17, P = 0.043), HIT-6 (r = 0.27, P = 0.001), PCL-5 (r = 0.23, P = 0.006), GAD-Q-IV (r = 0.17, P = 0.043), and CES-D (r = 0.29, P < 0.001) and negatively correlated with NeuroQoL T-scores (r = -0.30, P < 0.001).
Conclusions:
The IPV-HT Burden Assessment Score captures diverse IPV-HT exposures and shows preliminary validity through associations with psychosocial and neurological outcomes.

