Effects of EEG neurofeedback in adults with attention-deficit/hyperactivity disorder: a systematic review of
Małgorzata Rotkiewicz1, Yassine Yachou2, Sofia Charef2
1Département de Recherche Clinique, Pôle Universitaire G03, Ville-Evrard Hôpital, 202 Avenue Jean Jaurès, Neuilly- sur-Marne, France. m.rotkiewicz@epsve.fr.

Background:
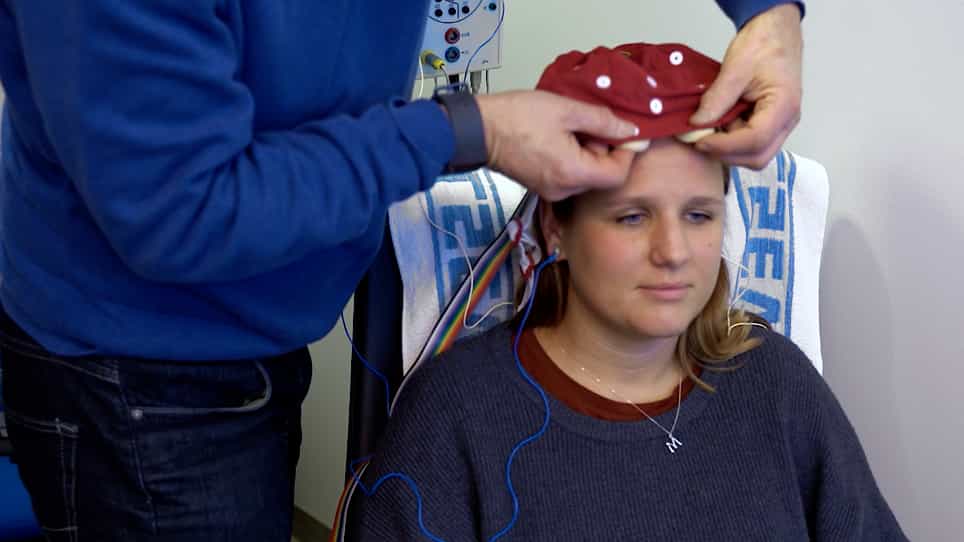
Pharmacotherapy is recommended as the first-line treatment for adult attention-deficit/hyperactivity disorder (ADHD), yet some individuals show partial or inadequate response associated with adverse effects. These limitations have prompted interest in adjunctive or alternative interventions. Electroencephalography (EEG) neurofeedback is a non-pharmacological intervention for ADHD, which enables self-regulation of neural activity. This systematic review synthesised clinical, cognitive, and electrophysiological outcomes of EEG neurofeedback in adult ADHD, and examined standard versus personalised training protocols.
Methods:
Following PRISMA guidelines, four databases (PubMed, ScienceDirect, Ovid, Web of Science) were searched from 1960 to October 2025 for this PROSPERO-registered review (ID: CRD420251020898). Eligible studies included adults (≥ 18 years) with a formal ADHD diagnosis undergoing EEG neurofeedback. Outcomes comprised symptom severity, cognitive performance, electrophysiology, and adverse events. Risk of bias was assessed using RoB 2 and ROBINS-I V2.
Results:
Seven studies (three RCTs, four non-randomised; n = 390) met inclusion criteria. Protocols included theta/beta (n = 1), slow cortical potential (n = 1), alpha downregulation training (n = 1) and personalised approaches guided by individual alpha peak frequency (n = 3) or QEEG profiles (n = 1). Naturalistic and personalised studies reported large symptom reductions, whereas RCTs revealed small, generally non-significant effects relative to controls. Cognitive improvements were inconsistently reported and largely attributable to practice effects. Electrophysiological changes were protocol-specific without convergence across studies. No treatment-related adverse events were observed.
Conclusions:
Evidence remains limited by methodological heterogeneity, small samples, variable controls, inconsistent learning metrics, and risk of bias. Current RCTs do not demonstrate evidence of efficacy over placebo. Blinded, adequately powered trials using standardised learning measures are needed to clarify mechanisms of neurofeedback.

