Related Experiment Video
Updated: Oct 22, 2026
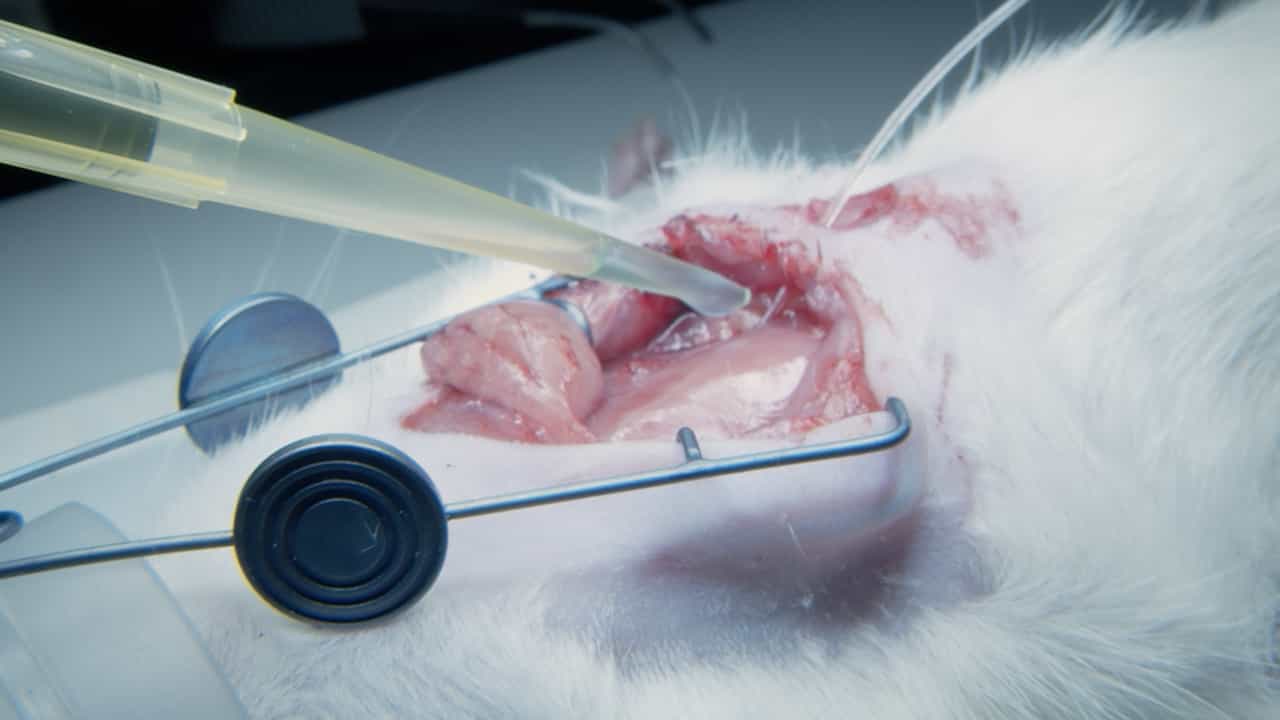
Cervical Lymph Duct-Cannulated Rat Model for Assessing Lymphatic Transport from the Head and Brain
Published on: March 10, 2026
Intracranial lymphatic dysfunction after traumatic brain injury: Imaging biomarkers, neural repair, and non-invasive
Yuheng Cui1, Yang Liu2, Weiwei Jiang3
1Department of Neurosurgery, Xuanwu Hospital, Capital Medical University, Beijing, China.

Abstract:
Traumatic brain injury initiates secondary processes that may persist long after the initial mechanical insult. These processes may be amplified when tissue fluid, cellular debris, inflammatory mediators, metabolites, and abnormal proteins accumulate faster than the brain can redistribute or eliminate them. The relevant clearance apparatus is a serial-parallel network comprising cerebrospinal fluid-interstitial fluid exchange, perivascular transport, brain-meningeal interfaces, meningeal lymphatic vessels, and cranial, spinal, and cervical outflow pathways. Traumatic brain injury may disrupt this network through altered aquaporin-4 polarization, blood-brain barrier dysfunction, edema, pressure abnormalities, disturbed sleep and autonomic regulation, and neuroinflammation. This dysfunction does not necessarily represent a uniform reduction in flow; rather, it may involve phase- and phenotype-specific transport bottlenecks. This review integrates these mechanisms within an injury-clearance-repair framework, evaluates available imaging biomarkers, and classifies therapeutic evidence according to the directness of transport-target engagement. Current evidence remains predominantly preclinical, and most non-invasive interventions require mechanistic validation specifically in traumatic brain injury. Translation will depend on compartment-specific biomarkers, phase-appropriate safety assessments, and the establishment of a causal link between transport correction, neural repair biology, and functional recovery. The therapeutic objective is not the indiscriminate enhancement of "flow," but the restoration of coordinated transport across the rate-limiting step that constrains recovery.