Related Experiment Video
Updated: Oct 22, 2026

Simultaneous Laryngopharyngeal and Conventional Esophageal pH Monitoring
Published on: December 14, 2020
High-Resolution Manometry Assessment of Esophagitis Across Los Angeles Grades Validates Lyon 2.0 Criteria
Marco Sozzi1, Stefano Siboni1, Pierfrancesco Visaggi2
1Division of General Surgery, IRCCS Policlinico San Donato, University of Milan.

Introduction:
Gastroesophageal reflux disease (GERD) with erosive esophagitis is driven by antireflux barrier (ARB) dysfunction, yet a comprehensive high-resolution manometry (HRM) assessment across Los Angeles (LA) grades is lacking. This study evaluates HRM metrics in patients with erosive esophagitis to validate Lyon 2.0 consensus criteria, hypothesizing that LA grade B esophagitis shares manometric features with severe GERD (LA grades C-D) and that HRM can stratify LA grade A patients for objective GERD risk.
Methods:
A retrospective multicenter study (July 2022 to July 2025) enrolled 254 patients with GERD symptoms and erosive esophagitis (LA grade A: 145, B: 84, C-D: 25) across 6 centers. Patients underwent off-PPI endoscopy, HRM, and pH monitoring. HRM assessed esophagogastric junction (EGJ) morphology, EGJ-contractile integral (EGJ-CI), ineffective esophageal motility (IEM), straight leg raise (SLR), and Milan Score. Pathologic GERD was defined per Lyon 2.0 criteria.
Results:
LA grades B and C-D showed a higher rate of hiatal hernia, positive SLR, and lower EGJ-CI compared with LA grade A (P<0.001). Milan Score increased with esophagitis severity (P<0.001). Reflux monitoring confirmed pathologic GERD in 96% (B) and 100% (C-D) versus 50% (A) based on pH and impedance criteria. In LA grade A, patients with ≥2 disrupted ARB mechanisms (67.5%) had higher GERD rates than those with intact ARB (29.2%).
Discussion:
HRM supports Lyon 2.0 inclusion of LA grade B as definitive GERD, with manometric profiles similar to C-D. In LA grade A, compromised ARB identifies higher GERD risk, guiding therapy escalation.

Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
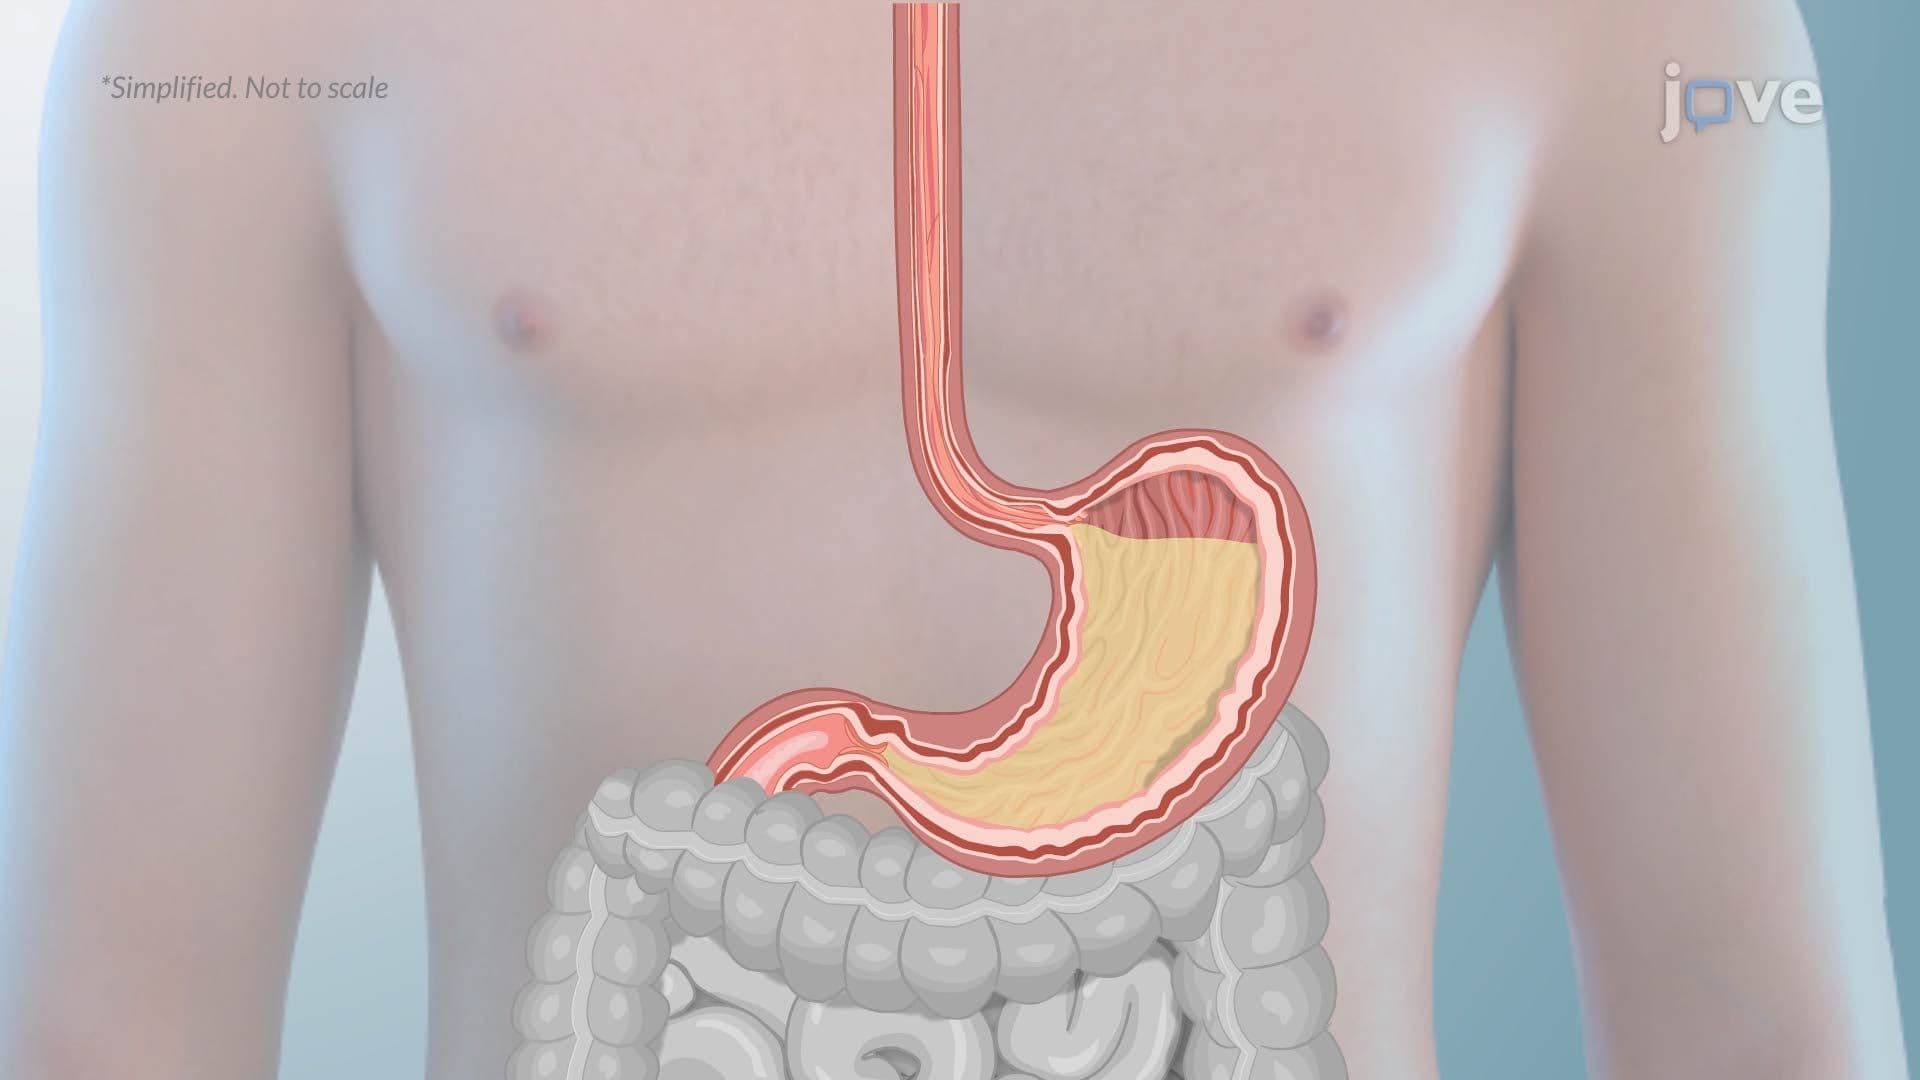 01:25
Gastroesophageal Reflux Disease
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...