Related Experiment Video
Updated: Oct 22, 2026
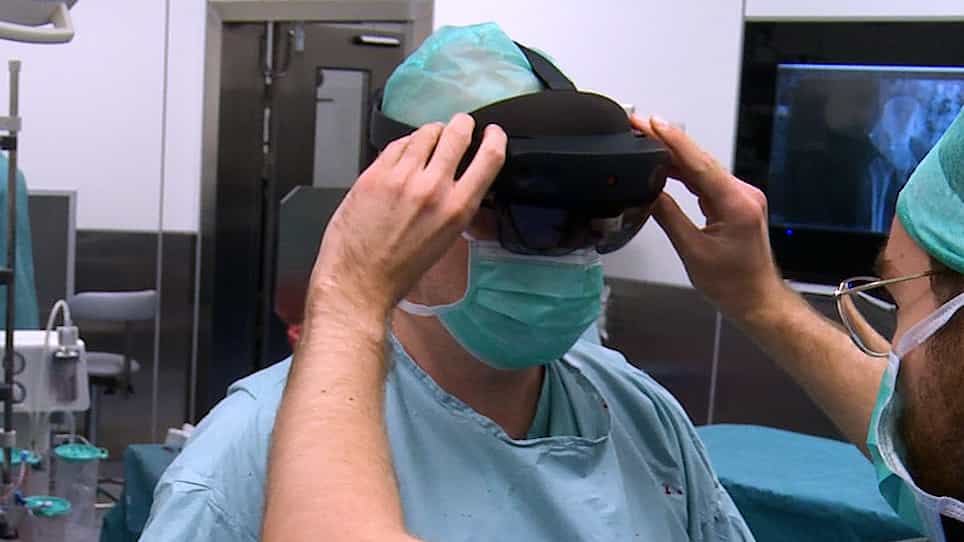
The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Patient-specific management in high-risk revision total hip arthroplasty: mid-term outcomes of a next-generation
Farouk Khury1,2,3, Blaine Luebbering4, Garrett Ruff4
1The Ruth and Bruce Rappaport Faculty of Medicine, Technion - Israel Institute of Technology, Haifa, Israel. farouk.khury@technion.ac.il.

Background:
Managing recurrent instability in revision total hip arthroplasty (rTHA) requires a personalized approach, as traditional constrained liners often yield suboptimal results due to locking-mechanism failure and limited impingement-free range of motion. This study aimed to evaluate the mid-term clinical outcomes of a novel constrained acetabular liner (CAL) when utilized as a patient-specific solution for a high-risk cohort undergoing complex rTHA. By tailoring the constraint to individual biomechanical deficits, this next-generation device seeks to mitigate historic failure modes.
Methods:
We retrospectively reviewed 32 patients who underwent 37 rTHA procedures with a next-generation CAL at a single urban academic center between March 2017 and October 2023. Average follow-up was 4.7 years (range, 0.3 to 9.7 years). The most common indication for rTHA was instability (70.3%), followed by infection (16.2%), aseptic loosening (10.8%), and polyethylene wear (2.7%). Just over one third of patients (37.5%) had undergone a prior revision. Preoperative constructs included fixed-bearing (37.8%), dual-mobility (32.4%), CAL (24.3%), static spacer (2.7%), and hemiarthroplasty (2.7%).
Results:
In most procedures (70.3%), the CAL was implanted into a pre-existing acetabular cup, whereas 29.7% involved both cup and liner revision. Following rTHA, no cases of implant wear, breakage, acetabular cup aseptic loosening, or periprosthetic fracture were observed. Six patients (18.8%) underwent a total of sixteen subsequent reoperations after CAL implantation-10 for instability and 6 for infection. Among instability-related reoperations, 4 involved revision to a new next-generation CAL. Survivorship free from all-cause reoperation was 83.8% at one year and 72.6% at latest follow-up.
Conclusions:
This study demonstrates favorable mid-term clinical outcomes and reoperation-free survivorship following complex revision THA using a novel constrained acetabular liner system. For patient cohorts suffering from severe recurrent dislocation, this next-generation CAL provides an effective, tailored tool in the surgical armamentarium by adapting to unique patient anatomy and soft-tissue compromises. Further research with larger sample sizes and extended follow-up is needed to assess long-term durability.