Related Experiment Video
Updated: Oct 23, 2026

Technique and Patient Selection Criteria of Right Anterior Mini-Thoracotomy for Minimal Access Aortic Valve Replacement
Published on: March 26, 2018
Computed tomography angiography with three-dimensional reconstruction for planning aortic valve replacement via right
1Department of Cardiovascular Surgery, First Affiliated Hospital of Anhui Medical University, Hefei, China.

Introduction:
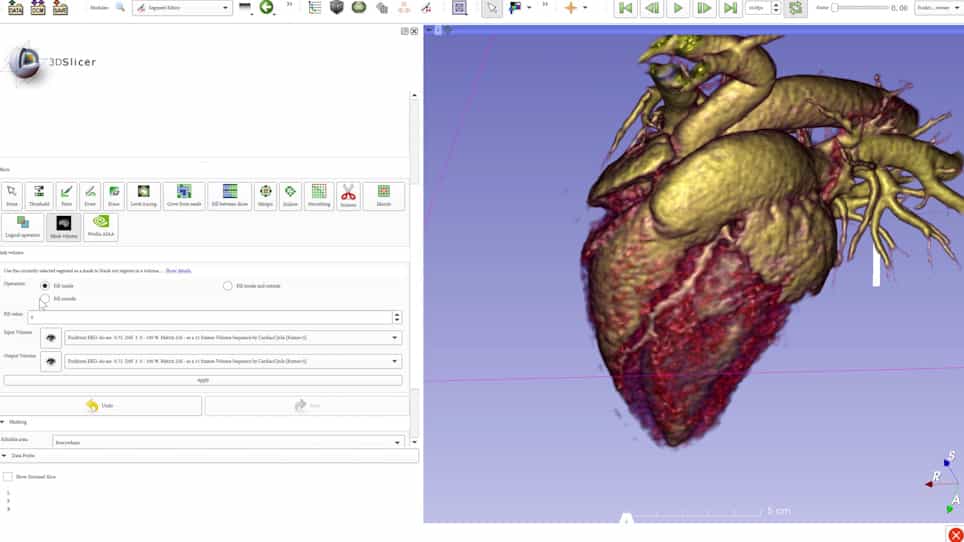
This study explored the value of computed tomography angiography (CTA) with three-dimensional (3D) reconstruction in aortic valve replacement (AVR) via right anterior mini-thoracotomy.
Methods:
Clinical data were retrospectively collected from 168 patients who underwent AVR at our institution in China between 1 July 2018 and 1 September 2022. After 1:1 propensity score matching, the experimental group (right anterior mini-thoracotomy) and control group (median sternotomy) each comprised 43 patients. Patients in the experimental group underwent preoperative aortic CTA with 3D reconstruction to guide individualised selection of the intercostal incision site. Perioperative and clinical outcomes were compared between groups.
Results:
The experimental group had significantly lower 24-hour postoperative drainage volume and shorter mechanical ventilation time, intensive care unit stay, and total hospital stay than the control group (all P<0.001). No intraoperative conversion to median sternotomy or postoperative reoperation for bleeding or pericardial tamponade occurred in the experimental group. Postoperatively, five patients (11.6%) developed atelectasis or pulmonary infection, five (11.6%) developed pleural effusion, and five (11.6%) developed subcutaneous emphysema or pneumothorax; none required thoracentesis. Aortic cross-clamping and cardiopulmonary bypass times were approximately 8 minutes longer, respectively, in the experimental group. At 24 months, the incidence of the composite endpoint-including all-cause mortality, cardiocerebrovascular complications, and readmission for massive pleural effusion or coagulation dysfunction-did not differ significantly between groups.
Conclusion:
Preoperative CTA with 3D reconstruction enables accurate localisation of the right intercostal incision for AVR via right anterior mini-thoracotomy. This technique preserves minimally invasive surgery benefits and does not increase risks of mid/long-term adverse events.