Related Experiment Video
Updated: Oct 24, 2026

Symmetric Bihemispheric Postmortem Brain Cutting to Study Healthy and Pathological Brain Conditions in Humans
Published on: December 18, 2016
Post-traumatic cognitive decline and neurodegenerative disease: a narrative review and proposed framework for
Jae Jin Park1, Seung Young Chung1, Seong Min Kim1
1Department of Neurosurgery, Eulji University Hospital, Eulji University College of Medicine, Daejeon, Republic of Korea.

Background:
When a patient with a history of traumatic brain injury (TBI) develops progressive cognitive decline months to years after injury, clinicians must consider injury sequelae, an independent neurodegenerative disease, or both. Existing diagnostic frameworks each address a different aspect of this question, and none was constructed to apportion contribution between them. The distinction matters for management because AD-directed therapy should be considered only after biological Alzheimer's disease (AD) has been established, followed by separate assessment of treatment eligibility and safety.
Objective:
To synthesise evidence on cognitive change after TBI and the clinical, biomarker, and neuroimaging information available when delayed decline is evaluated, and to propose a structure for that evaluation.
Methods:
Structured narrative review. A documented de novo PubMed search was conducted on 27 July 2026, covering January 2015 to the search date, using two complementary strategies: one addressing cognitive, functional and neurodegenerative outcomes after TBI, and one addressing biomarker and neuroimaging evidence with longitudinal and prognostic terms. Diagnostic and research criteria, neuropathological and mechanistic references, comparator biomarker studies, and treatment trials were identified through targeted retrieval and reference checking. Exhaustive title and abstract screening, dual-reviewer study selection, formal risk-of-bias assessment, and quantitative synthesis were not undertaken.
Results:
Four patterns of cognitive change after TBI are proposed as unvalidated longitudinal clinical heuristics rather than validated diagnostic categories, and no prevalence is estimated for any of them. Delayed progressive deterioration following an initial plateau presents the greatest diagnostic difficulty. Blood biomarkers can support evaluation for coexisting biological AD, but neurofilament light and glial fibrillary acidic protein kinetics vary with injury severity and sampling window, and no validated biomarker profile identifies injury-driven neurodegeneration in an individual patient. Tau-related pathology, impaired protein clearance, and chronic neuroinflammatory activity are plausible contributors not shown to form a unified causal cascade.
Conclusion:
Current evidence supports structured longitudinal reassessment and evaluation of competing explanations rather than etiological classification by biomarker pattern. A proposed assessment pathway, and a framework for stating what can and cannot be concluded in an individual patient, are offered as testable structures, including for medicolegal settings in which causal attribution is requested.
Related Concept Videos
 01:29
Alzheimer Disease l: Introduction
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
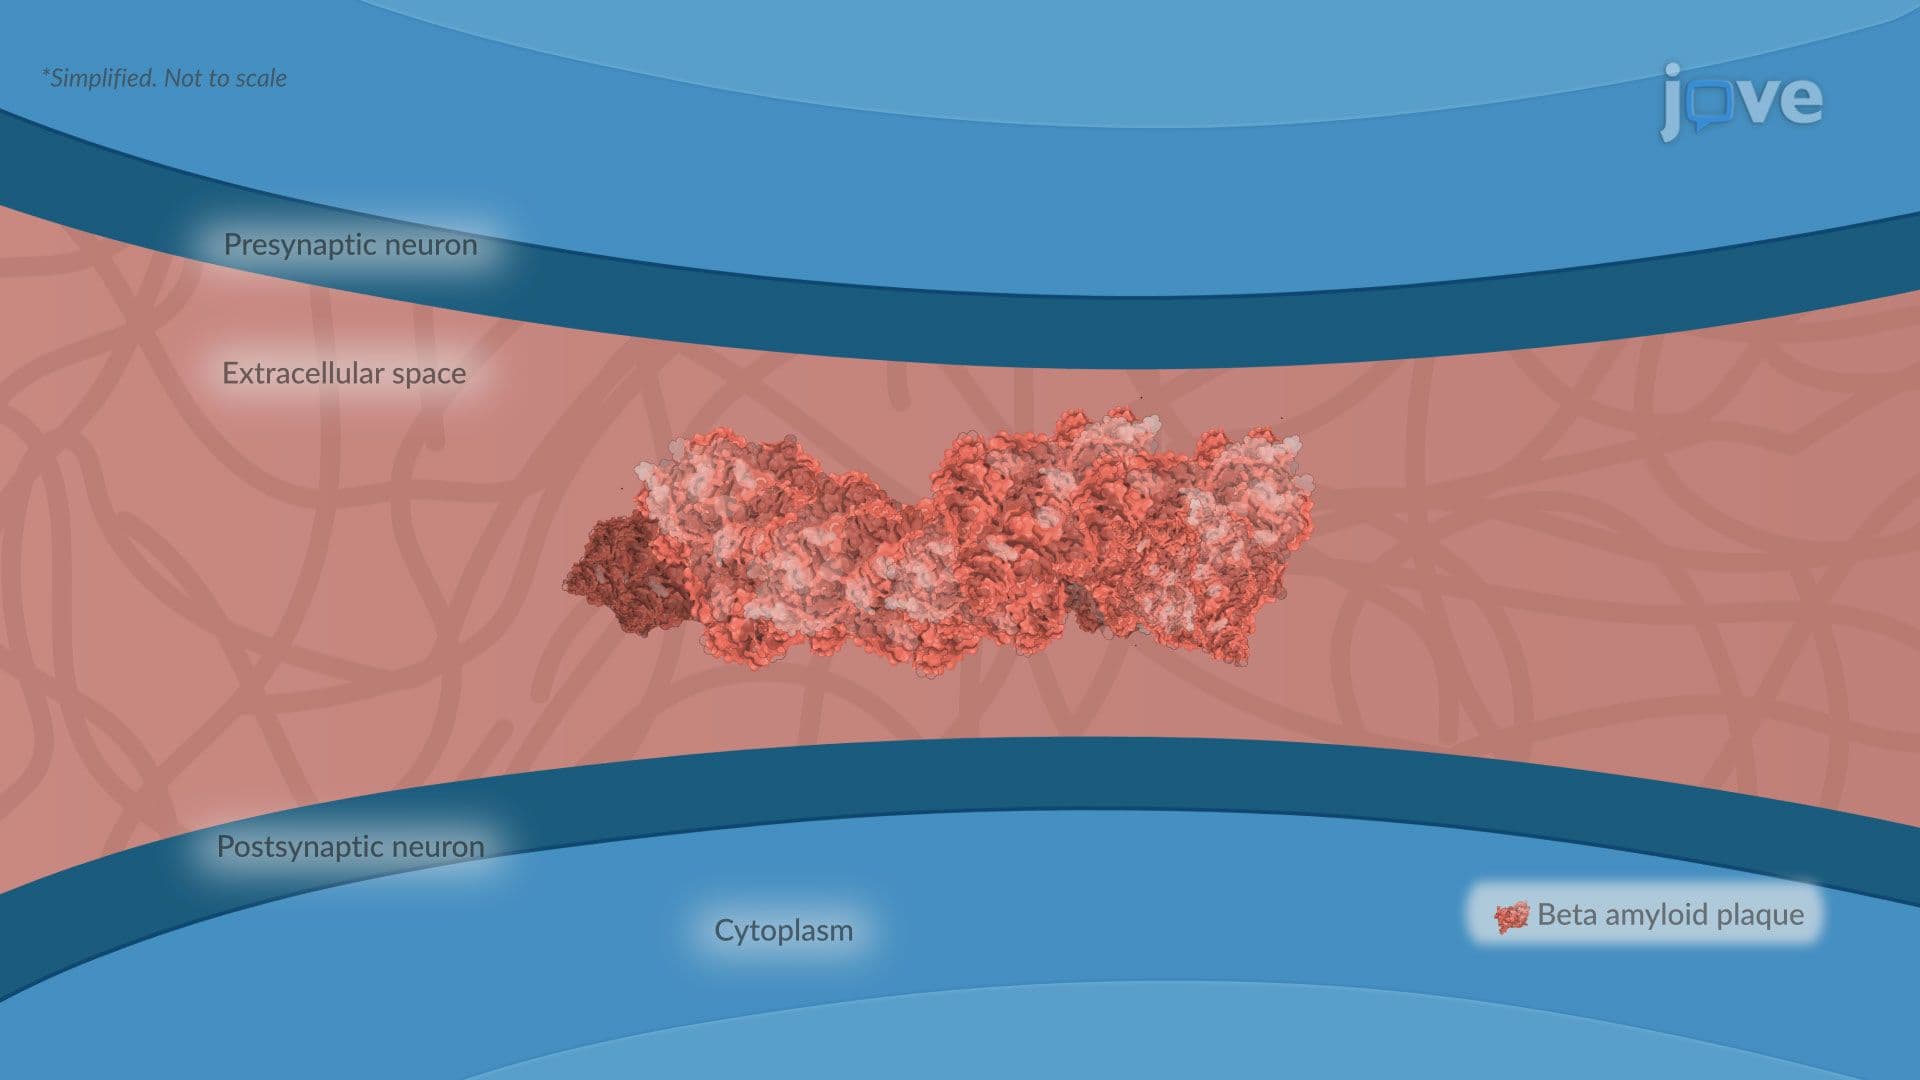 01:22
Dementia l: Introduction
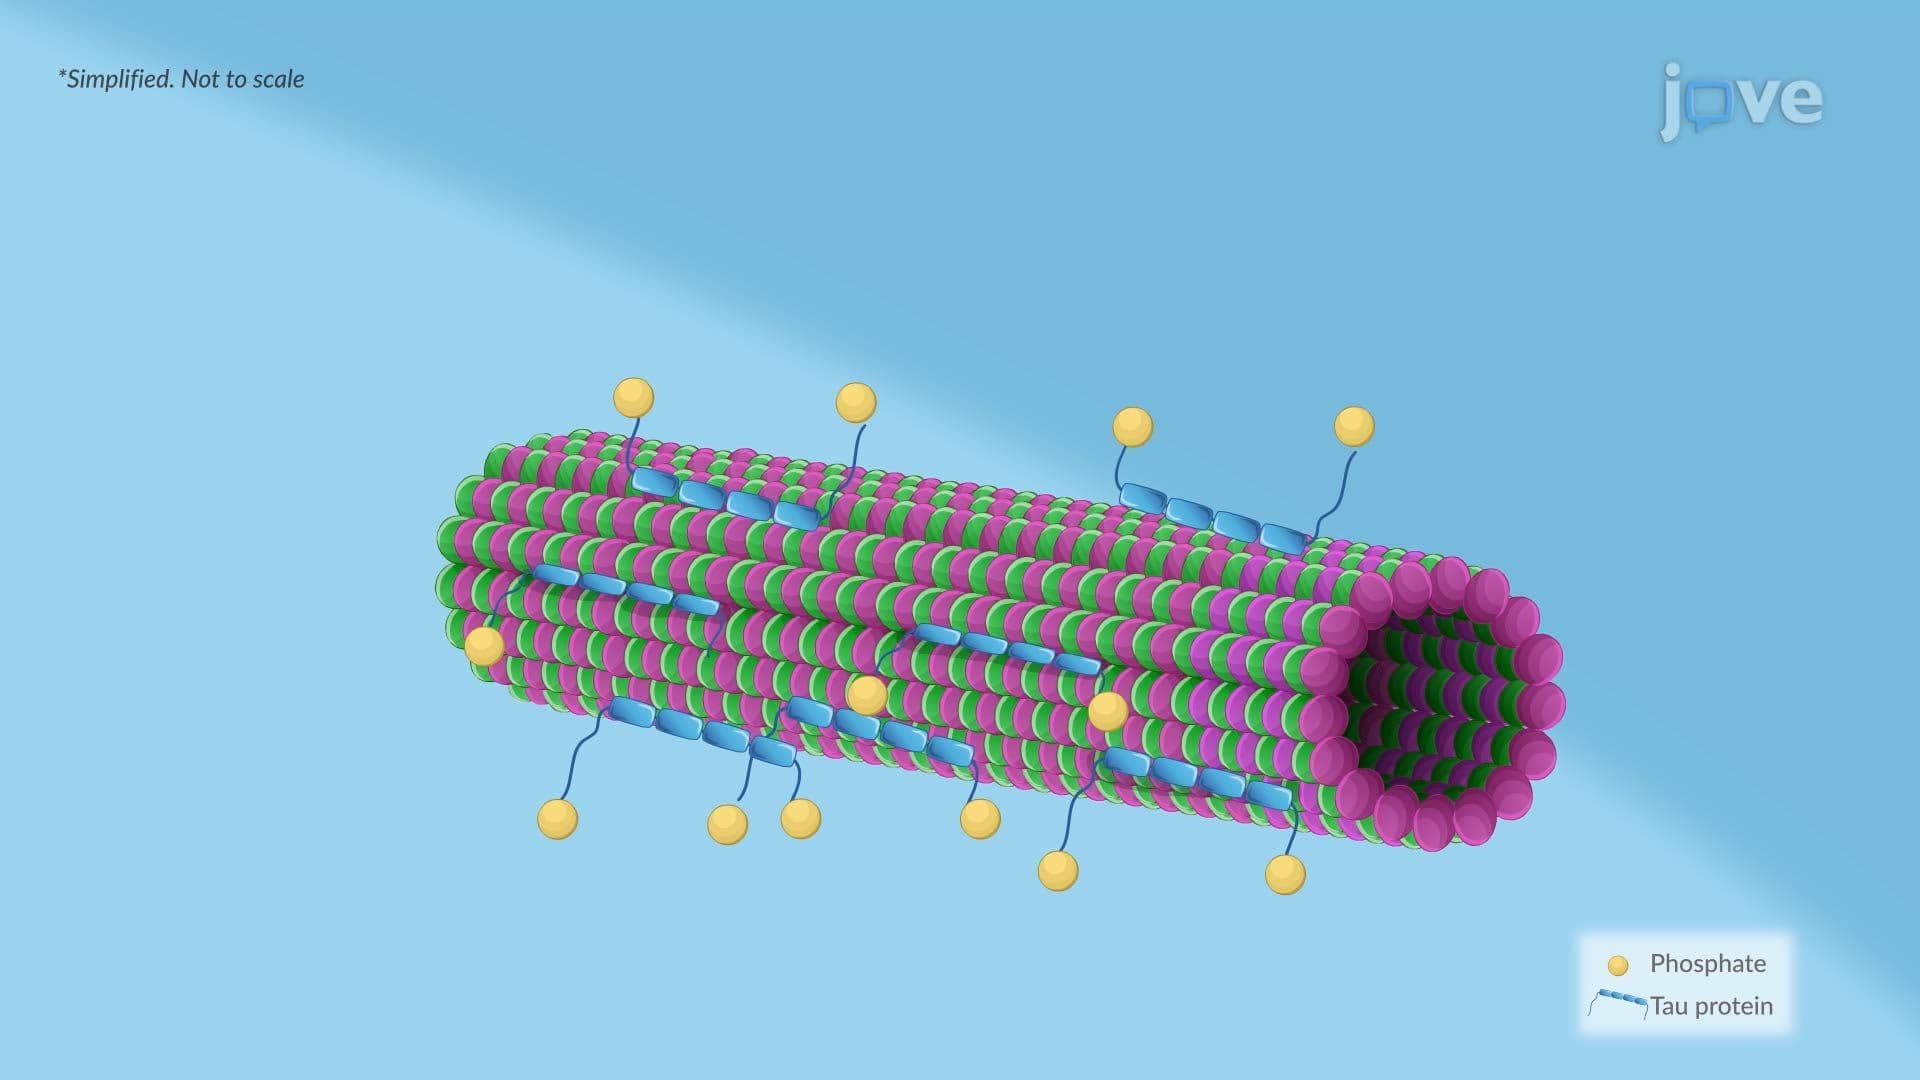 01:23
Alzheimer Disease ll: Pathophysiology
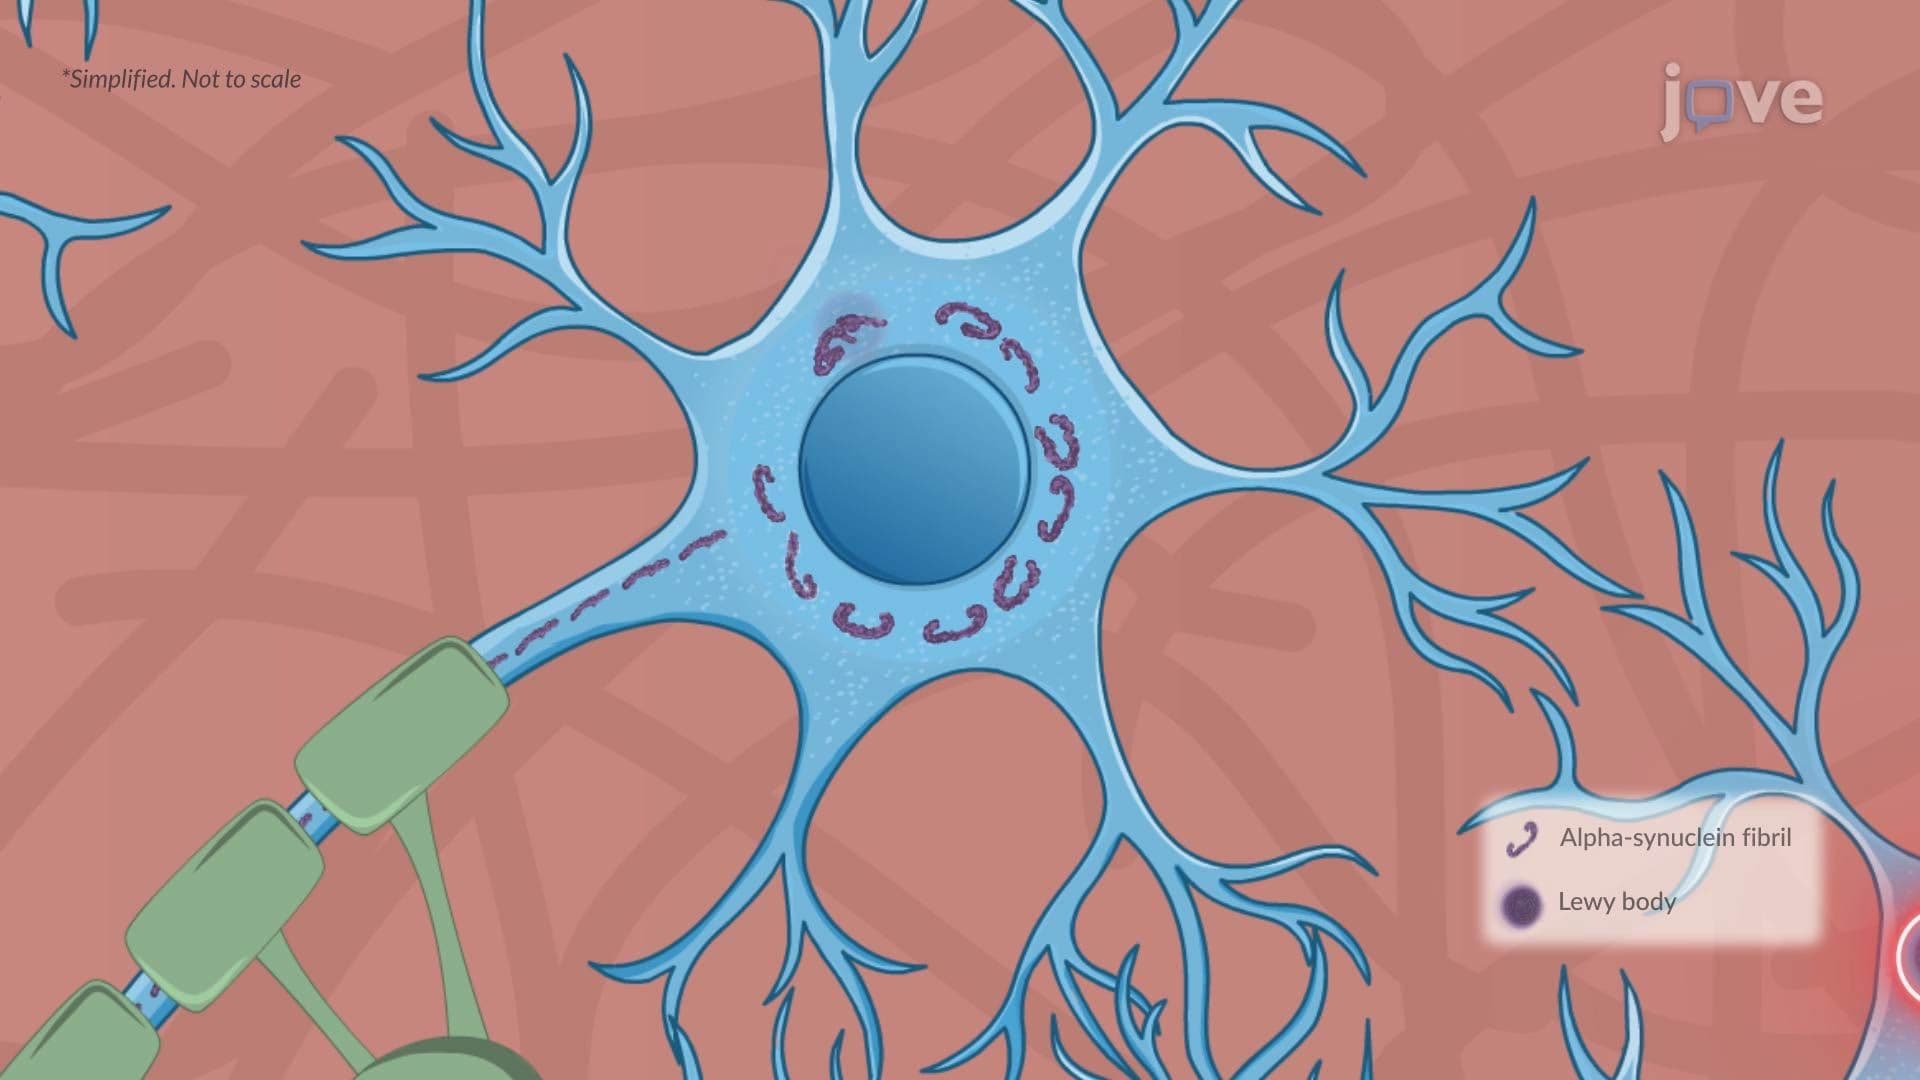 01:24
Parkinson Disease ll: Pathophysiology
 01:27
Post-traumatic Stress Disorder
Symptoms and Behavioral Manifestations
A spectrum of distressing symptoms characterizes PTSD. Recurrent flashbacks, where individuals involuntarily relive traumatic events, are a...