Related Experiment Video
Updated: Oct 24, 2026
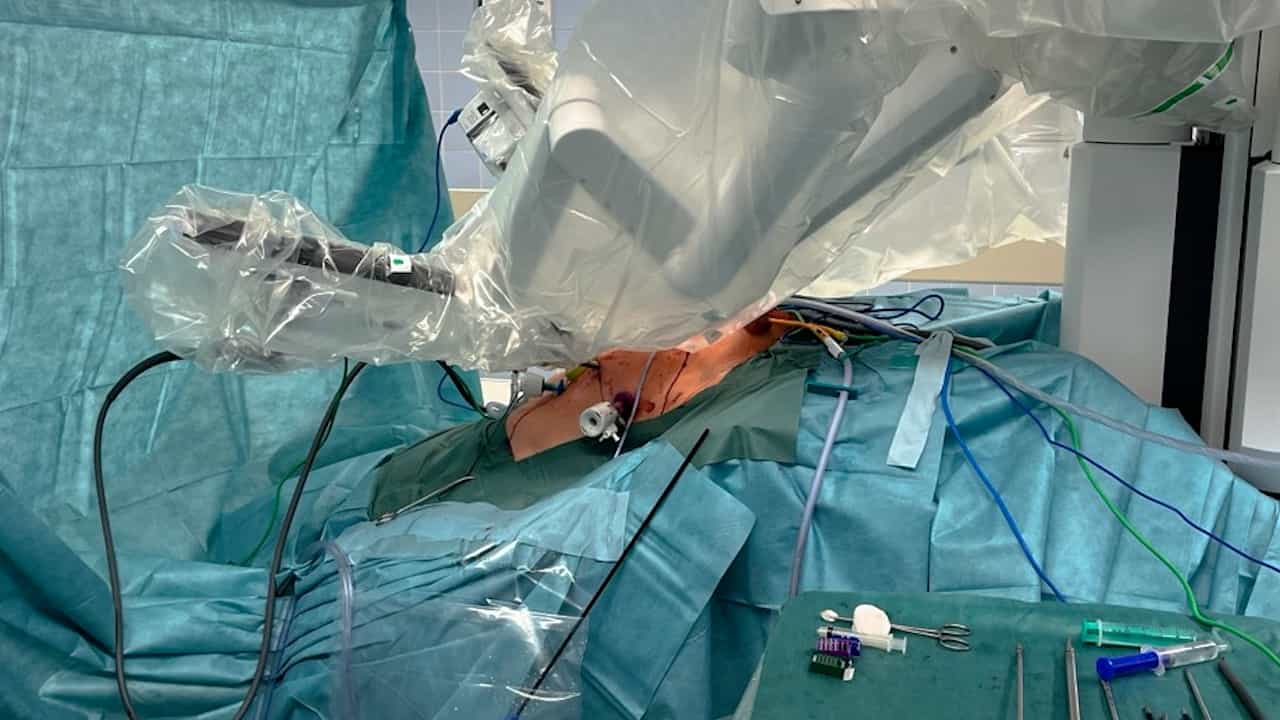
Robot-Assisted Radical Prostatectomy in a Heart Transplant Patient
Published on: July 17, 2026
Cardiovascular disease-specific mortality after partial versus radical nephrectomy for stage II renal cancer: A
Yao Hao1, Zhicheng Dai2, Feng Li3
1Department of Urology, Jingzhou First People's Hospital, The First Affiliated Hospital of Yangtze University, Jingzhou, Hubei, 434000, China; Center of Laboratory Medicine, General Hospital of Ningxia Medical University, Yinchuan, Ningxia, 750004, China.

Background:
Surgery remains standard treatment for localized renal cancer. Whether partial nephrectomy (PN), compared with radical nephrectomy (RN), affects long-term cardiovascular disease-specific mortality (CVD-SM) in stage II disease is uncertain. We assessed this association using competing-risk methods.
Methods:
Patients with T2N0M0 renal cancer diagnosed in the SEER database from 2004 to 2022 were included. Missing tumor grade and unspecified T2 subclassification were addressed by multiple imputation. Propensity-score matching was performed within 10 imputed datasets. Cumulative incidence functions were estimated using the Aalen-Johansen method. Fine-Gray models were primary, with cause-specific Cox models as supportive analyses; estimates were pooled across imputations.
Results:
The cohort included 14,602 patients (PN, n = 1294; RN, n = 13,308), with a median follow-up of 85 months. After matching, 1290-1292 patients per group were retained. Five-year CVD-SM cumulative incidence was 2.68% after PN and 3.07% after RN; 10-year estimates were 7.18% and 6.63%, respectively. No significant association was observed (Fine-Gray sHR, 1.10; 95% CI, 0.69-1.74; P = 0.690; Cox HR, 1.04; 95% CI, 0.66-1.64; P = 0.867). PN was associated with lower cancer-specific mortality (Fine-Gray sHR, 0.58; 95% CI, 0.42-0.80; P < 0.001).
Conclusion:
Among patients with stage II renal cancer, surgical approach was not significantly associated with CVD-SM. However, estimate imprecision and unavailable cardiovascular and renal risk factors preclude claims of equivalence or exclusion of clinically meaningful effects. The potential cardiovascular benefit of PN remains uncertain. Its lower cancer-specific mortality should be interpreted cautiously because residual surgical-selection confounding may persist.
Synopsis:
Cardiovascular disease-specific mortality represents an important long-term competing risk in patients with stage II renal cancer. No statistically significant association between surgical approach and cardiovascular disease-specific mortality was detected, leaving the cardiovascular survival advantage of partial nephrectomy uncertain.
