Related Experiment Video
Updated: Oct 24, 2026
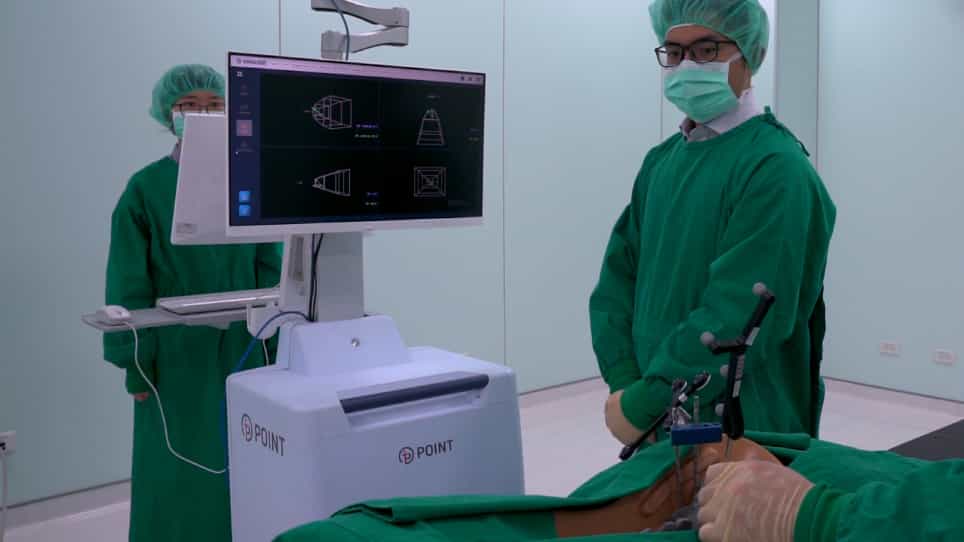
A Spine Robotic-Assisted Navigation System for Pedicle Screw Placement
Published on: May 11, 2020
2026 North American Spine Society Patient Safety Position Statement on Education, Training, and Competency for Spine
Brian W Su1, Karin R Swartz2, Pierce D Nunley3
1Marin Health Spine Institute, 2 Bon Air Rd. Ste. 120, Larkspur, CA 94939-1142.

Abstract:
The rapid expansion of minimally invasive, endoscopic, percutaneous, and implant-based spine interventions has outpaced standardized training requirements. This statement provides recommendations based on current training pathways, contemporary practice, and expert consensus, with patient safety as the guiding principle. These recommendations are not intended to define or restrict scope of practice; credentialing decisions remain the responsibility of institutions and governing bodies. Formal surgical spine training currently occurs through orthopaedic surgery residency with spine fellowship or neurological surgery residency with or without spine fellowship. These pathways include substantial supervised operative experience and ACGME residency case minimums. Anesthesiology, physical medicine and rehabilitation, radiology, and pain medicine pathways provide procedural training but do not include operative spine training, and nationally recognized training pathways for these specialties do not have minimum required case volumes across the spectrum of advanced spine interventions. Minimum case numbers, where established, are only one component of competency and should be considered alongside appropriate education, supervised experience, and demonstrated competency. Training and credentialing should reflect procedural complexity, anatomy at risk, biomechanical alteration, and potential complications. A surgical intervention treats structural spinal anatomy and meaningfully alters biomechanics or directly visualizes and decompresses the spinal cord and/or nerve roots. Based on current training pathways, spinal fusion or permanent stabilization, direct spinal cord and/or nerve root decompression, lateral sacroiliac fusion, vertebral augmentation with structural vertebral implants beyond cement or bone graft, and spinal cord stimulation paddle lead placement should be performed by physicians with formal surgical spine training. Other non-structural interventions, including basivertebral nerve ablation, percutaneous neuromodulation, cement or bone-graft vertebral augmentation, and endoscopic branch neurectomy, should require structured procedure-specific education, supervised experience, appropriate minimum case numbers, and competency assessment. Educational courses should complement rather than replace structured clinical experience. This statement encourages prospective registries for emerging technologies to evaluate outcomes, complications, reinterventions, durability, subsequent surgical consequences, and inform training standards. Transparent informed consent and documented complication-management arrangements established before the procedure in every practice setting, including physician offices, are essential.

